Related Experiment Video
Updated: Jan 13, 2026
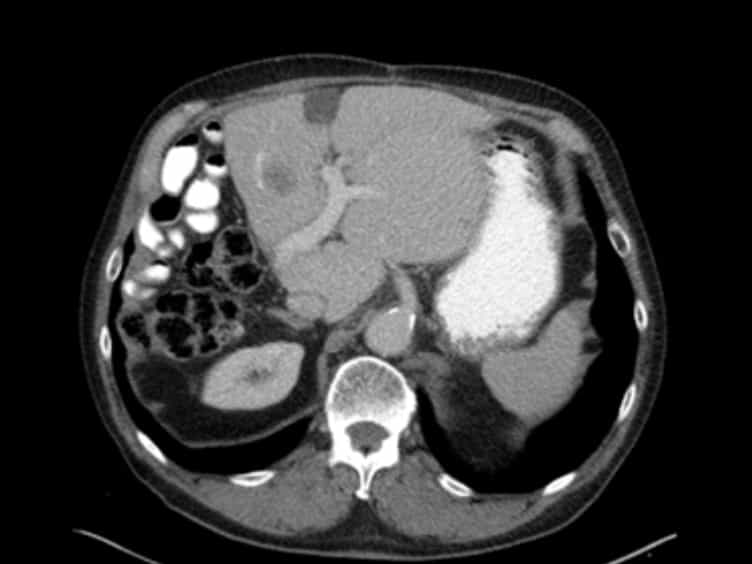

The Influence of Liver Resection on Intrahepatic Tumor Growth
Published on: April 9, 2016
Quantification of remnant liver ischemia after hepatectomy using advanced 3D-software analysis and its impact on
Acidi Belkacem1, Ghallab Mohamed2, Ali Omar3
1Department of Surgery, Paul-Brousse Hospital, Assistance Publique Hôpitaux de Paris, Centre Hépato-Biliaire, Villejuif, Cedex, France; Chaire d'Innovation Bloc Opératoire Augmenté (BOPA), Assistance Publique Hôpitaux de Paris, Institut Mines-Telecoms, Université Paris-Saclay, France; Inserm Unit, Paris Saclay University, UMRS 1193, Villejuif, France.

Background:
Recurrence of hepatocellular carcinoma postresection remains a major clinical challenge after resection, with rates as high as 70% at 5 years. Although the biology of hepatocellular carcinoma has been extensively studied, the impact of surgical technique, particularly the effect of remnant liver ischemia following hepatectomy, has not been thoroughly explored. The primary endpoint was to establish the correlation between remnant liver ischemia volume and hepatocellular carcinoma recurrence rates, with secondary endpoints comparing remnant liver ischemia incidence in anatomic resections versus nonanatomic resections and their subsequent oncologic outcomes.
Methods:
This study retrospectively assessed 238 patients who underwent liver resection for hepatocellular carcinoma from 2012 to 2021. Early postoperative computed tomography scans were analyzed using 3D imaging software to detect and quantify remnant liver ischemia.
Results:
Remnant liver ischemia was present in 71% of patients, with univariate analysis showing a significant increase in 1-year hepatocellular carcinoma recurrence rates for patients with remnant liver ischemia (16% vs 5%, P = .041). Anatomic resection was associated with a lower incidence of remnant liver ischemia compared with nonanatomic resection (23% vs 77%, P < .05). Receiver operating characteristic curve analysis determined a remnant liver ischemia volume threshold of 80 mL, which was further examined in subgroup analysis (Low-remnant liver ischemia group < 80 mL < High-remnant liver ischemia group). Multivariate analysis revealed high remnant liver ischemia volume (hazard ratio 2.06 [1.13-3.76], P = .019) and nonanatomic resection (hazard ratio 2.55 [1.19-5.55], P < .016) as independent risk factors for hepatocellular carcinoma recurrence.
Conclusion:
The presence and volume of remnant liver ischemia are significant predictors of hepatocellular carcinoma recurrence postresection. This study emphasizes the utility of 3D imaging in surgical planning and the potential of adjunctive techniques, such as fluorescence guided liver surgery, to minimize remnant liver ischemia and improve oncologic outcomes.
More Related Videos
 11:10
Visualization of Vascular and Parenchymal Regeneration after 70% Partial Hepatectomy in Normal Mice
Published on: September 13, 2016
 08:15
A Hepatocellular Cancer Patient-Derived Organoid Xenograft Model to Investigate Impact of Liver Regeneration on Tumor Growth
Published on: February 2, 2024