Related Experiment Video
Updated: Jan 12, 2026
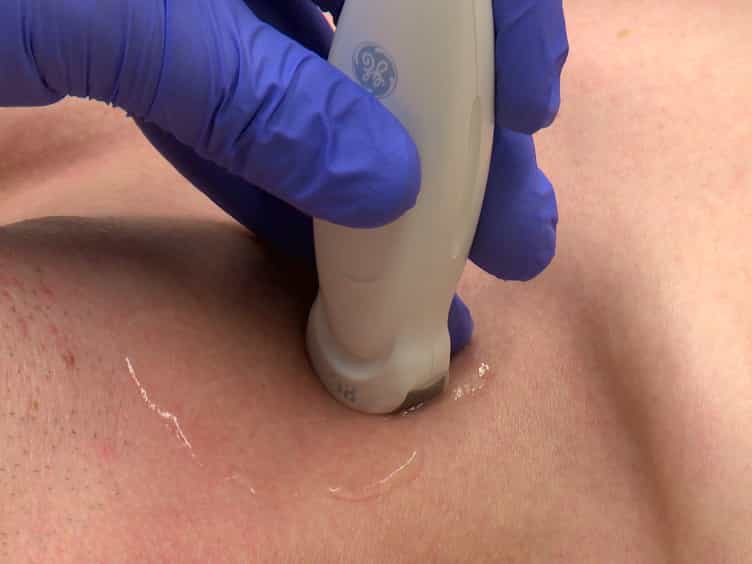

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Comparative Evaluation of Supraclavicular Versus Infraclavicular Approach With Regard to Right Subclavian Vein
Chintalapalli Ch Shanmuka Srikanth1, Krishna Anusha Akula2, Kamisetty Mani Bharath1
1Department of Anaesthesiology, Konaseema Institute of Medical Sciences, Amalapuram, IND.

Abstract:
Background In settings where real-time ultrasonography (USG) is unavailable or delayed, landmark-guided central venous access remains essential. Anatomically, the right supraclavicular (SC) route offers a more direct course to the superior vena cava than the infraclavicular (IC) approach, which could shorten procedural time without increasing risk. Methods We conducted a prospective, single-centre, parallel-group randomised controlled trial in adult elective cardiac surgery patients (n=70; 35 per arm) comparing landmark-guided right subclavian venous catheterisation via SC versus IC approaches, using a standardised Seldinger technique. The primary outcome was total cannulation time. Secondary outcomes included access time, number of puncture attempts, observer-rated ease of guidewire/catheter passage, success rate and complications. Binary outcomes were analysed for all randomised patients; timing outcomes were assessed in procedures with complete records (n=62; SC: 32, IC: 30). Results SC significantly reduced procedure duration. The mean total cannulation time was 2.98±0.59 minutes (SC) versus 3.70±0.77 minutes (IC), with a mean difference of -0.72 minutes (95% confidence interval (CI): -1.07 to -0.37; p<0.001). The mean access time was 17.72±17.89 seconds (SC) versus 35.80±33.63 seconds (IC), with a mean difference of -18.1 seconds (95% CI: -32.0 to -4.2; p=0.012). The distribution of puncture attempts and observer-rated ease scores did not differ materially between groups. Overall success was high (94.3% SC versus 85.7% IC; Fisher's exact test; p=0.428). Complications were infrequent: subclavian arterial puncture occurred in 2/35 (SC) versus 5/35 (IC) (p=0.428); no pneumothorax, haemothorax, haematoma or catheter malposition was observed. Conclusions In adult cardiac surgical patients, the SC approach achieves faster landmark-guided right subclavian venous access than the approach, without detectable compromises in success or safety. These findings support routine competence with the SC technique when ultrasound cannot be used and justify larger multicentre trials powered for rare complications and operator-learning effects.


Related Concept Videos
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:28
Cardiac Catheterization I: Pre-Procedure Overview