Related Experiment Video
Updated: Jan 12, 2026
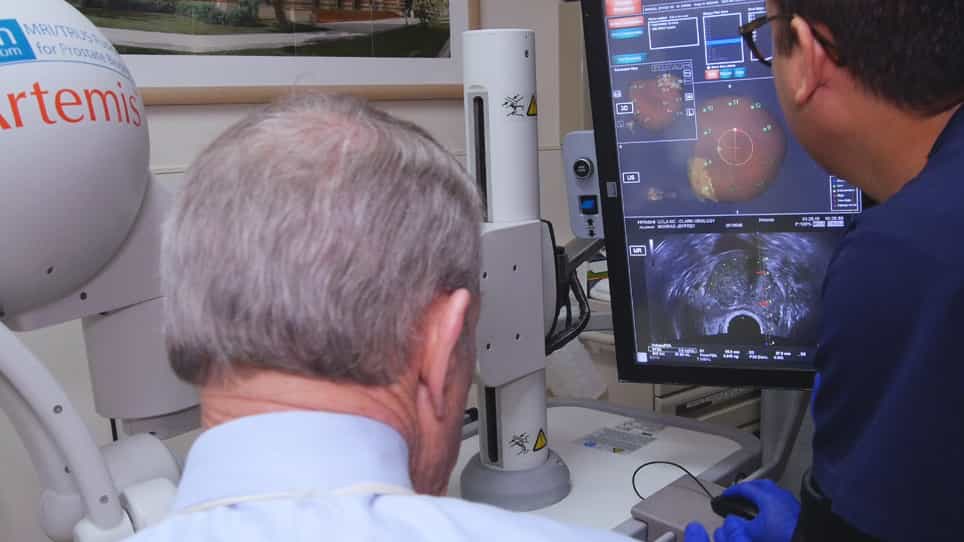
Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Standalone 29-MHz micro-ultrasound for classifying clinically significant prostate cancer: a systematic review and
Ahmed M Abdel Gawad1, Ahmed Y Aboelsaad1, Ahmed Fawzi Elsayed1
1Urology Department, Faculty of Medicine, Al-Azhar University, Damietta, Egypt.

Background:
Micro-ultrasound (micro-US; 29-MHz) offers real-time, high-resolution prostate imaging, but its stand-alone diagnostic accuracy remains uncertain. We synthesized prospective evidence to evaluate micro-US for classifying clinically significant prostate cancer (csPCa) using histopathology as the reference standard.
Methods:
We searched PubMed, Embase, Scopus, and Web of Science (inception-20 May 2025) for prospective studies assessing micro-US as an index test on a diagnostic pathway. Data were pooled using random-effects models on logit-transformed sensitivity and specificity, with an HSROC representation and model diagnostics. Subgroup and meta-regression analyses explored heterogeneity, including threshold (PRI-MUS) and spectrum effects. Clinical utility was appraised using Fagan nomograms and a likelihood-ratio scatter. Small-study effects were evaluated with Deeks' test.
Results:
Five prospective studies met criteria. Pooled sensitivity was 0.84 (95% CI 0.65-0.94) and pooled specificity was 0.41 (95% CI 0.25-0.59), indicating moderate discrimination on HSROC. Secondary metrics were concordant (PLR 1.45, 95% CI 1.17-1.80; NLR 0.37, 95% CI 0.23-0.61; DOR 3.95, 95% CI 2.48-6.30). On a 25% pre-test probability, the Fagan nomogram showed modest shifts (~ 33% after a positive test; ~11% after a negative), supporting a triage/rule-out role. Heterogeneity was substantial and strongly influenced by threshold and clinical spectrum differences; subgroup and meta-regression suggested that spectrum-related factors were associated with lower specificity, whereas no covariate robustly altered sensitivity (exploratory given small k). Model checks were acceptable, and Deeks' test showed no evidence of small-study effects (p ≈ 0.70).
Conclusion:
As a stand-alone index test for csPCa classification, micro-US demonstrates high sensitivity but low specificity, yielding modest impact on post-test probability. These findings support micro-US as a complementary/triage (rule-out) adjunct, particularly when mpMRI is unavailable, contraindicated, or delayed, while highlighting the need for standardized PRI-MUS thresholds, reader training, and larger multicenter studies to refine specificity and clarify integration with MRI-based pathways.