Related Experiment Video
Updated: Jan 12, 2026
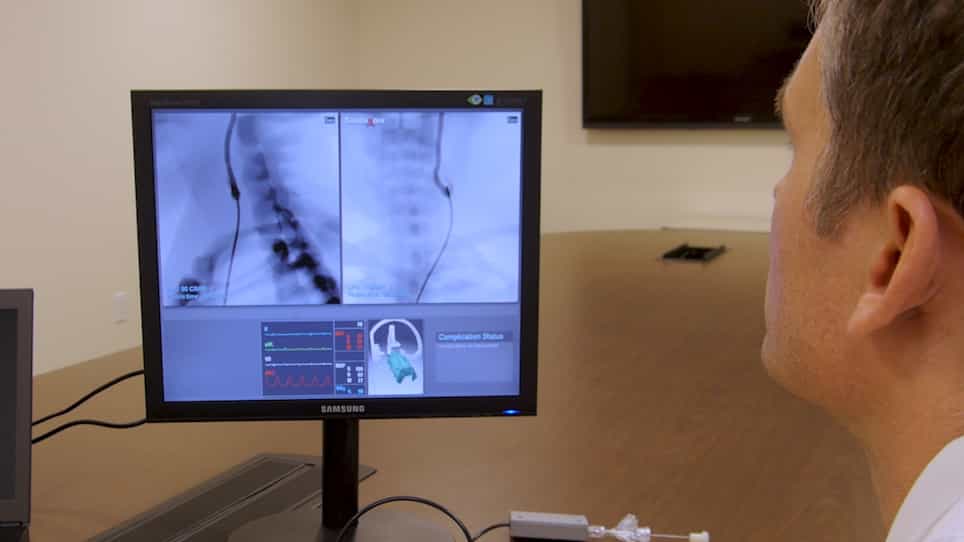

Simulator Training for Endovascular Neurosurgery
Published on: May 6, 2020
Goal-directed fluid therapy for endovascular therapeutic procedures in patients with aneurysmal subarachnoid
Saurav Singh1, Arvind Chaturvedi1, Ashish Bindra1
1Department of Neuroanaesthesiology and Critical Care, All India Institute of Medical Sciences, New Delhi, India.

Background And Aims:
Hypovolemia and hypotension are the main risk factors for the development of vasospasm or delayed cerebral ischemia in patients with aneurysmal subarachnoid hemorrhage (aSAH). We aimed to compare the duration of hypovolemia and hypotension between goal-directed fluid therapy (GDFT) and standard fluid therapy (SFT) in patients undergoing endovascular therapeutic procedures for aSAH.
Material And Methods:
Twenty patients were enrolled in this single-center, prospective, randomized controlled, and double-blind study. Patients were randomized into the GDFT group (n = 10) and SFT group (n = 10). A cardiac output monitoring device was used in both groups to calculate the duration of hypovolemia and hypotension. Appropriate statistical tests were used, and a P value < 0.05 was considered statistically significant.
Results:
The demographic profile was comparable between both the groups. Fifty percent of the study population was hypovolemic before the procedure. The total duration of hypovolemia and hypotension [median (minimum-maximum)] was 3.66 min (0-10.66) and 4 (0-30) min (P = 0.82) and 4.33 (3-6.66) min and 4.66 (3.33-7.33) min (P = 0.09) in GDFT and SFT groups, respectively. Patients in the GDFT groups received significantly lower volumes of intraprocedural crystalloids. However, the total volume of fluids used was comparable between the groups.
Conclusions:
Preprocedural hypovolemia is prevalent among patients scheduled for endovascular therapeutic procedures for aSAH. Duration of intraprocedural hypovolemia and duration of hypotension is comparable between GDFT and SFT groups in patients undergoing endovascular therapeutic procedures for aSAH. Hence, GDFT offers no distinctive advantage over SFT and should be individualized to specific patient needs (and not generalized to all the patients) undergoing endovascular therapeutic procedures for aSAH.


