Related Experiment Video
Updated: Jan 12, 2026
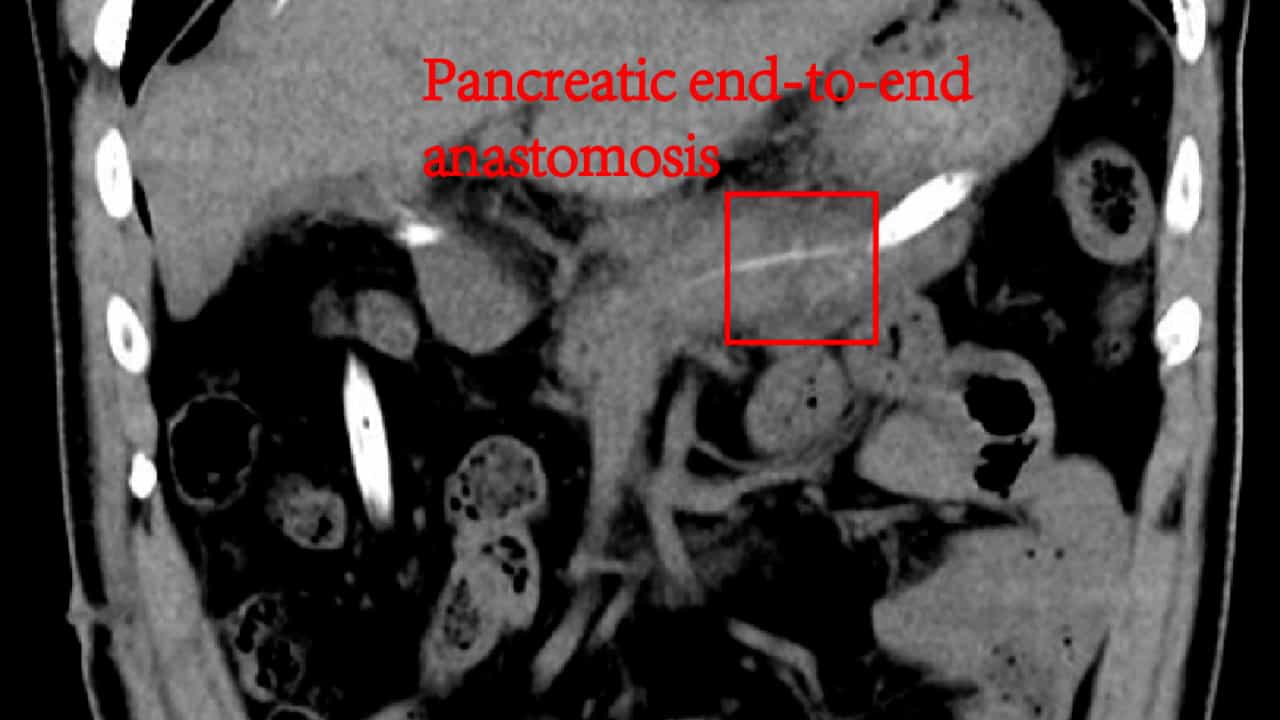

Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Evolution of the Indications and Outcomes of Total Pancreatectomy
Hallbera Gudmundsdottir1, Stella K Adjei Antwi, Cornelius A Thiels
1From the Department of Surgery, Mayo Clinic, Rochester, MN.

Background:
The first total pancreatectomy (TP) resulting in survival past the immediate postoperative period was performed at Mayo Clinic in 1944. Although still uncommonly performed, indications have recently fluctuated. We aimed to evaluate trends in TP use and outcomes over four decades.
Study Design:
Patients who underwent single-stage TP at Mayo Clinic Rochester from 1988 to 2024 were analyzed in two cohorts: early era (EE, 1988 to 2009) and modern era (ME, 2010 to 2024).
Results:
In total, 437 patients were identified: 118 during EE (mean 8 per year) and 319 during ME (mean 21 per year). Primary indications were adenocarcinoma (42% EE vs 60% ME), intraductal papillary mucinous neoplasm (31% EE vs 17% ME), and chronic pancreatitis (11% EE vs 13% ME; p < 0.001). Concurrent vascular resection was performed in 9.3% (EE; all venous only) vs 53% (ME; venous alone in 20% and arterial with or without venous in 33%; p < 0.001). Multivisceral resection was performed in <1% (EE) vs 24% (ME; p < 0.001). Major complications occurred in 13% (EE) vs 27% (ME; p = 0.018), and 90-day mortality was 3.4% (EE) vs 6.3% (ME; p = 0.35). For adenocarcinoma, 5-year median overall survival from both surgery and diagnosis was significantly improved in ME (p = 0.009 and p < 0.001, respectively). Median last HbA1c was 7.7 (EE) vs 7.3 (ME; p < 0.001). Among patients surviving more than 1 year, insulin pumps were used in 12% (EE) vs 49% (ME; p < 0.001).
Conclusions:
The use of TP has dramatically increased in recent years, primarily for adenocarcinoma alongside increased use of neoadjuvant therapy and ever-expanding criteria for anatomic resectability. Operative complexity has significantly increased with resultant increased perioperative morbidity. TP remains a higher-risk procedure, specifically with en bloc vascular resections, emphasizing the importance of appropriate patient selection, preoperative patient education, and thoughtful postoperative and long-term management.