Related Experiment Video
Updated: Jan 12, 2026
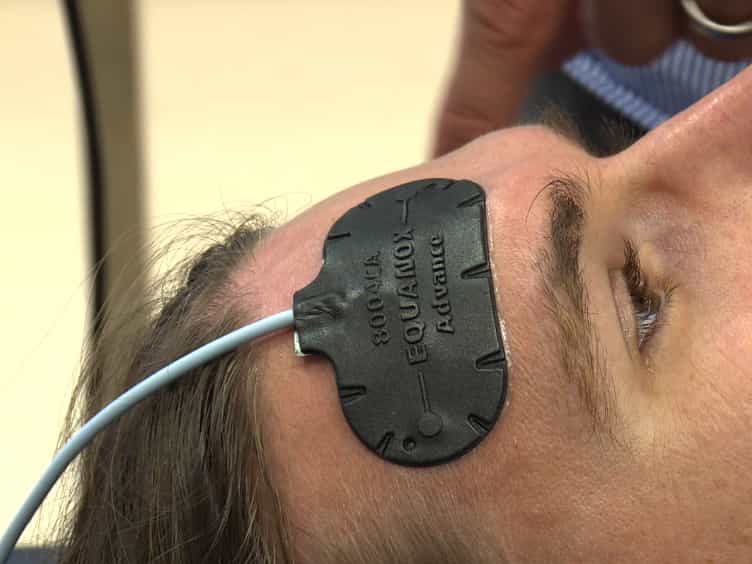
A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
The hypoxic ventilatory response and arousal burden predict the magnitude of ventilatory long-term facilitation in
Jason H Mateika1,2,3, Danny Hammo1,2, Dylan M Kissane1,2
1John D. Dingell Veterans Affairs Medical Center, Detroit, Michigan, USA.

Abstract:
The magnitude of progressive augmentation (PA) and ventilatory long-term facilitation (vLTF) are two forms of respiratory plasticity that are enhanced in some humans with obstructive sleep apnoea (OSA). This response might be linked to repeated nocturnal exposure to intermittent hypoxia or other traits connected to OSA. A meta-analysis was completed using data from 91 OSA participants who completed one of two mild intermittent hypoxia protocols during wakefulness. Two iterations of a subset regression analysis were completed to identify the best model that predicted the magnitude of PA or vLTF. Novel (e.g., arousal and hypoxic burden) or standard indicators of sleep apnoea (e.g., apnoea/hypopnoea index), anthropometric variables, protocol elements and physiological variables measured during wake and sleep were included as independent variables. After model selection, a multiple linear regression analysis was used to identify the most impactful variables in the model. The hypoxic ventilatory response (HVR) alone (R = 0.589, P < 0.001) or in combination with the arousal index (R = 0.625, P < 0.015 for both variables) predicted the magnitude of PA, whilst the HVR in combination with the arousal burden (R = 0.602, P < 0.001) or arousal index (R = 0.593, P < 0.002 for all variables) predicted the magnitude of vLTF. The HVR and markers of arousal are strong predictors of the magnitude of PA and vLTF. In contrast, markers of apnoea severity, including the hypoxic burden, did not add to the ability to predict the magnitude of PA or vLTF.
More Related Videos
 05:45
Experimental Approach to Examine Leptin Signaling in the Carotid Bodies and its Effects on Control of Breathing
Published on: October 25, 2019
 05:45
Delivery of In Vivo Acute Intermittent Hypoxia in Neonatal Rodents to Prime Subventricular Zone-derived Neural Progenitor Cell Cultures
Published on: November 2, 2015
Related Concept Videos
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:25
Hyperpnea and Hyperventilation
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:26
Respiratory Volumes and Capacities I
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...