Related Experiment Video
Updated: Jan 12, 2026
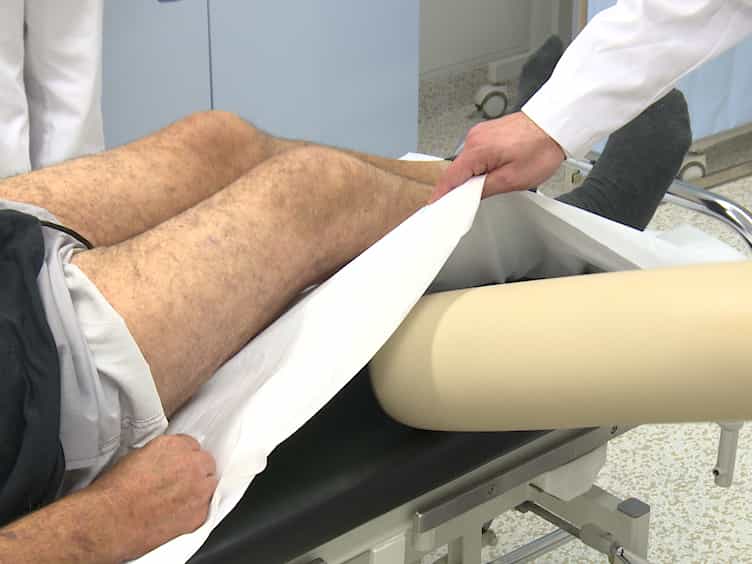
Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Periprosthetic joint infection after hemiarthroplasty for hip fracture is a distinct clinical entity associated with
Daniel P Lewis1,2,3, Seth M Tarrant1,2,3, David Dewar4,5
1Department of Traumatology, John Hunter Hospital, Newcastle, Australia.

Aims:
Periprosthetic joint infections (PJIs) are devastating complications. Our knowledge of hip fracture-associated hemiarthroplasty PJI (HHA-PJI) is limited compared to elective arthroplasty. The goal of this study was to describe the epidemiology, risk factors, management, and outcomes for HHA-PJI.
Methods:
A population-based (465,000 patients) multicentre, retrospective analysis of hip hemiarthroplasty (HHA) between January 2006 to December 2018 was conducted. PJI was defined by international consensus and treatment success as no return to operating room and survival to 90 days after the initial surgical management of the infection. Univariate, survival, and competing risk regression analyses were performed.
Results:
In total, 1,852 HHAs were identified (74% female; mean age 84 years (SD 7); 90-day mortality 16.7%). A total of 43 patients (2.3%) developed PJI at aged 77 years (SD 10) (56% female; 90-day-mortality 20.9%; hazard ratio (HR) 1.6; 95% CI 1.1 to 2.3; p = 0.023). The incidence of HHA-PJI was 0.77/100,000 population/year and 193/100,000 HHAs/year. The median time to PJI was 26 days (IQR 20 to 97), with 53% polymicrobial growth and 41% multidrug-resistant organisms (MDRO). Competing risk regression identified younger age (subdistribution hazard ratio (SHR) 0.86; 95% CI 0.8 to 0.92; p < 0.001), chronic kidney disease (SHR 3.41; 95% CI 1.36 to 8.56; p = 0.013), BMI > 35 kg/m2 (SHR 6.81; 95% CI 2.25 to 20.65; p < 0.001), perioperative urinary tract infection (SHR 1.89; 95% CI 1.02 to 3.5; p = 0.042), and dementia (SHR 9.4; 95% CI 2.89 to 30.58; p < 0.001) as significant risk factors for developing HHA-PJI. When infection treatment was successful (n = 15, 38%), median survival was 1,632 days (IQR 829 to 2,084), as opposed to 215 days (IQR 20 to 1,245) in those who failed, with a 90-day mortality of 30% (n = 12). There was no significant difference in treatment success between debridement, excision arthroplasty, or revision arthroplasty.
Conclusion:
HHA-PJI is an uncommon complication, but is significantly associated with mortality. All currently identified predictors are nonmodifiable. Due to the common polymicrobial and MDRO infections, our standard antibiotic prophylaxis may not be adequate. HHA-PJI is a different disease compared to elective PJI with distinct epidemiology, pathogens, risk factors, and outcomes, which require targeted research specific to this unique population.

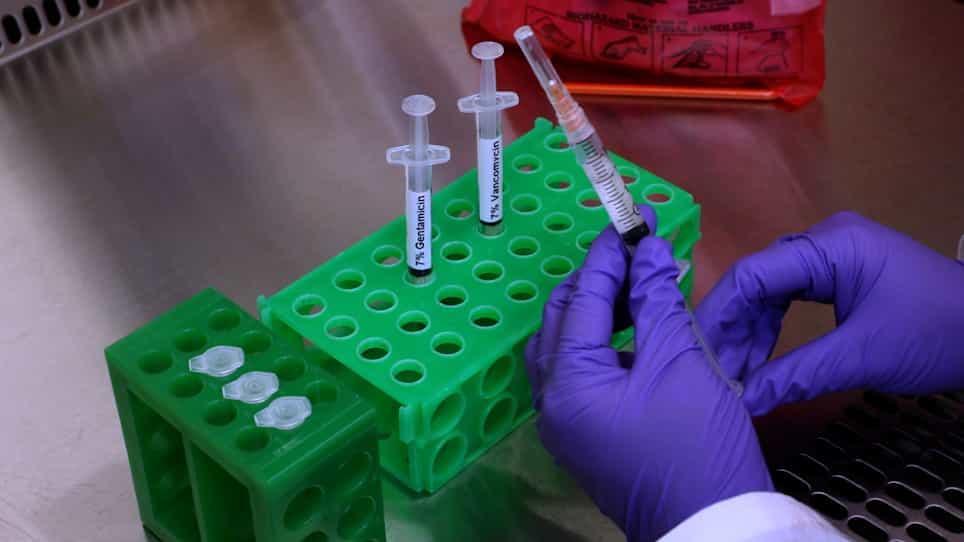
Related Concept Videos
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies.
 01:25
Endocarditis I: Introduction
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:27
Acute Pyelonephritis I: Introduction
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...