Related Experiment Video
Updated: Jan 11, 2026
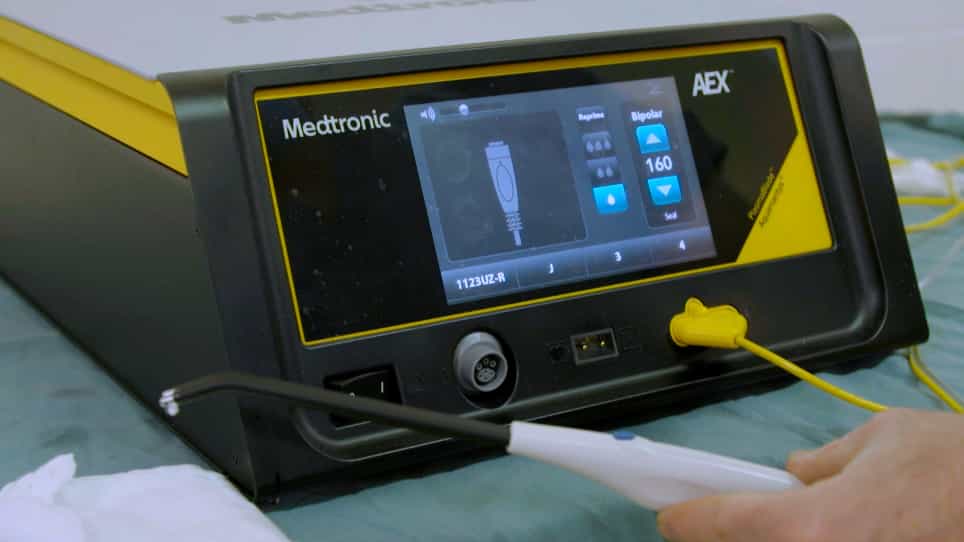

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
The incidence, treatment and evolution of vascular injuries in high-grade blunt abdominal solid organ trauma
Ellen Barnes1, James Carroll2, Sana Nasim3
1Trauma Unit, Royal Perth Hospital, Victoria Square, Perth, WA, Australia; Royal College of Surgeons Ireland, Dublin, Ireland.

Background:
Vascular injury is a major risk factor for acute and delayed haemorrhage in blunt solid organ trauma. However, the natural history, including spontaneous resolution, remains poorly described. This study evaluated the incidence, detection timing, treatment, spontaneous resolution, and outcomes of vascular injury in high-grade blunt solid organ trauma.
Methods:
A retrospective cohort study of patients with Grade III or higher splenic, hepatic, or renal injuries (2018-2023) at Western Australia's single adult major trauma centre was conducted. We recorded rates of surgery, angioembolisation, delayed haemorrhage, and the development and regression of vascular injury.
Results:
460 patients with 487 high grade solid organ injuries were admitted during the study period. Vascular injury was noted in 62.2 % of splenic injuries (n = 145/233); 24.1 % of hepatic injuries (n = 32/133) and 21.5 % of renal injuries (n = 26/121). Successful angioembolisation occurred in 61.4 % of splenic vascular injury (n = 89), 10/32 liver vascular injury and 8/26 renal vascular injury. 19 splenectomies were performed (8.2 %). Untreated vascular injury was reported in 41 splenic injuries (28.3 % of vascular injury); 13 hepatic and 15 renal injuries. Three cases of delayed haemorrhage occurred, two splenic and one hepatic; there were no clear uniting factors.
Conclusion:
Vascular injury is common in high-grade blunt solid organ trauma, particularly splenic injury. Interval inpatient imaging detects clinically relevant new vascular injury, and a substantial proportion resolve without intervention. Given the low delayed haemorrhage rate, universal post-discharge follow-up imaging seems excessive.
Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Aneurysm III: Interprofessional Care
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....