Related Experiment Video
Updated: Jan 11, 2026
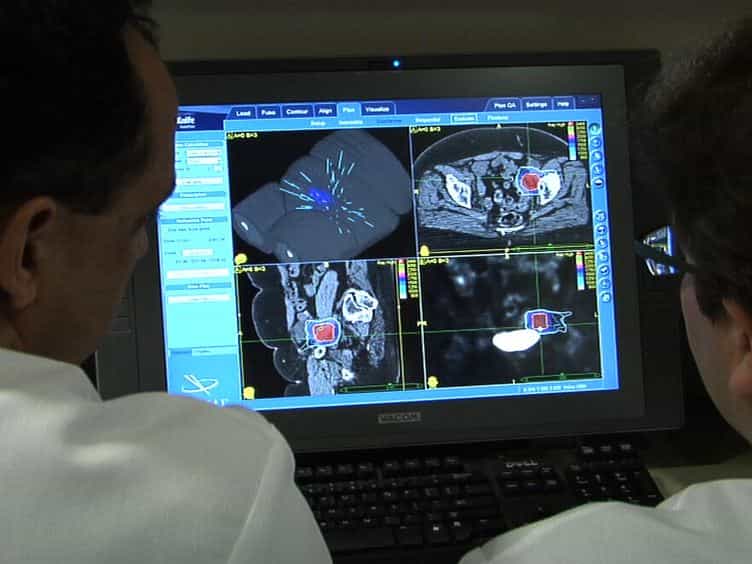
Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Re-irradiation in oligorecurrence and oligometastatic cervical cancer in modern radiotherapy era
Wiwatchai Sittiwong1, Tissana Prasartseree1, Pongpop Tuntapakul1
1Division of Radiation Oncology, Department of Radiology, Faculty of Medicine Siriraj Hospital, Mahidol University, 2 Wanglang Rd., Siriraj, Bangkok Noi, Bangkok, 10700, Thailand.

Background:
Recurrent cervical cancer remains a therapeutic challenge despite advances in primary treatment. The emerging paradigm of oligorecurrence and oligometastasis has opened avenues for curative-intent local therapies, including re-irradiation. Modern radiotherapy techniques have enabled high-dose delivery with acceptable toxicity. This study aims to assess clinical outcomes and treatment-related toxicities in patients with oligorecurrent or oligometastatic cervical cancer treated with modern re-irradiation techniques.
Methods:
This retrospective study included 20 cervical cancer patients with oligorecurrence or synchronous/metachronous oligometastases (≤ 5 lesions) who underwent at least one course of re-irradiation. Survival outcomes including locoregional recurrence-free survival (LRRFS), distant metastasis-free survival (DMFS), progression-free survival (PFS), and overall survival (OS) were estimated using Kaplan-Meier analysis. Genitourinary (GU), gastrointestinal (GI), and hematologic toxicities were assessed and graded based on CTCAE version 5.0.
Results:
The median age was 53 years (range: 33-70), with 75% initially diagnosed at FIGO 2018 stage III. The predominant histologies were squamous cell carcinoma (50%) and adenocarcinoma (45%). Recurrences most commonly involved pelvic (30%) and para-aortic (30%) lymph nodes, with 50% occurring in-field. Stereotactic body radiotherapy (SBRT), volumetric modulated arc therapy (VMAT), and MR-guided adaptive brachytherapy (MR-GABT) were the most commonly used re-irradiation modalities, employed in 95% of patients. Median times to first and second recurrence were 11.1 months (IQR: 6.0-17.3) and 13.7 months (IQR: 5.6-21.7), respectively. At a median follow-up of 33.6 months, PFS, LRRFS, DMFS, and OS rates after the first recurrence were were 31.8%, 33.6%, 60.5%, and 84.2% respectively. Grade ≥ 2 genitourinary (GU), gastrointestinal (GI), and hematologic toxicities were observed in 40%, 25%, and 55% of patients, respectively. Grade 3 hematologic toxiciy was 25% and mostly occurred during chemotherapy administration. No grade ≥ 3 GU or GI toxicities were reported. The mean accumulated D0.03 cc after re-irradiation to bladder, rectum, sigmoid and bowel for in-fied/out-of-field were 83.8 ± 6.7/78.5 ± 7.5), 71.2 ± 3.9/69.5 ± 5.2, 68.0 ± 5.5/61.0 ± 5.3, and 62.9 ± 4.6/62.4 ± 7.1 GyEQD2(3), respectively.
Conclusion:
Re-irradiation with contemporary radiotherapy techniques appears to be a feasible and effective salvage option for selected patients with limited recurrent or metastatic cervical cancer, yielding favorable survival and acceptable toxicity profiles.
More Related Videos
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
 06:20
Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
Related Concept Videos
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 02:56
Treatment Resistant Cancers