Related Experiment Video
Updated: Jan 11, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Development of a scoring system based on a nomogram to identify malignant pleural effusion
Jieying Li1, Huan Hou1, Jinming Gao1
1Department of Pulmonary and Critical Care Medicine, Peking Union Medical College Hospital, Beijing, China.

Background:
Malignant pleural effusion (MPE), a grave complication in advanced malignant tumors, indicates poor clinical outcomes. Timely diagnosis of MPE is of great significance, yet presents a clinical challenge. This study aimed to develop a scoring system based on a nomogram to distinguish MPE from benign pleural effusion (BPE).
Methods:
This single-center, retrospective study enrolled 382 patients with pleural effusion (PE) who underwent diagnostic thoracic puncture in Peking Union Medical College Hospital from December 2012 to May 2022. All participants were randomly divided into a training set (n=268) and a validation set (n=114) at a 7:3 ratio for predictive model development and internal validation. The nomogram model was established using the informative indexes screened by the least absolute shrinkage and selection operator (LASSO) regression and multivariate logistic regression. A scoring system based on this nomogram model was constructed to distinguish MPE from BPE.
Results:
The scoring system included: no fever (7 points), age/effusion adenosine deaminase (ADA) >2.5 (5 points), effusion/serum total protein (TP) ratio >0.5 (6 points), serum lactate dehydrogenase (LDH)/effusion ADA ratio [cancer ratio (CR)] >11.8 (8 points), effusion carcinoembryonic antigen (CEA) >3.6 ng/mL (10 points), and effusion LDH >154 U/L (7 points). The score showed favorable diagnostic performance in the training set [area under the curve (AUC) =0.961; 95% confidence interval (CI): 0.941-0.981], and the internal validation set (AUC =0.872; 95% CI: 0.803-0.942). At the optimal cutoff value of 28 points, the specificity and sensitivity for identifying MPE in the training set were 85.3% and 93.2%. In the internal verification set, they were 87.5% and 80.0%, respectively. The score also showed good diagnostic accuracy in differentiating MPE caused by lung cancer from BPE (training set: AUC =0.984; 95% CI: 0.971-0.998; validation set: AUC =0.914; 95% CI: 0.845-0.984). Besides, this scoring system outperformed conventional single tumor biomarkers in identifying cytologically suspected or negative malignant effusions (AUC =0.879; 95% CI: 0.812-0.945).
Conclusions:
The combination of multiple tumor markers demonstrated potential diagnostic value for MPE identification. To further improve the cost-effectiveness and applicability, we developed a simple scoring system involving six easily accessible clinical variables, which exhibited good diagnostic performance and clinical applicability for identifying MPE.
More Related Videos


Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's...
 01:23
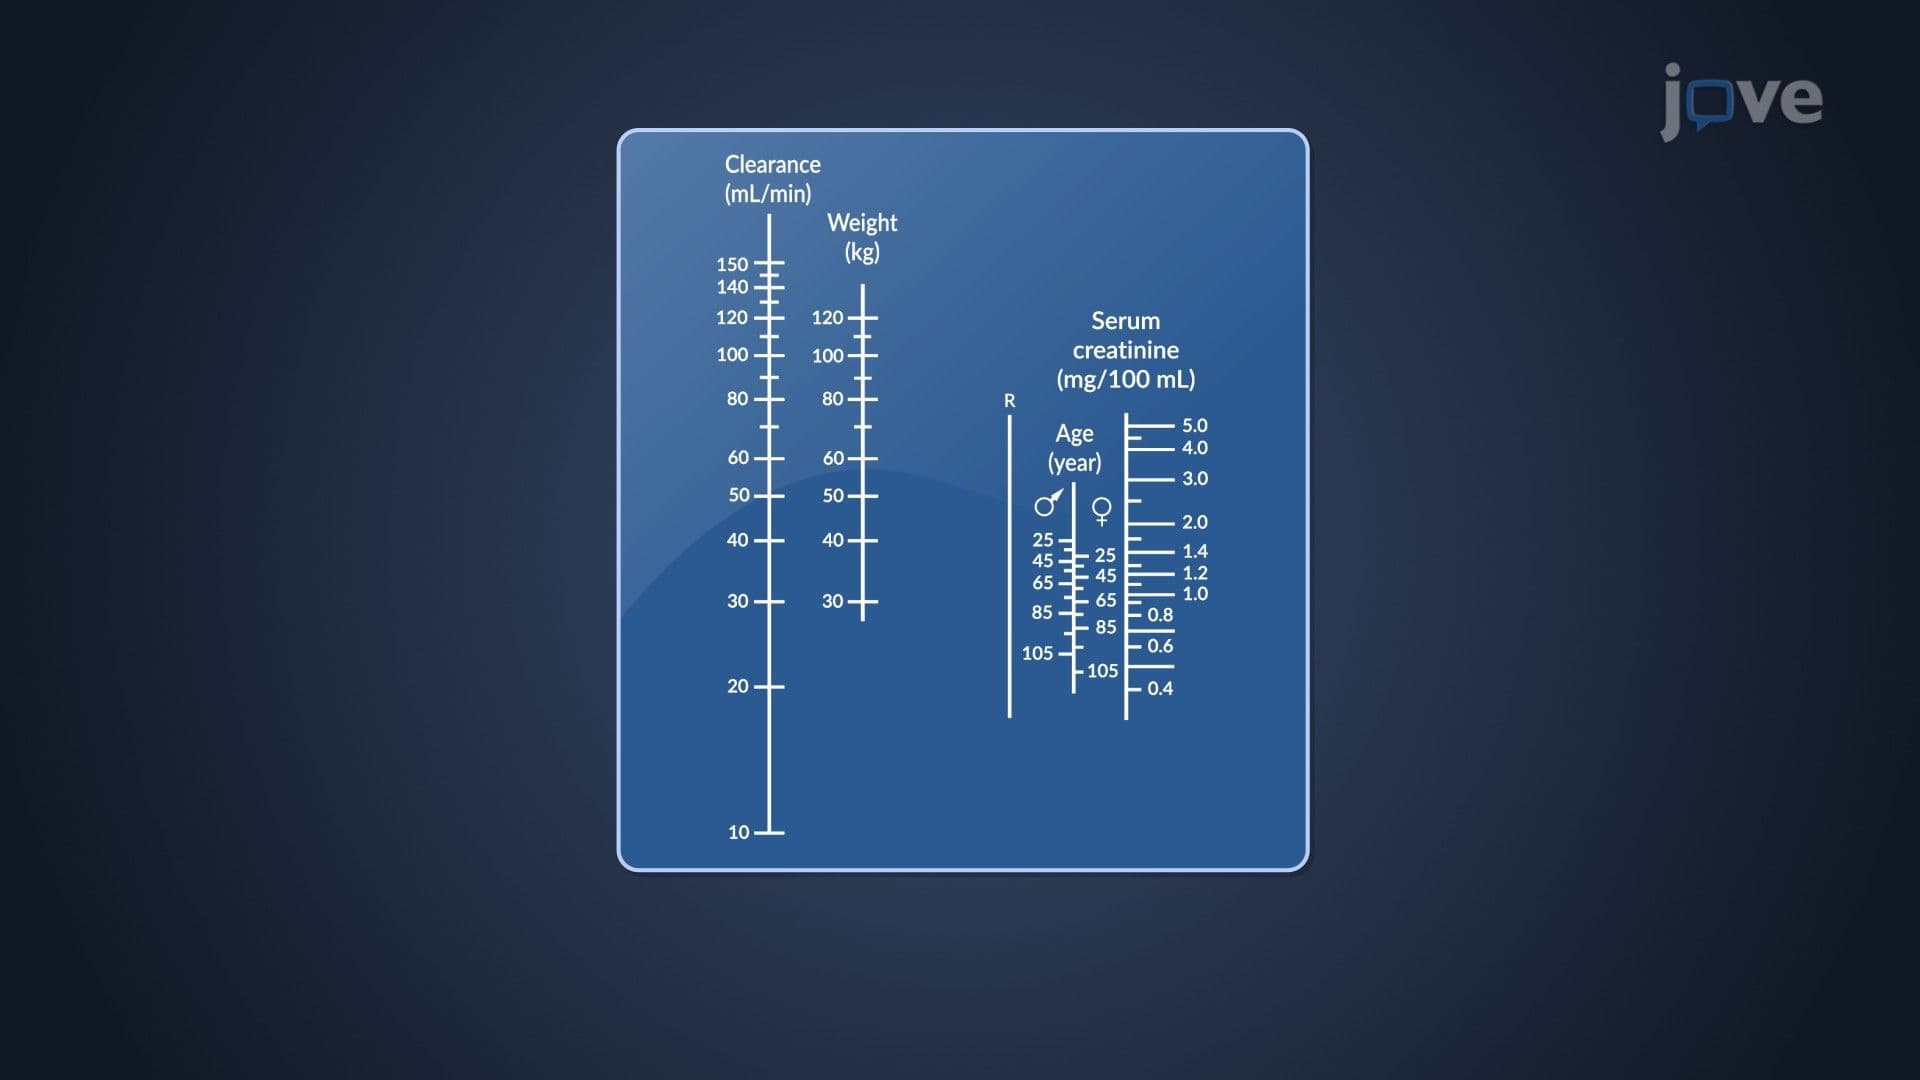
Dosage Regimen Designs: Nomograms and Tabulations
 01:30
Pneumonia III: Complications and Assessment
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due...