Related Experiment Video
Updated: Jan 11, 2026
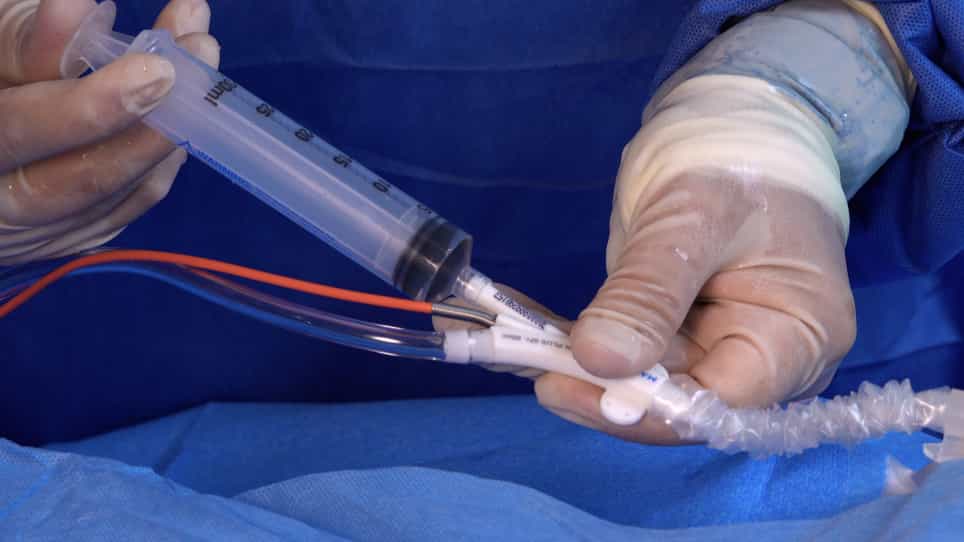

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Aortic Pulsatility Index Predicts Native Recovery in Patients With Cardiogenic Shock Supported by Intra-aortic
Kaneez Zainab1, Eric Taylor1, Nikhil Gangasani1
1Medical University of South Carolina, Charleston, SC.

Insights
A new hemodynamic marker, the assisted aortic pulsatility index (API), predicts native heart recovery in cardiogenic shock patients treated with an intra-aortic balloon pump (IABP). This finding aids in managing patients with severe heart failure.
Area of Science:
- Cardiology
- Critical Care Medicine
- Biomedical Engineering
Background:
- The intra-aortic balloon pump (IABP) is a standard therapy for cardiogenic shock (CS).
- Validated clinical markers for predicting native heart recovery in CS patients on IABP support are lacking.
- Identifying predictors of native recovery is crucial for optimizing treatment strategies and patient outcomes.
Purpose of the Study:
- To evaluate clinical and hemodynamic predictors of survival to hospital discharge with native heart recovery in CS patients requiring IABP.
- To introduce and validate a novel hemodynamic marker, the assisted aortic pulsatility index (API), for predicting native recovery.
Main Methods:
- Retrospective analysis of 267 consecutive CS patients requiring IABP support between January 2021 and November 2024.
- Hemodynamic variables, including assisted systolic blood pressure, assisted diastolic blood pressure, and pulmonary capillary wedge pressure (PCWP), were recorded at baseline, initial IABP support, and final IABP support.
- The assisted aortic pulsatility index (API) was defined as (assisted systolic blood pressure - assisted diastolic blood pressure) / PCWP.
Main Results:
- Eighty patients were included in the final analysis; in-hospital mortality was 31%.
- Native recovery occurred in 40% of patients, while 29% were bridged to advanced therapies (transplant or LVAD).
- Multivariable analysis identified final assisted API (OR 3.283, P=0.002) and acute myocardial infarction (AMI) presentation (OR 18.12, P=0.016) as significant predictors of native recovery.
- A receiver-operating characteristic curve analysis showed the final assisted API to be a strong predictor (C-statistic: 0.77, P < 0.001).
- An assisted API cutoff > 1.7 demonstrated 81% sensitivity and 64% specificity for predicting survival to native recovery.
Conclusions:
- The assisted aortic pulsatility index (API) is a novel, sensitive, and specific hemodynamic marker for predicting native recovery in CS patients supported by IABPs.
- This marker can aid clinicians in assessing the potential for native heart function recovery and guiding therapeutic decisions.
Background:
For decades, the intra-aortic balloon pump (IABP) has been a reliable and readily available pillar of therapy for cardiogenic shock (CS). However, no clinical markers have been validated that signal sufficient contractile reserve to support recovery with native heart function in this population of patients. Our aim was to assess clinical and hemodynamic predictors of survival to hospital discharge with native recovery.
Methods And Results:
We retrospectively evaluated 267 consecutive patients who presented with CS to our institution between January 2021 and November 2024 and required IABPs. Hemodynamic variables were captured at 3 different timepoints: baseline (prior to IABP insertion), initial set on support, and final set on support. A total of 80 patients were included in the final analysis. We defined the assisted aortic pulsatility index (API) as assisted systolic blood pressure-assisted diastolic blood pressure/pulmonary capillary wedge pressure (PCWP) by using data extracted from the IABP waveform. In-hospital mortality rates were 31%. Of the remainder, 40% survived to native recovery, and 29% were bridged to either transplantation or an acute or durable left ventricular assist device. Multivariable analysis identified final assisted API and acute myocardial infarction (AMI) presentation as significant predictors of survival to native recovery (final assisted API: 3.283 [1.688, 7.892]; P = 0.002; AMI presentation: 18.12 [2.121, 263.9]; P = 0.016). A receiver-operating characteristic curve was generated using the final assisted API as a predictor of the primary outcome (C-statistic: 0.77; P < 0.001). Using a final assisted API cutoff of > 1.7, this threshold was 81% sensitive and 64% specific for predicting survival to native recovery.
Conclusions:
Assisted API, a novel hemodynamic marker calculated as assisted systolic-assisted diastolic blood pressure/PCWP, was a sensitive and specific predictor of survival to native recovery in patients with CS supported by IABPs.
More Related Videos


Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:17
Aortic Regurgitation IV: Nursing Management
 01:16
Pulse
The pulse serves as a clinical...
 01:15
Aortic Regurgitation I: Introduction
 01:17
Measurement of Blood Pressure