Related Experiment Video
Updated: Jan 11, 2026
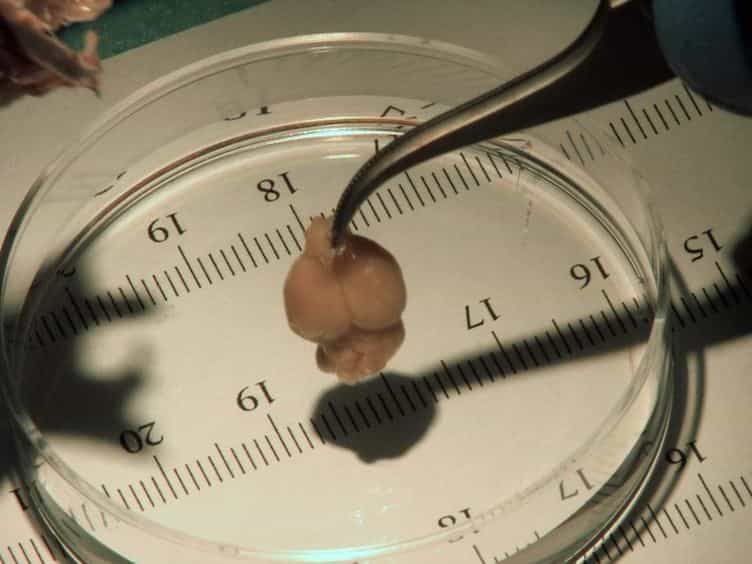

Intravascular Perfusion of Carbon Black Ink Allows Reliable Visualization of Cerebral Vessels
Published on: January 4, 2013
Prolonged Venous Transit on Perfusion Imaging: An Evolving Marker of Outcomes in Large Vessel Occlusion Stroke: A
Jay Kakadiya1, Dhairya A Lakhani2, Hamza A Salim3
1From the Department of Radiology and Radiological Sciences (J.K., H.L., V.S.Y.), Division of Neuroradiology, Johns Hopkins University, Baltimore, Maryland.

Prolonged venous transit (PVT) on perfusion imaging is an emerging venous outflow (VO) biomarker exhibiting microvascular integrity and downstream venous drainage. Conventional arterial parameters such as time to maximum (Tmax), CBF, and CBV often fail to capture postrecanalization microcirculatory dysfunction that contributes to infarct progression and poor outcomes in anterior circulation ischemic stroke. A comprehensive literature review was conducted to evaluate the clinical, radiologic, and functional implications of PVT, factors influencing its status, and predictive models integrating PVT with other perfusion metrics in patients with acute ischemic stroke due to large vessel occlusion (AIS-LVO) undergoing mechanical thrombectomy. Across studies, PVT-positive status (delayed dural sinus opacification, Tmax ≥10 seconds) correlated with higher admission and discharge NIHSS, longer hospital stay, larger Tmax >6 seconds and mismatch volumes, and worse 90-day outcomes (mRS 3-6). PVT-positive status independently predicted mortality and poor functional recovery, with advanced age and higher NIHSS as associated factors. Compared with other imaging markers, PVT demonstrated superior predictive performance for functional outcomes (AUC up to 0.821), further enhanced when combined with CBV index (AUC 0.831). PVT offers a reproducible, easily interpretable imaging marker of delayed venous outflow due to microvascular dysfunction, providing superior prognostic value beyond arterial parameters and supporting its inclusion in AIS-LVO imaging assessment.
Prolonged venous transit (PVT) on perfusion imaging is an emerging venous outflow (VO) biomarker exhibiting microvascular integrity and downstream venous drainage. Conventional arterial parameters such as time to maximum (Tmax), CBF, and CBV often fail to capture postrecanalization microcirculatory dysfunction that contributes to infarct progression and poor outcomes in anterior circulation ischemic stroke. A comprehensive literature review was conducted to evaluate the clinical, radiologic, and functional implications of PVT, factors influencing its status, and predictive models integrating PVT with other perfusion metrics in patients with acute ischemic stroke due to large vessel occlusion (AIS-LVO) undergoing mechanical thrombectomy. Across studies, PVT-positive status (delayed dural sinus opacification, Tmax ≥10 seconds) correlated with higher admission and discharge NIHSS, longer hospital stay, larger Tmax >6 seconds and mismatch volumes, and worse 90-day outcomes (mRS 3-6). PVT-positive status independently predicted mortality and poor functional recovery, with advanced age and higher NIHSS as associated factors. Compared with other imaging markers, PVT demonstrated superior predictive performance for functional outcomes (AUC up to 0.821), further enhanced when combined with CBV index (AUC 0.831). PVT offers a reproducible, easily interpretable imaging marker of delayed venous outflow due to microvascular dysfunction, providing superior prognostic value beyond arterial parameters and supporting its inclusion in AIS-LVO imaging assessment.

Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:19
Imaging Studies VII: Vascular Imaging