Related Experiment Video
Updated: Jan 11, 2026
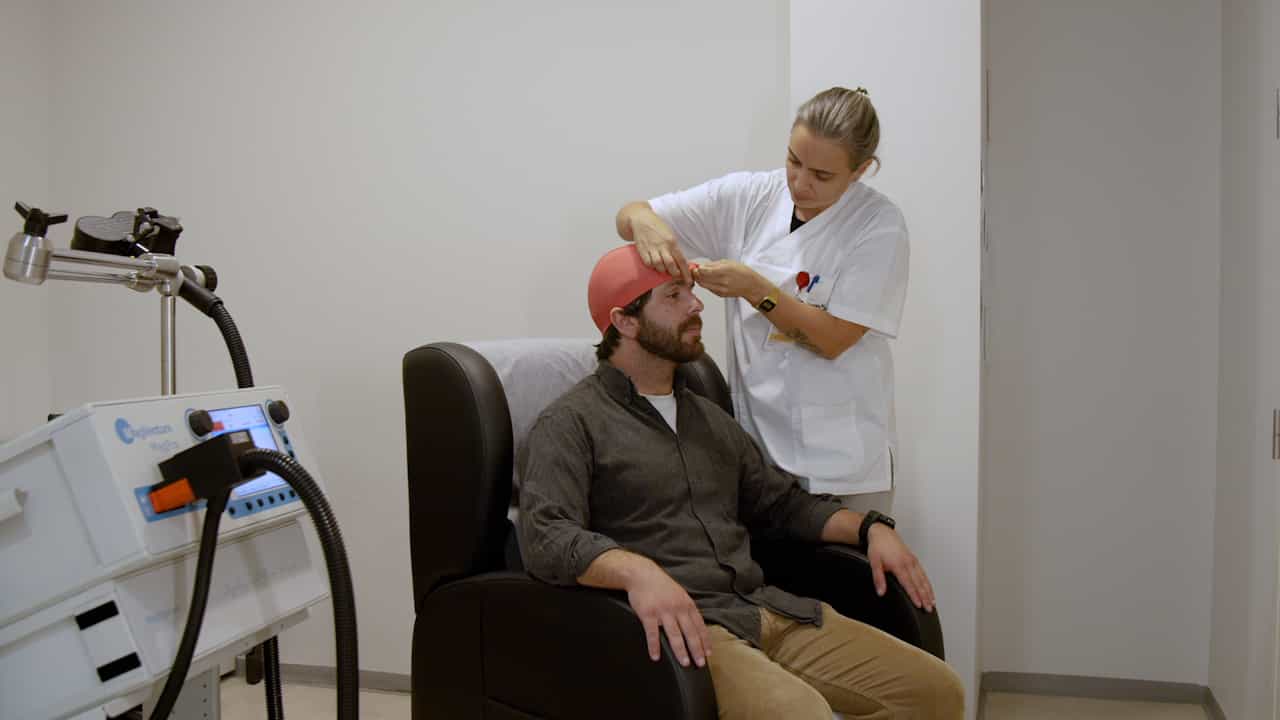

Conventional Repetitive Transcranial Magnetic Stimulation for Depression: A Step-by-Step Protocol
Published on: November 21, 2025
Effectiveness of transcranial magnetic stimulation for posttraumatic stress disorder: A multisite, propensity-matched
Yosef M Berlow1, Samantha L Cilli2, F Andrew Kozel3
1Center for Neurorestoration and Neurotechnology, VA Providence Healthcare System, Providence, RI, USA; Department of Psychiatry and Human Behavior, Alpert Medical School of Brown University, Providence, RI, USA.

Background:
Transcranial magnetic stimulation (TMS) is increasingly used off-label for posttraumatic stress disorder (PTSD), often applying protocols developed for depression. While prior studies suggest high-frequency TMS can improve PTSD symptoms, few have been adequately powered to compare protocols. We examined whether three common TMS protocols yield equivalent outcomes for PTSD in a large, multisite cohort of veterans.
Methods:
Clinical outcomes were analyzed from 756 veterans with comorbid PTSD and depression treated with antidepressant TMS across multiple VA sites. Protocols included left prefrontal 10 Hz TMS (n = 526), left prefrontal intermittent theta burst TMS (iTBS; n = 71), and deep TMS (dTMS; n = 61). PTSD symptoms were measured with the PTSD symptom checklist for DSM-5 (PCL-5). Primary outcomes included PTSD response (>10-point reduction) and remission (PCL-5 <33). Propensity score matching adjusted for baseline differences. Equivalence was set at 10 % for categorical outcomes and Cohen's d = 0.25 for continuous outcomes. Depression outcomes were also analyzed.
Results:
All three TMS protocols produced substantial PTSD symptom reductions (18-22 points). PTSD response rates were 63 % (10 Hz), 65 % (iTBS), and 78 % (dTMS); remission rates were 47 %, 48 %, and 49 %, respectively. Both iTBS and dTMS were noninferior to 10 Hz (all ps < 0.05). Depression outcomes demonstrated similar patterns.
Discussion:
In this large multisite cohort study of veterans with PTSD and depression, 10 Hz, iTBS, and dTMS protocols demonstrated comparable clinical effectiveness. Limitations are those inherent to cohort studies of veterans. These findings support the effectiveness of TMS for PTSD, and protocol selection based on patient-specific or logistical considerations rather than efficacy differences.

