Related Experiment Video
Updated: Jan 11, 2026


Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Bone density, structure, and estimated strength in children with congenital heart disease. A CHAMPS* cohort study
Marta C Erlandson1, Matthew S Chapelski1, Chantelle L Baril1
1College of Kinesiology, University of Saskatchewan, Canada.

Insights
Children with congenital heart disease (CHD) exhibit poorer bone structure in their limbs compared to typically developing peers (TDP). Complex CHD lesions are linked to significantly worse bone density, structure, and strength, increasing fracture risk.
Area of Science:
- Pediatric Orthopedics
- Cardiology
- Bone Biology
Background:
- Children with congenital heart disease (CHD) often have reduced physical activity, lower birth weights, and poorer nutrient intake.
- These factors increase the risk of impaired skeletal development in children with CHD compared to typically developing peers (TDP).
Purpose of the Study:
- To assess and compare bone architecture in children with CHD versus TDP.
- To evaluate differences in bone parameters based on CHD lesion complexity.
Main Methods:
- Peripheral quantitative computed tomography (pQCT) scans of the radius and tibia were performed on 42 children with CHD and 41 TDP (ages 7-15).
- Bone parameters were analyzed using MANCOVA, controlling for sex, age, height, weight, maturity, and physical activity.
Main Results:
- No significant differences in distal bone parameters were found between CHD and TDP groups.
- Children with CHD showed significantly lower total area, cortical content, cortical area, cortical thickness, and polar stress-strain index at the radial and tibial shaft compared to TDP.
- Complex CHD lesions were associated with significantly worse bone parameters and greater cortical density at the radial and tibial shaft compared to TDP.
Conclusions:
- Children with complex CHD demonstrate poorer bone architecture at the radial and tibial shaft compared to TDP.
- Complex CHD lesions may elevate the risk of impaired bone density, structure, and estimated strength, potentially increasing fracture risk.
Introduction:
Children with congenital heart disease (CHD) have lower levels of physical activity, lower birth weights, and lower nutrient intake compared to their typically developing peers (TDP); which can put children with CHD at increased risk of impaired skeletal development. Therefore, the purpose of this study was to assess the bone architecture of children with CHD compared to TDP. Our secondary objective was to evaluate differences between CHD lesion complexity.
Methods:
Forty-two children with CHD 7 to 15 years of age (10.9±2.5) were age and sex-matched to 41 TDP. Peripheral quantitative computed tomography (pQCT) scans were obtained at the distal (4%) and shaft (65%, 66%) sites for the radius and tibia, respectively. pQCT bone parameters were compared between groups using multiple analysis of covariance (MANCOVA), using sex, age, height, weight, maturity, and physical activity as covariates.
Results:
There were no significant differences between children with CHD and TDP at the distal radius or distal tibia (p>0.05). Children with CHD had significantly lower total area, cortical content, cortical area, cortical thickness, and polar stress-strain index at the radial and tibial shaft compared to TDP (p<0.05). When sub-dividing children with CHD by lesion severity, the complex CHD group had significantly lower cortical content, cortical area, cortical thickness, and polar stress-strain index at the radius and tibia shaft when compared to TDP (p<0.05). Additionally, children with complex lesions had greater cortical density at the radius and tibia shaft when compared to TDP (p<0.05). Finally, children with simple lesions had greater cortical density at the radius shaft when compared to TDP (p<0.05).
Conclusion:
Children with complex CHD had worse bone parameters when compared to TDP. Children with complex CHD lesions may be at increased risk of impaired bone density, structure, and estimated strength at both the radius and tibia shaft.


Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:55
Bone Structure
 01:24
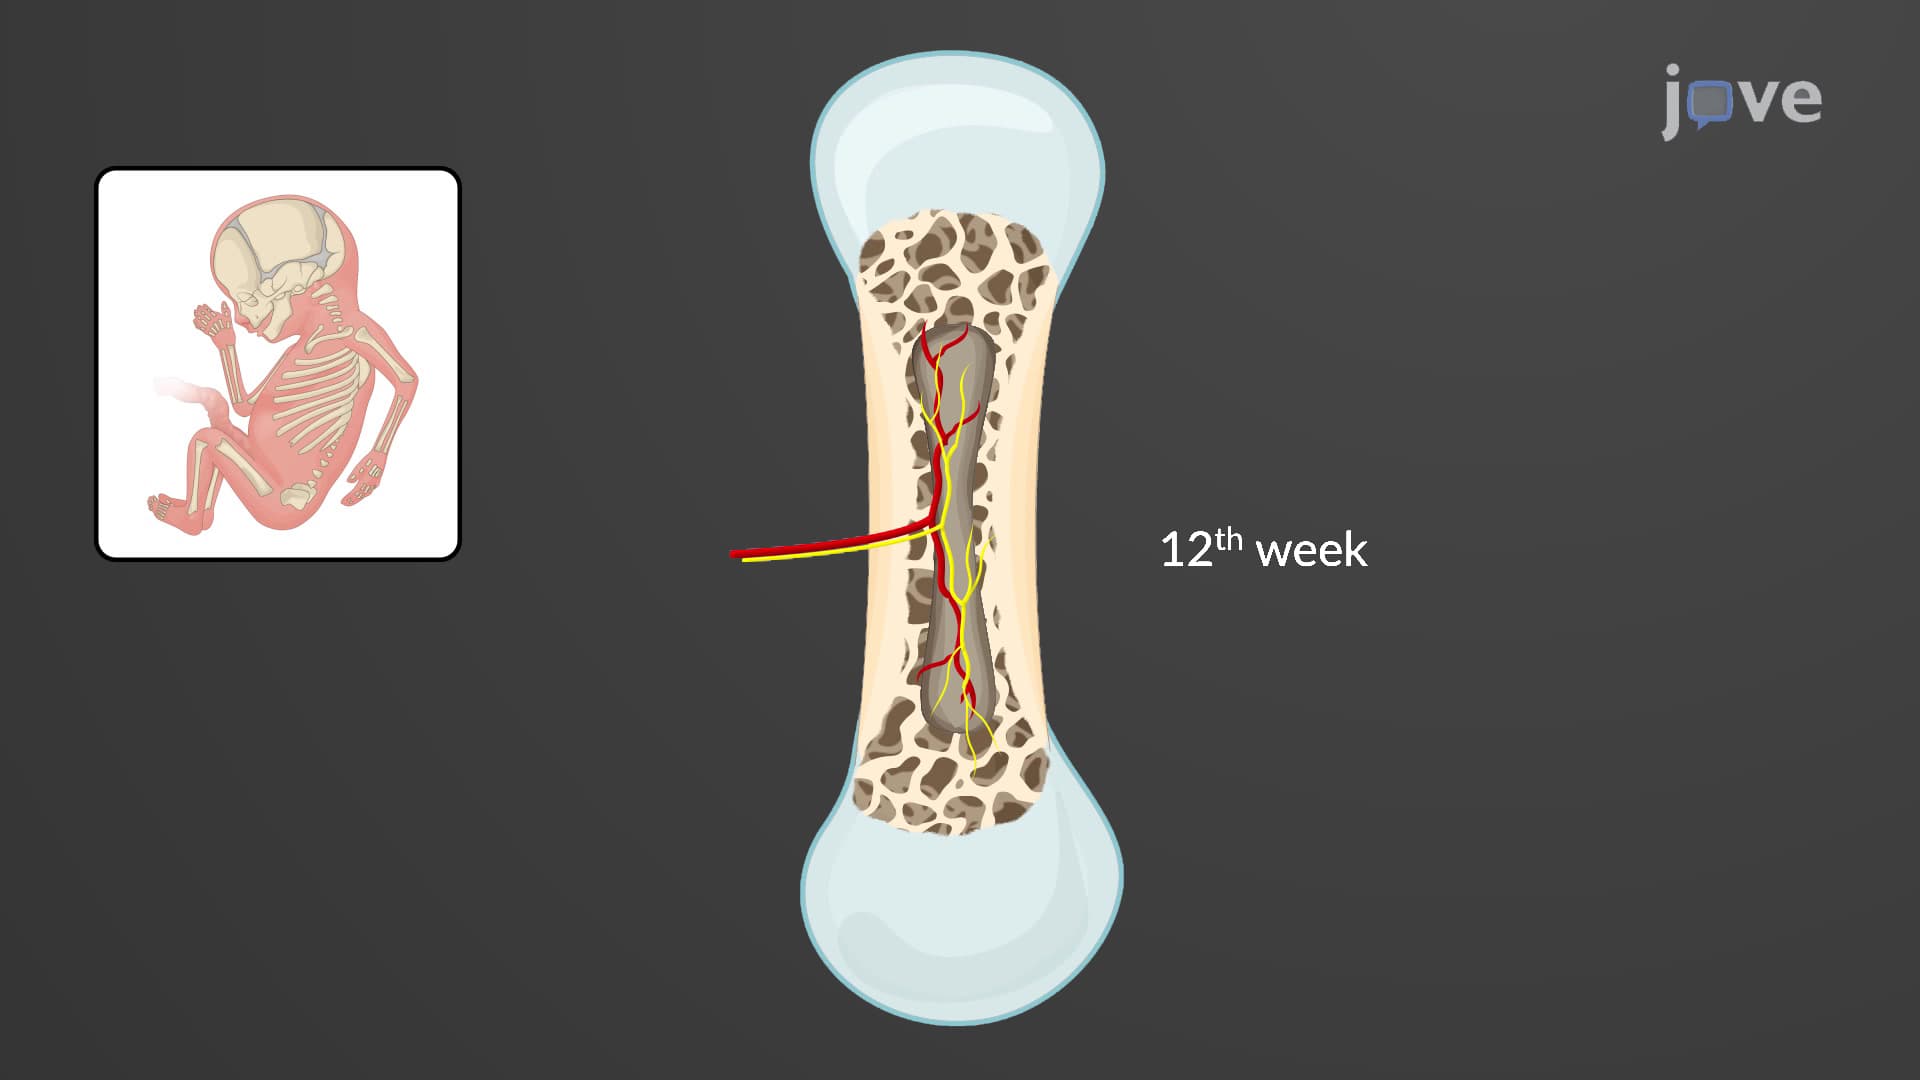
Bone Formation by Endochondral Ossification
 01:27
Compact Bone
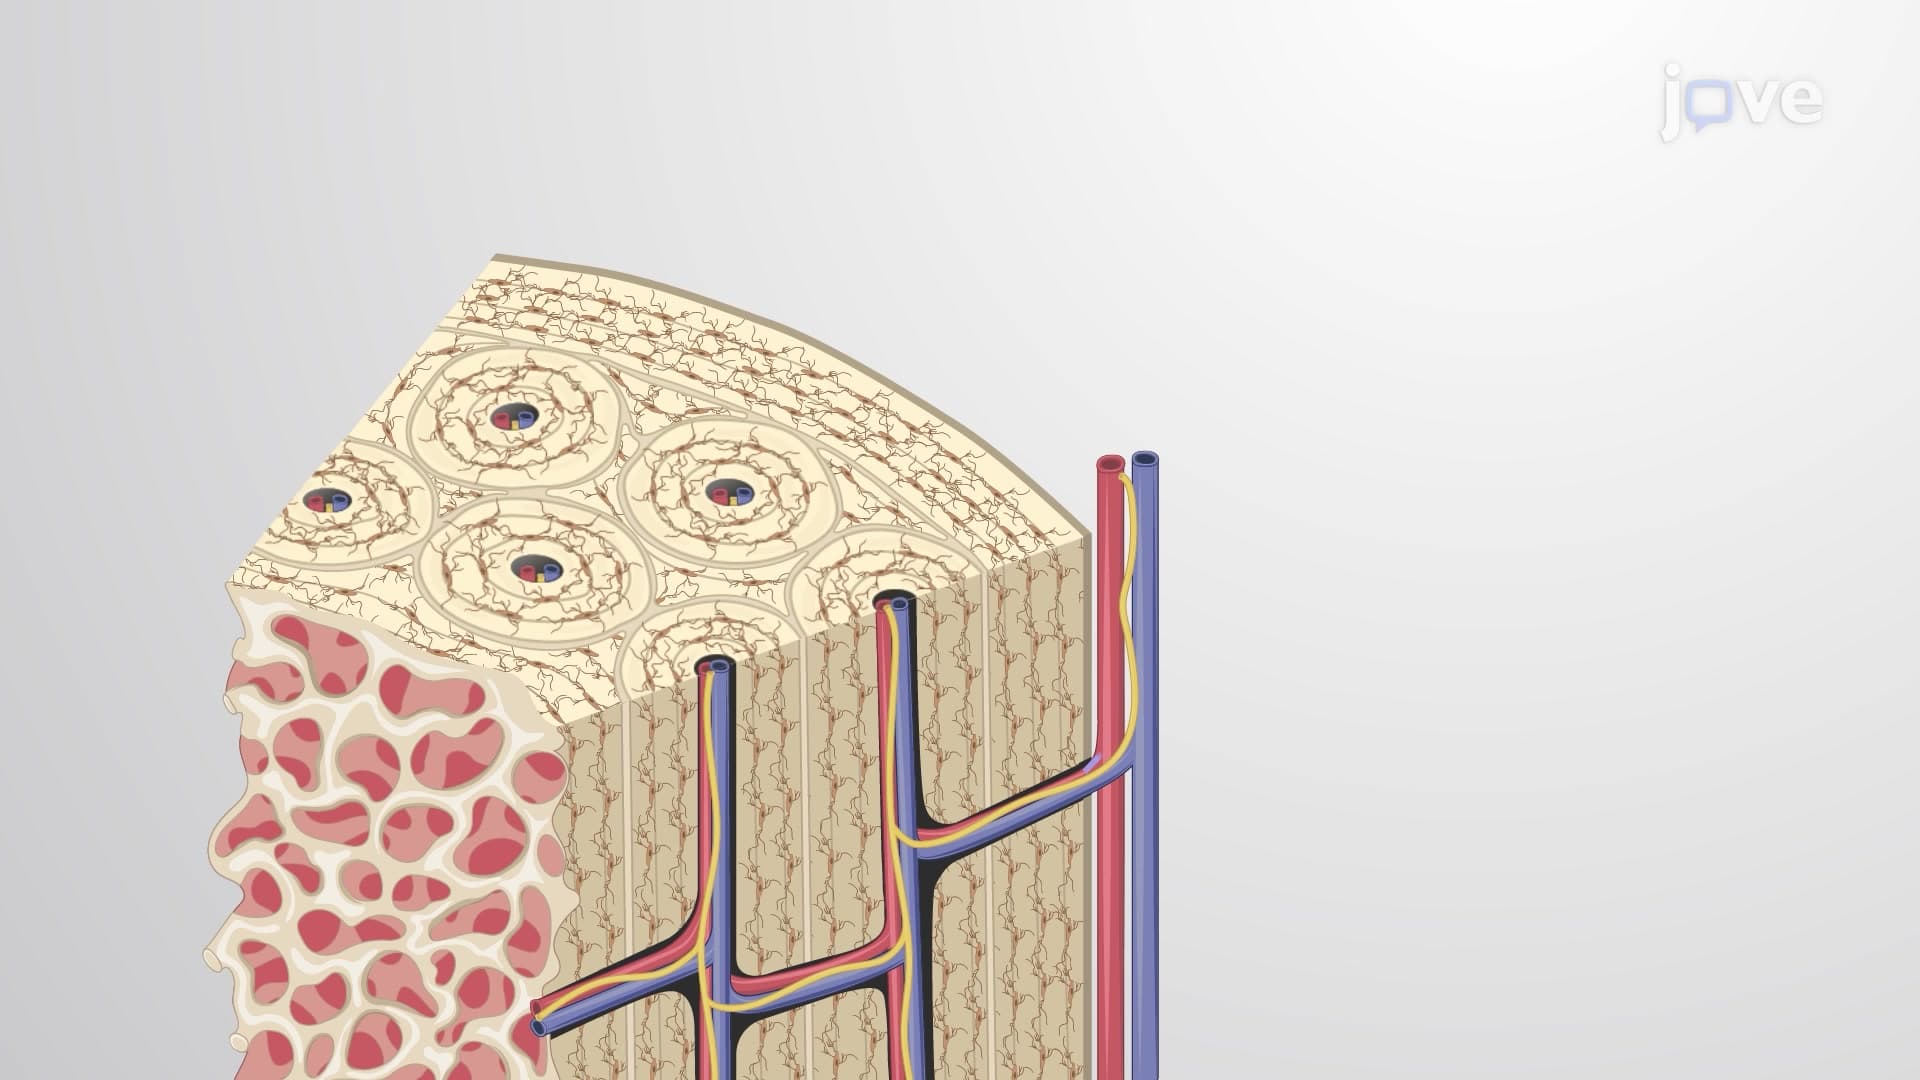
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:27
Growth of Cartilage and Bone Tissue
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...