Related Experiment Video
Updated: Jan 11, 2026
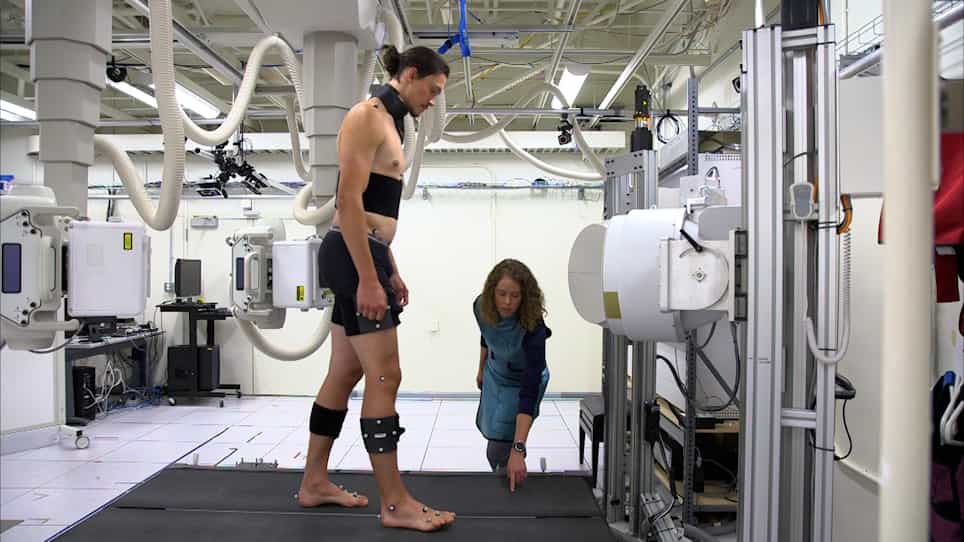

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Kinematic alignment without femoral cartilage-wear compensation for apex-distal joint line obliquity: Effects on
Tsutomu Maeda1,2, Theodore Derek Vernon Cooke3, Mitsuhiko Kubo4
1Department of Orthopaedic Surgery Shiga General Hospital Moriyama Shiga Japan.

Purpose:
Pronounced apex-distal joint line obliquity (JLO) complicates total knee arthroplasty (TKA) by challenging patellofemoral tracking and medial tibial bone support. Joint line obliquity-modified kinematic alignment (JLO-KA)-a selective modification of kinematic alignment (KA) that omits femoral cartilage-wear compensation and reallocates correction to the tibial side-was developed. This study quantified postoperative component and limb alignment with JLO-KA versus true KA.
Methods:
Retrospective comparison of 20 JLO-KA knees and 15 true-KA knees with preoperative apex-distal JLO (CPAK I-III). Pre-/postoperative computed tomography (CT) measured lateral distal femoral angle (LDFA), medial proximal tibial angle (MPTA), femoral component rotation (FCR), arithmetic hip-knee-ankle angle (aHKA), and JLO; postoperative Coronal Plane Alignment of the Knee (CPAK) distribution was analysed (Δ = JLO-KA minus true KA).
Results:
Groups were similar at baseline: preoperative LDFA 87.7° versus 87.6°, MPTA 83.5° versus 83.5°, aHKA -4.3° versus -4.1°, JLO 171.2° versus 171.2° (all p > 0.05). Postoperatively, JLO-KA increased LDFA to 90.4° ± 2.3° versus 87.0° ± 1.9° (Δ = +3.4°, 95% confidence interval [CI]: 1.9-4.8; p < 0.0001), MPTA to 88.0° ± 1.4° versus 85.6° ± 2.0° (Δ = +2.4°, 1.1-3.7; p = 0.0015), and FCR to 3.1° ± 2.0° versus 0.1° ± 2.0° (Δ = +2.9°, 1.5-4.3; p = 0.0002), while aHKA was similar (-2.4° ± 3.1° vs. -1.4° ± 2.8°; Δ = -1.0°; p = 0.324). JLO was closer to neutral with JLO-KA (178.4° ± 2.2° vs. 172.7° ± 2.8°; Δ = +5.8°; p < 0.001). Neutral-JLO CPAK types (IV-VI) occurred in 16/20 (80%) versus 2/15 (13%) (p = 0.00013). The restricted KA 90° ± 5° range for LDFA and MPTA was met by 19/20 (95%) versus 7/15 (47%) (p = 0.0019).
Conclusion:
Reallocating cartilage-wear compensation from the medial femur to the medial tibia within the same calliper-verified workflow reduced femoral valgus, limited tibial varus, and increased femoral external rotation by ≈3° while maintaining aHKA. Shifts were consistent with lateralizing the prosthetic trochlear groove and preserving medial tibial bone support, positioning JLO-KA as a targeted option for apex-distal knees (CPAK I-III).
Level Of Evidence:
Level III, retrospective comparative study.
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:16
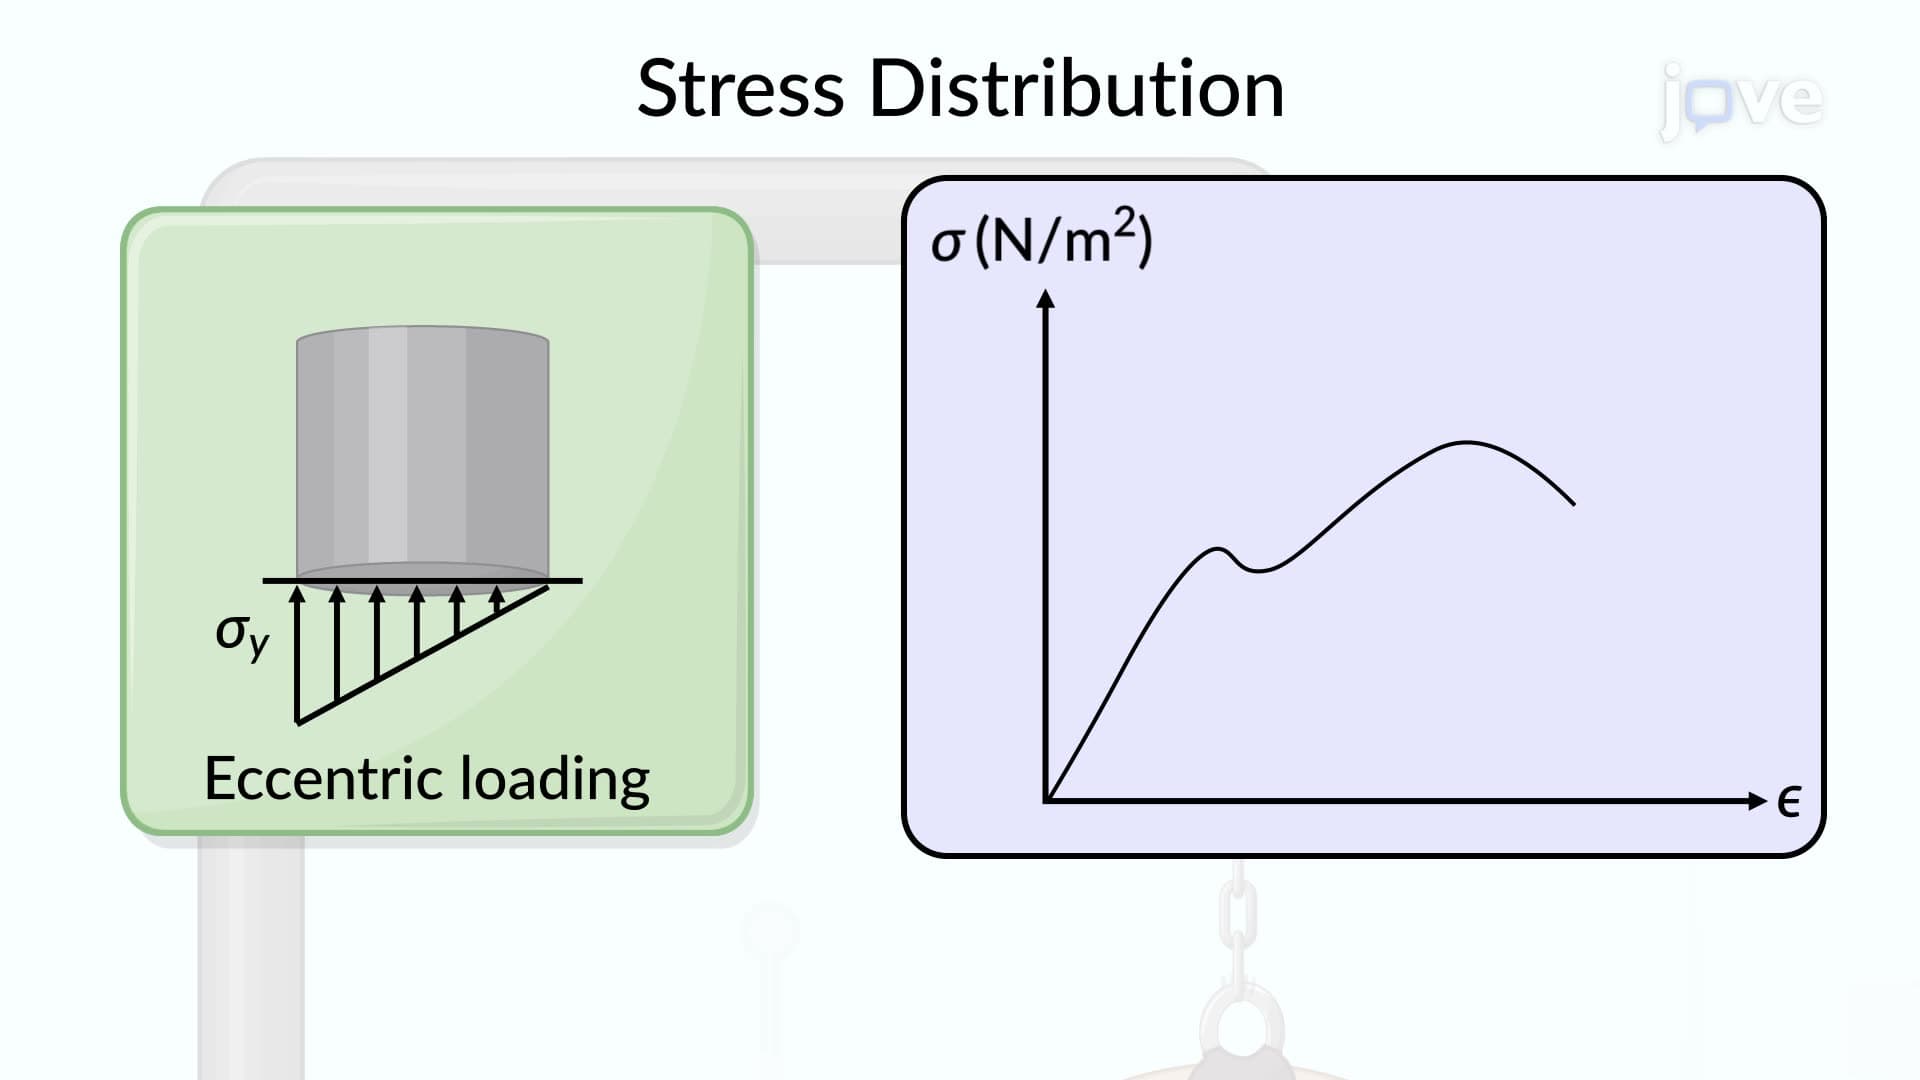
Eccentric Axial Loading in a Plane of Symmetry
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris...
 01:30
Kinematic Equations for Rotation
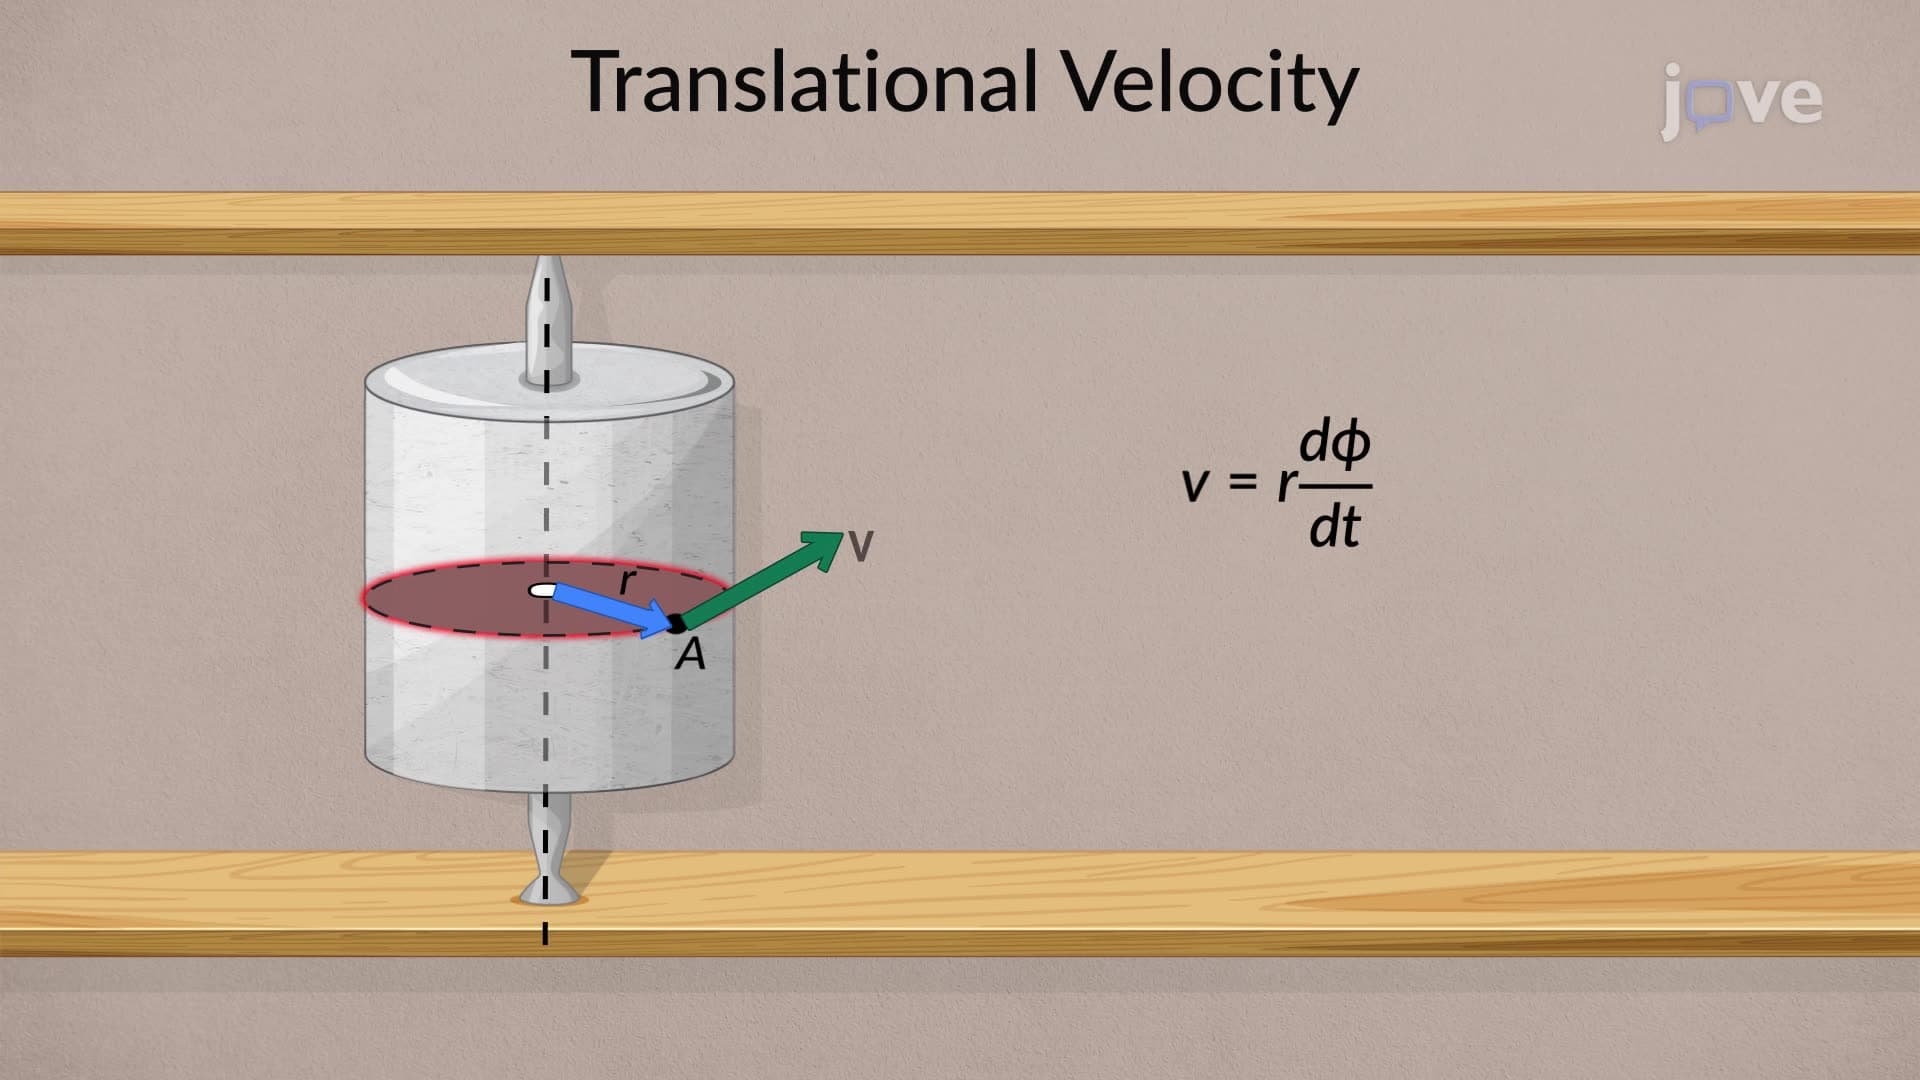
For instance, imagine a point A on a rigid body engaged in circular motion. The translational velocity of this particular point can be calculated by taking the time derivatives of the displacement equation, which essentially measures the...
 01:10
Deformation in a Circular Shaft
 01:07
Development of the Limb Synovial Joints
The mesenchymal stem cells differentiate into chondrocytes that form the hyaline cartilage, and later the cartilaginous model of the bone. This model further transforms into a bone. This process is known as endochondral ossification.
During development, the limbs...