Related Experiment Video
Updated: Jan 11, 2026
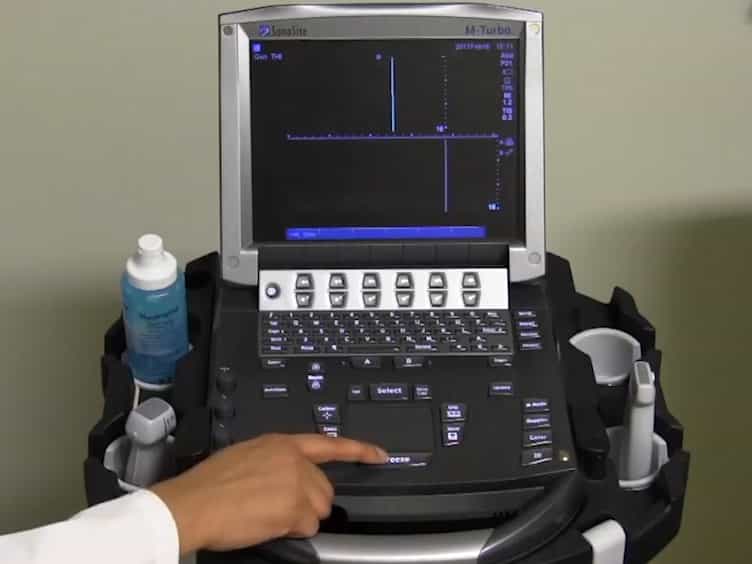
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Optimal fluid management strategies in patients with heart failure: a systematic review and meta-analysis of
Umar G Adamu1, Blessing Muponda1, Nqoba Tsabedze1
1Division of Cardiology, Department of Internal Medicine, School of Clinical Medicine, Faculty of Health Sciences, University of the Witwatersrand, Johannesburg, South Africa.

Background:
Fluid restriction is frequently recommended in heart failure (HF) management to prevent volume overload and improve clinical outcomes. However, the evidence supporting this practice remains limited. This meta-analysis aimed to evaluate the impact of fluid restriction vs. liberal fluid intake on clinical and patient-centered outcomes in individuals with HF.
Methods:
A systematic search of PubMed, Embase, Cochrane Library, and ClinicalTrials.gov was conducted through April 27, 2025, to identify randomized controlled trials (RCTs) comparing restrictive and liberal fluid strategies in HF. Pooled risk ratios (RRs) for binary outcomes and weighted mean differences (WMDs) for continuous outcomes with 95% confidence intervals (CIs) were calculated using a random-effects model.
Results:
Four RCTs with a total of 747 patients were included, of whom 378 (50.6%) were randomized to liberal fluid intake. There were no significant differences between groups regarding all-cause mortality (RR: 1.71; 95% CI: 0.37-3.72; p = 0.27), HF rehospitalization (RR: 0.71; 95% CI: 0.46-1.10; p = 0.13) or thirst (WMD: 4.78; 95% CI: -6.72 to -16.28; p = 0.42). Patients in the fluid restriction group had significantly lower fluid intake (WMD: -361.84 mL/day; 95% CI: -552.89 to -170.78; p < 0.001), lower Kansas City Cardiomyopathy Questionnaire (KCCQ) Clinical summary score (WMD: -361.84; 95% CI: -552.89 to -170.78; P < 0.001), and lower adherence (WMD: 16.47; 95% CI: 6.45-26.50; p = 0.001). No significant differences were observed between groups in terms of acute kidney injury, weight loss, or patient-reported quality of life.
Conclusions:
In this meta-analysis, fluid restriction significantly reduced total fluid intake but did not improve clinical outcomes in patients with HF. Adherence and KCCQ clinical summary scores were higher with liberal fluid intake. These findings support an individualized approach to fluid management in patients with HF.
Systematic Review Registration:
PROSPERO CRD420251048914.


Related Concept Videos
 01:30
Heart Failure V: Medical Management
 01:22
Heart Failure Drugs: Diuretics
 01:22
Heart Failure VI: Adjunct Therapies
 01:30
Heart Failure VII: Nursing Interventions
 01:28
Mitral Regurgitation IV: Nursing Management
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System