Related Experiment Video
Updated: Jan 11, 2026


Minimally Invasive Cisterna Magna Injection Model for Leptomeningeal Metastasis Studies in Mice
Published on: May 23, 2025
Spinal Cord Leptomeningeal Enhancement as a Marker of Extensive Spinal Cord Involvement in Children With MOGAD
Serenella Bartiromo1,2, Cesar Alves3, Julia O'Mahony4
1Department of Medicine, University of Ottawa, Ottawa Hospital Research Institute, Canada.

Background And Objectives:
Spinal cord leptomeningeal enhancement (LME) can be observed in children with myelin oligodendrocyte glycoprotein antibody-associated disease (MOGAD) and with seronegative myelitis. We investigated whether the presence of spinal cord LME in MOGAD and seronegative myelitis is associated with distinct clinical, CSF, and MRI findings.
Methods:
Study participants were identified among the 490 children and adolescents recruited to the Canadian Pediatric Demyelinating Disease study following an incident attack of CNS demyelination. Inclusion criteria for this study were: (1) evidence of spinal cord lesions on MRI, (2) available postgadolinium MRI sequences, and (3) available MOG and aquaporin-4 (AQP4) antibody results. None of the AQP4 antibody-positive participants met our inclusion criteria and only 1 participant with multiple sclerosis exhibited LME. We therefore focused the study on children with MOGAD and seronegative myelitis and compared the clinical, CSF, and MRI features between participants with and without LME.
Results:
Our cohort included 33 participants with MOGAD (median age 5.9 years, 55% women) and 45 with seronegative myelitis (median age 11.9 years, 33% women). Spinal cord LME was detected in 20/33 (61%) participants with MOGAD and 14/45 (31%) with seronegative myelitis. Among children with MOGAD, those with LME were more likely than those without LME to have longitudinally extensive myelitis ([LETM], 19/20 vs 8/13, p = 0.024); H-sign (15/20 vs 5/13, p = 0.036), tumefactive cord lesions (10/20 vs 1/13, p = 0.021); complete cross-sectional involvement (16/20 vs 5/13, p = 0.026); nodular lesional enhancement (7/20 vs 0/13, p = 0.026); and more spinal cord lesions (p = 0.036). LME in MOGAD was not associated with greater CSF protein content or cell count nor predicted relapse rate or clinical recovery. Children with seronegative myelitis and LME were more likely than those without LME to have tumefactive lesions (6/14 vs 4/31, p = 0.048) and complete cross-section involvement (11/14 vs 13/31, p = 0.028) but did not differ in terms of H-sign, LETM, lesional enhancement, or number of lesions.
Discussion:
The presence of spinal cord LME is associated with more extensive spinal cord abnormalities on MRI in children with MOGAD and to a lesser extent in those with seronegative myelitis. The biological underpinnings of this finding and its clinical implications should be assessed in further studies.
Insights
Spinal cord leptomeningeal enhancement (LME) is more common in children with myelin oligodendrocyte glycoprotein antibody-associated disease (MOGAD) and indicates more extensive spinal cord abnormalities on MRI. This finding is also present to a lesser extent in seronegative myelitis.
Area of Science:
- Pediatric neurology
- Neuroimmunology
- Neuroradiology
Background:
- Spinal cord leptomeningeal enhancement (LME) is a potential imaging biomarker in pediatric CNS demyelinating diseases.
- Distinguishing between myelin oligodendrocyte glycoprotein antibody-associated disease (MOGAD) and seronegative myelitis is crucial for diagnosis and management.
- The association between LME and specific clinical, CSF, and MRI findings in these pediatric populations is not well-defined.
Purpose of the Study:
- To investigate the association between spinal cord LME and distinct clinical, cerebrospinal fluid (CSF), and magnetic resonance imaging (MRI) findings in children with MOGAD and seronegative myelitis.
- To compare the characteristics of LME in MOGAD versus seronegative myelitis.
- To determine if LME predicts disease severity or relapse in pediatric demyelinating diseases.
Main Methods:
- Retrospective analysis of 33 children with MOGAD and 45 with seronegative myelitis from the Canadian Pediatric Demyelinating Disease study.
- Inclusion criteria: spinal cord lesions on MRI, available postgadolinium sequences, and MOG/AQP4 antibody results.
- Comparison of clinical, CSF, and MRI features between participants with and without spinal cord LME.
Main Results:
- Spinal cord LME was detected in 61% of MOGAD cases and 31% of seronegative myelitis cases.
- In MOGAD, LME was associated with longitudinally extensive myelitis, H-sign, tumefactive lesions, complete cross-sectional involvement, nodular enhancement, and more lesions.
- In seronegative myelitis, LME was associated with tumefactive lesions and complete cross-sectional involvement, but not H-sign or LETM.
Conclusions:
- Spinal cord LME is linked to more extensive spinal cord abnormalities on MRI in pediatric MOGAD and, to a lesser degree, in seronegative myelitis.
- The underlying biological mechanisms and clinical significance of LME warrant further investigation.
- LME may serve as an imaging marker for disease severity in pediatric demyelinating conditions.
Related Concept Videos
 01:19
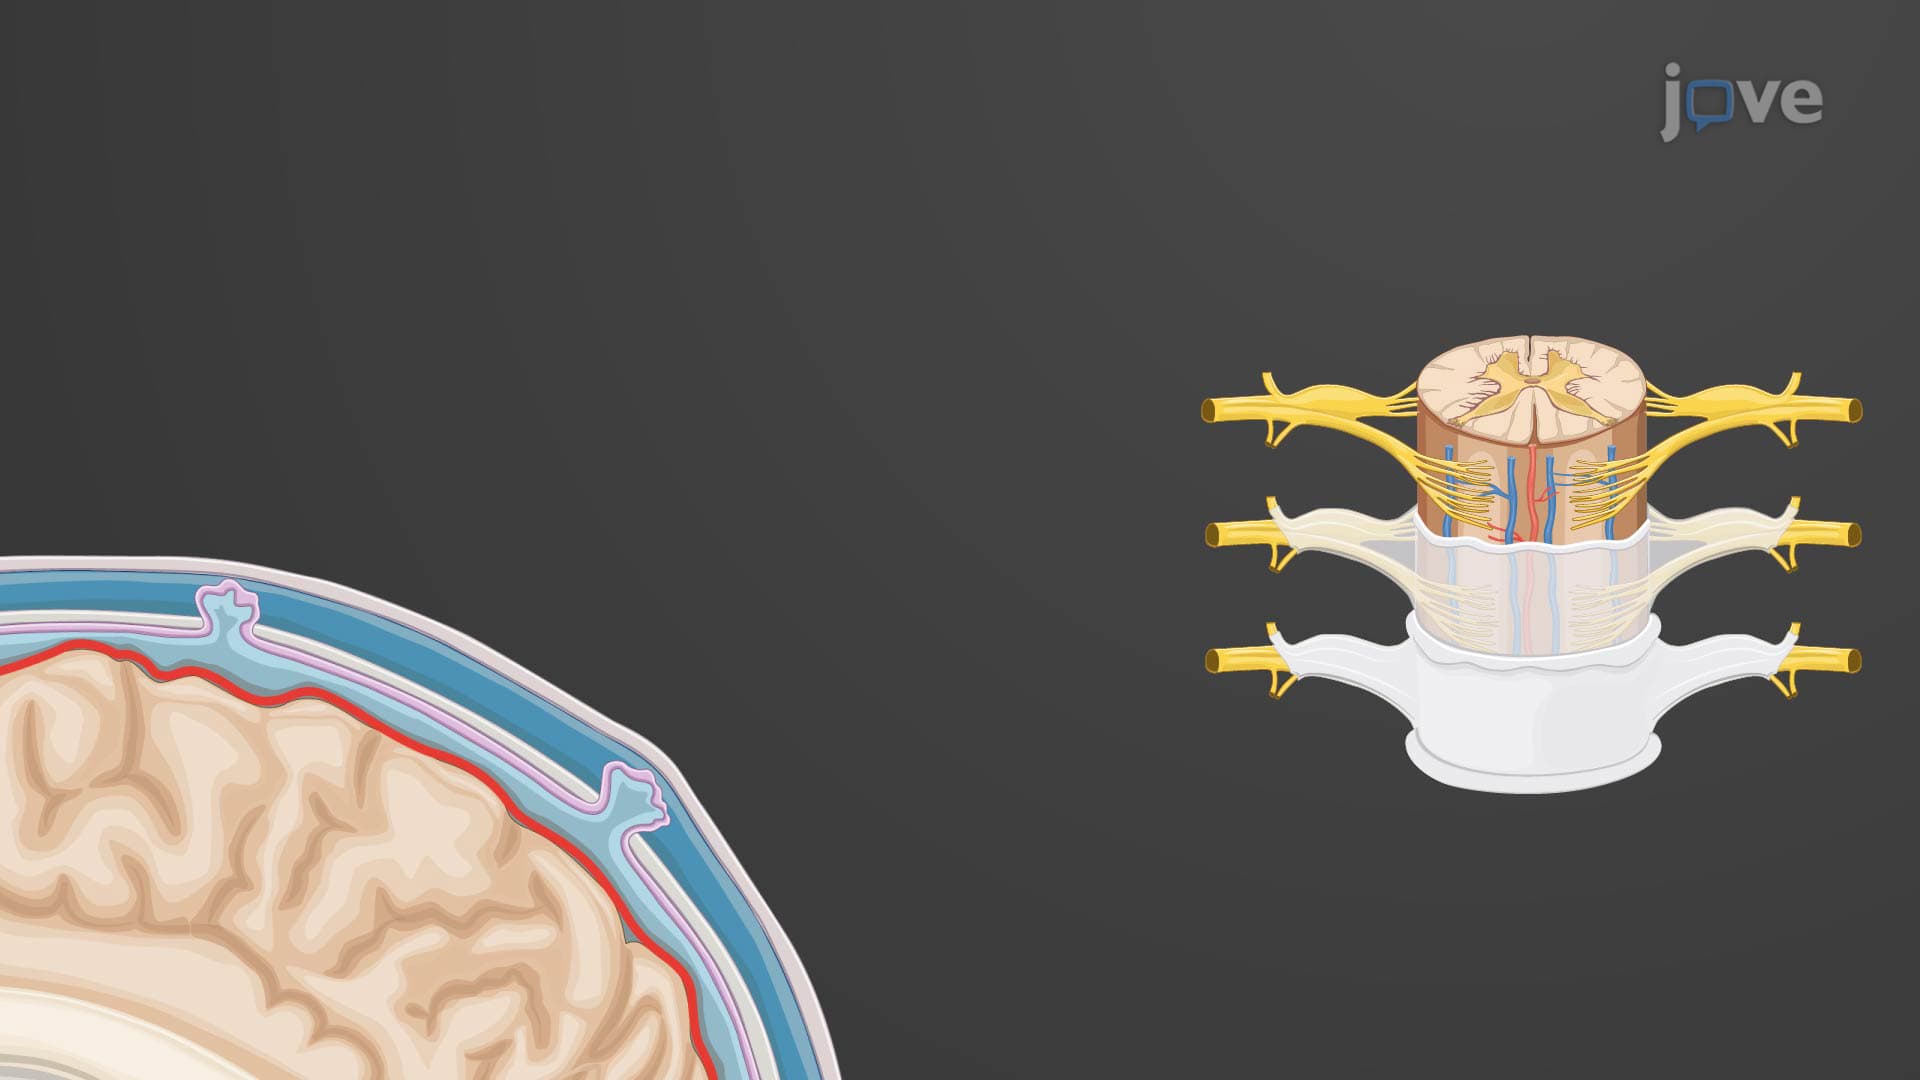
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:26
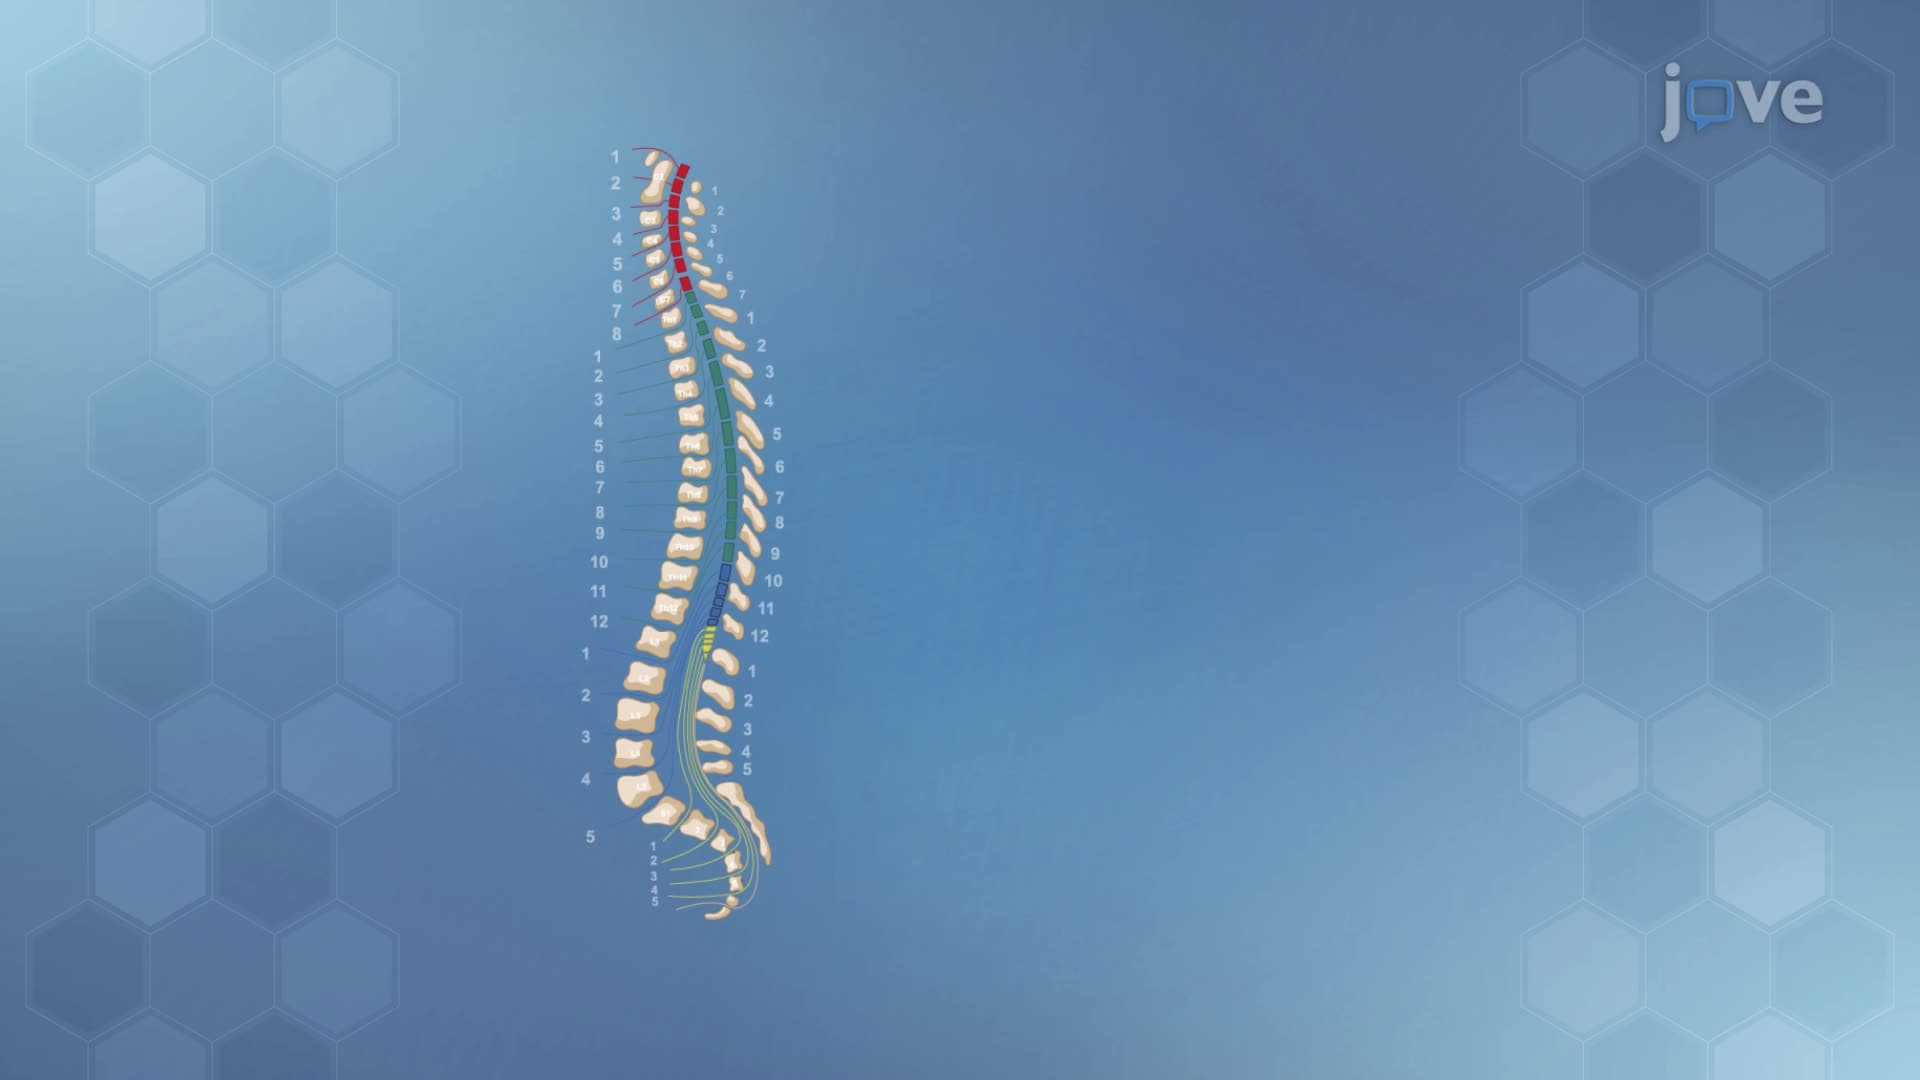
Spinal Cord
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies