Related Experiment Video
Updated: Jan 11, 2026


A Clinical Trial Assessing the Safety, Efficacy, and Delivery of Olive-Oil-Based Three-Chamber Bags for Parenteral Nutrition
Published on: September 20, 2019
Healthcare Resource Utilization and Cost Implications of Commercial Blenderized versus Plant-Based Standard Enteral
Katherine Bennett1, Amarsinh Desai2, Aimee Henrikson2
1Clinical Nutrition and Lactation, Rady Children's Health, Orange, CA, USA.

Purpose:
The study investigated the potential association between commercial blenderized tube feeding formulas (CBTF) or plant-based standard tube feeding formulas (STD-TF), and healthcare resource utilization (HCRU) and costs, in children and adults receiving enteral nutrition (EN) in a post-acute care setting.
Patients And Methods:
United States insurance claims were retrospectively analyzed to evaluate HCRU and costs for visits to emergency department (ED), inpatient, outpatient, urgent care, and other services at 12 weeks post hospital discharge. Between-cohort comparisons were performed for proportions of patients with claims for each place of service, mean number of visits, and unadjusted and adjusted costs.
Results:
Significantly fewer children receiving CBTF vs plant-based STD-TF required inpatient services (16% vs 35%), urgent care (3% vs 10%), ED (15% vs 28%), and other facilities (10% vs 22%) (p < 0.001 for each comparison), with a lower mean number of visits to any healthcare service reported (28 vs 96; p < 0.001). In adults, significantly fewer patients in the CBTF cohort vs the plant-based STD-TF cohort required inpatient (23% vs 38%; p = 0.003) and other services (13% vs 27%; p < 0.001), with a corresponding lower mean number of visits to any healthcare service (24 vs 79; p < 0.001). Total unadjusted costs were significantly lower in both children and adults receiving CBTF compared with plant-based STD-TF (children: $140,962 vs $1,060,345; adults: $166,591 vs $820,905; each p < 0.001). Cost savings associated with CBTF were maintained when costs were adjusted for age, sex, and Charlson's comorbidity index. Children and adults receiving CBTF had significantly lower total adjusted costs compared with those receiving plant-based STD-TF (children: $222,735 vs $965,451; adults: $258,460 vs $919,060 each p ≤ 0.001).
Conclusion:
The use of CBTF was associated with lower HCRU and costs both in children and adults receiving EN in post-acute care settings. To our knowledge, this is the first large real-world study comparing these formulas in post-acute care across both populations. Although the retrospective design and lack of adjustment for all potential confounders preclude conclusions about causation, these findings may guide formula selection based on potential economic impact.


Related Concept Videos
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:27
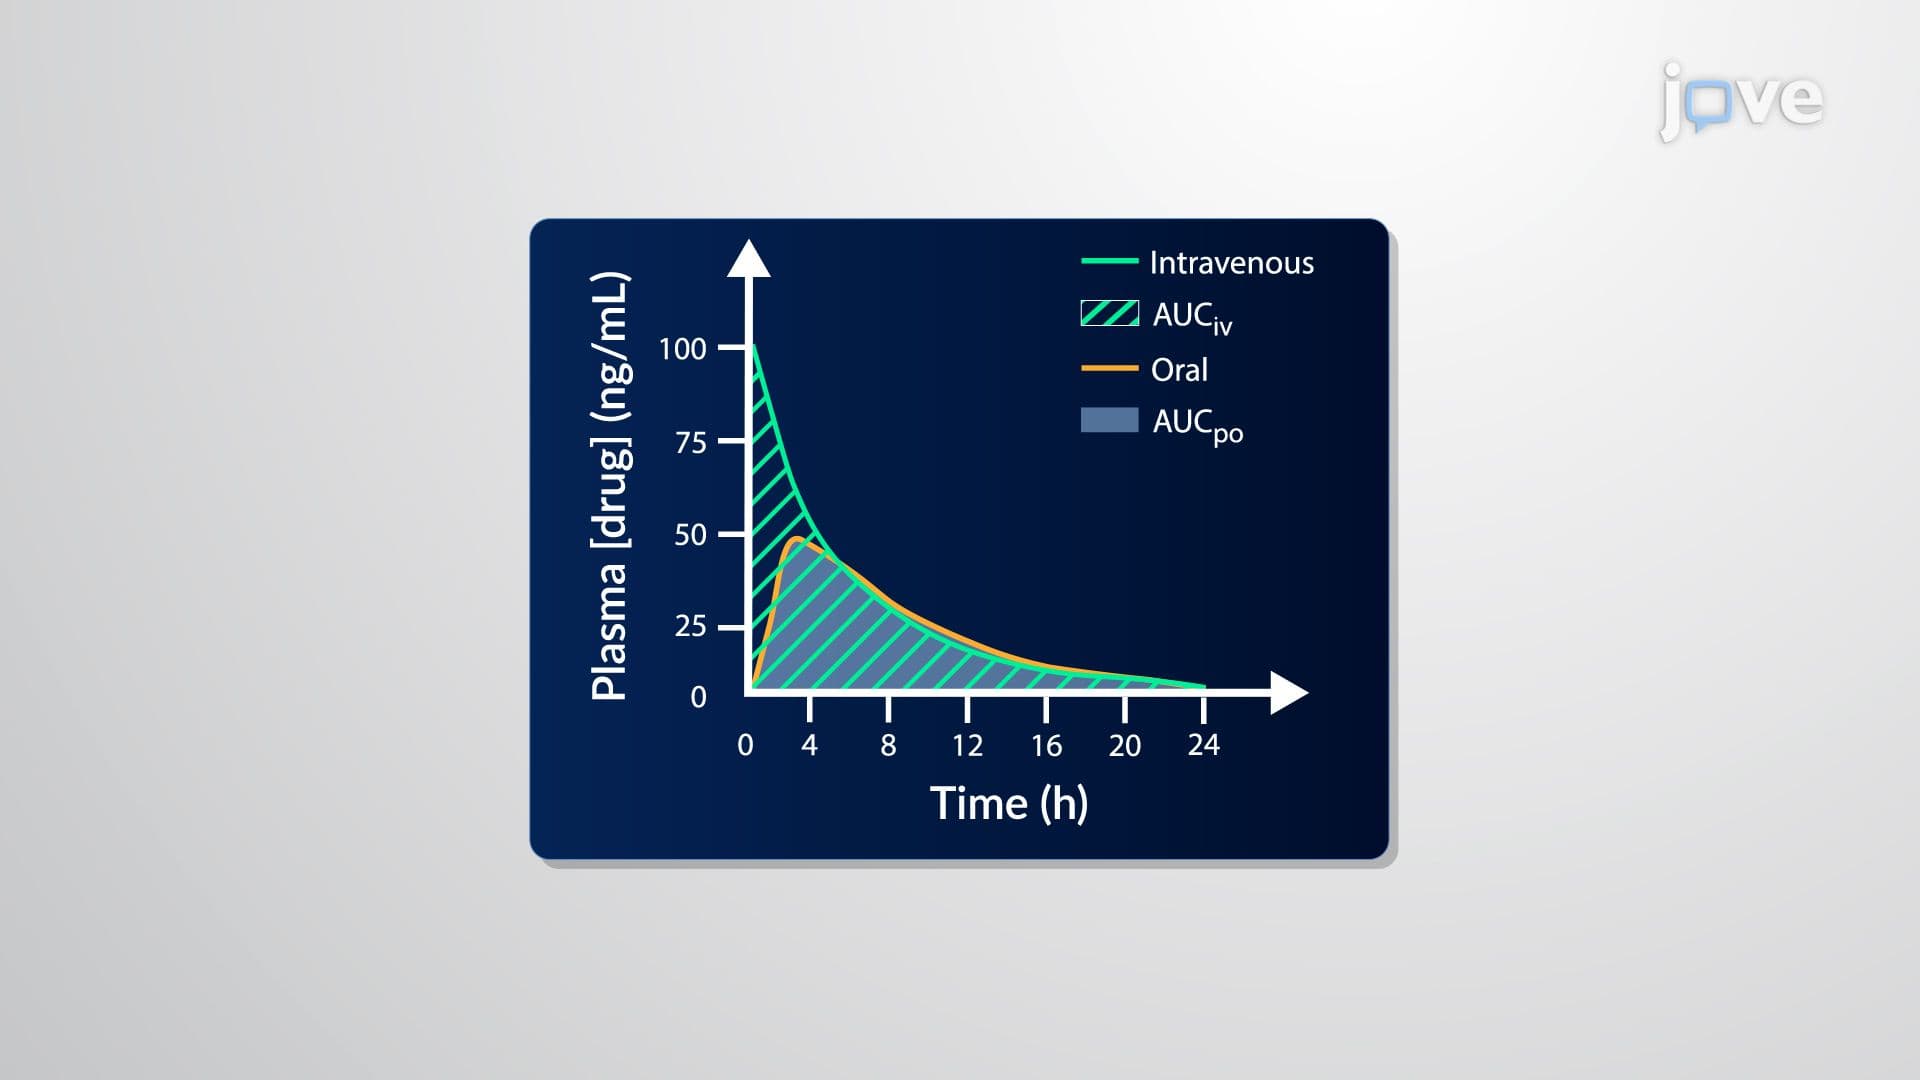
Bioavailability Study Design: Absolute Versus Relative Bioavailability
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...