Related Experiment Video
Updated: Jan 10, 2026
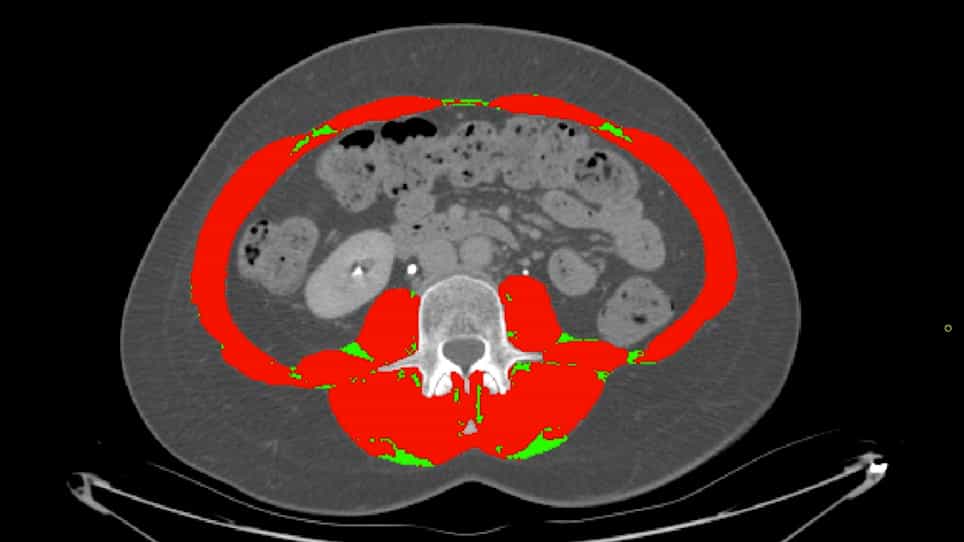

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Modified geriatric nutritional risk index: a high-sensitivity marker with L-shaped association for sarcopenia in
Hua Wei1, Qin Huang1, Ming Liu1
1The Integrated Medical and Elderly Care Center, Chengdu Integrated TCM and Western Medicine Hospital, Chengdu, Sichuan, China.

Background:
Screening for sarcopenia in older inpatients is currently inadequate, primarily because of the lack of consideration of the interaction between inflammation and nutrition. This study aimed to assess the efficacy of a novel modified Geriatric Nutritional Risk Index (mGNRI), which incorporates C-reactive protein (CRP) levels and weight changes, in predicting sarcopenia compared to traditional indices (geriatric nutritional risk index, GNRI/nutritional risk index, NRI).
Methods:
In this cross-sectional study, we evaluated 153 hospitalized older patients (mean age, 80.2 ± 9.1 years) using comprehensive assessments. Sarcopenia was diagnosed based on the Asian Working Group for Sarcopenia (AWGS) criteria, which include muscle mass and strength/function. We analyzed the associations using restricted cubic splines and multivariable logistic regression and compared the diagnostic performance using receiver operating characteristic (ROC) analysis.
Results:
The prevalence of sarcopenia was 24.2% (37/153). The mGNRI was significantly lower in the sarcopenia group compared to the non-sarcopenia group (48.1 ± 11.3 vs. 56.8 ± 12.8, *p* < 0.001). The mGNRI demonstrated an L-shaped relationship with an inflection point at 55.48 (p for nonlinear = 0.012). Below this threshold, each unit increase in mGNRI was associated with a 16.8% reduction in the odds of sarcopenia (OR = 0.832, 95% confidence interval CI: 0.741-0.934), whereas above this point, no significant association was observed (p = 0.504). In contrast, the GNRI or NRI ratio showed a linear protective effect (per unit increase, OR = 0.91, p < 0.001). An mGNRI < 55 indicated an 8.4-fold increased risk (OR = 8.40, 95% CI: 2.69-26.20), whereas GNRI<98 or NRI < 99 indicated a 6.93-fold risk (95% CI: 2.57-18.69). Diagnostic Power: The mGNRI at a cut-off of 55 yielded a sensitivity of 80.4% and the area under the curve (AUC) of 0.752. For a GNRI<98, the balanced accuracy was characterized by a sensitivity of 75.6% and specificity of 63.8%.
Conclusion:
The mGNRI serves as a practical and inflammation-sensitive tool for screening for sarcopenia in older inpatients. Its L-shaped association highlights a critical intervention threshold (mGNRI<55), demonstrating superior sensitivity compared to the linear indices (GNRI, NRI). Incorporating this tool into geriatric assessments may facilitate targeted interventions to address nutritional and inflammatory needs.

Related Concept Videos
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:15
Drug Dosing: Geriatric Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:22
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Absorption