Related Experiment Video
Updated: Jan 10, 2026


Trans-Tympanic Drug Delivery for the Treatment of Ototoxicity
Published on: March 16, 2018
Mannitol for prevention of cisplatin-induced nephrotoxicity: a systematic review and meta-analysis of randomized
Chih-Chin Kao1,2,3, Hsiu-Yu Tai4, Yueh-Chu Sio2,3
1Division of Nephrology, Department of Internal Medicine, School of Medicine, College of Medicine, Taipei Medical University, Taipei, Taiwan.

Background:
Cisplatin causes nephrotoxicity in approximately 30% of patients. Mannitol has been proposed as a nephroprotective agent, yet the clinical evidence remains inconclusive.
Methods:
We systematically searched PubMed, EMBASE, and the Cochrane Library through December 2024 for randomized controlled trials (RCTs) evaluating mannitol versus control interventions for prevention of cisplatin-induced nephrotoxicity. The primary outcome was acute kidney injury (AKI), standardized across CTCAE, AKIN, and RIFLE systems. Given heterogeneous comparators, analyses were stratified by control type without cross-comparator pooling. Odds ratios (ORs) were used for AKI; risk differences (RDs) were used for adverse events. Pooled estimates were generated only when ≥ 5 trials were available per stratum.
Results:
Nine RCTs (357 participants) were included. For severe AKI (grade ≥ 2), three small trials (n = 164) were available. Two placebo-controlled studies showed lower AKI risk with mannitol (absolute reductions ~ 15-20%), while one furosemide-controlled study showed no clear difference. These preliminary observations require confirmation in larger trials. For overall AKI (grade ≥ 1; six trials, n = 297), results were inconsistent across studies. Renal function outcomes were heterogeneous: one placebo-controlled trial favored mannitol, one hydration-controlled trial favored control, and a furosemide-controlled trial showed minimal difference. Adverse events were sparsely reported: no consistent differences were seen for electrolyte or hematological toxicities, while several studies suggested modest reductions in nausea/vomiting and a possible increase in diarrhea.
Conclusions:
Based on only three small trials (n = 164), preliminary trends suggest mannitol might reduce severe AKI in cisplatin-treated patients, particularly versus placebo. However, this evidence is insufficient to support clinical implementation. The observed protective trend should be considered hypothesis-generating rather than definitive. Effects on overall AKI, renal function, and toxicities remain inconclusive. Larger, well-designed RCTs with adequate statistical power are urgently needed before mannitol can be recommended for routine nephroprotection in clinical practice.


Related Concept Videos
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 01:28
Chemotherapy-Induced Nausea and Vomiting: Neurokinin-1 Receptor Antagonists
 01:15
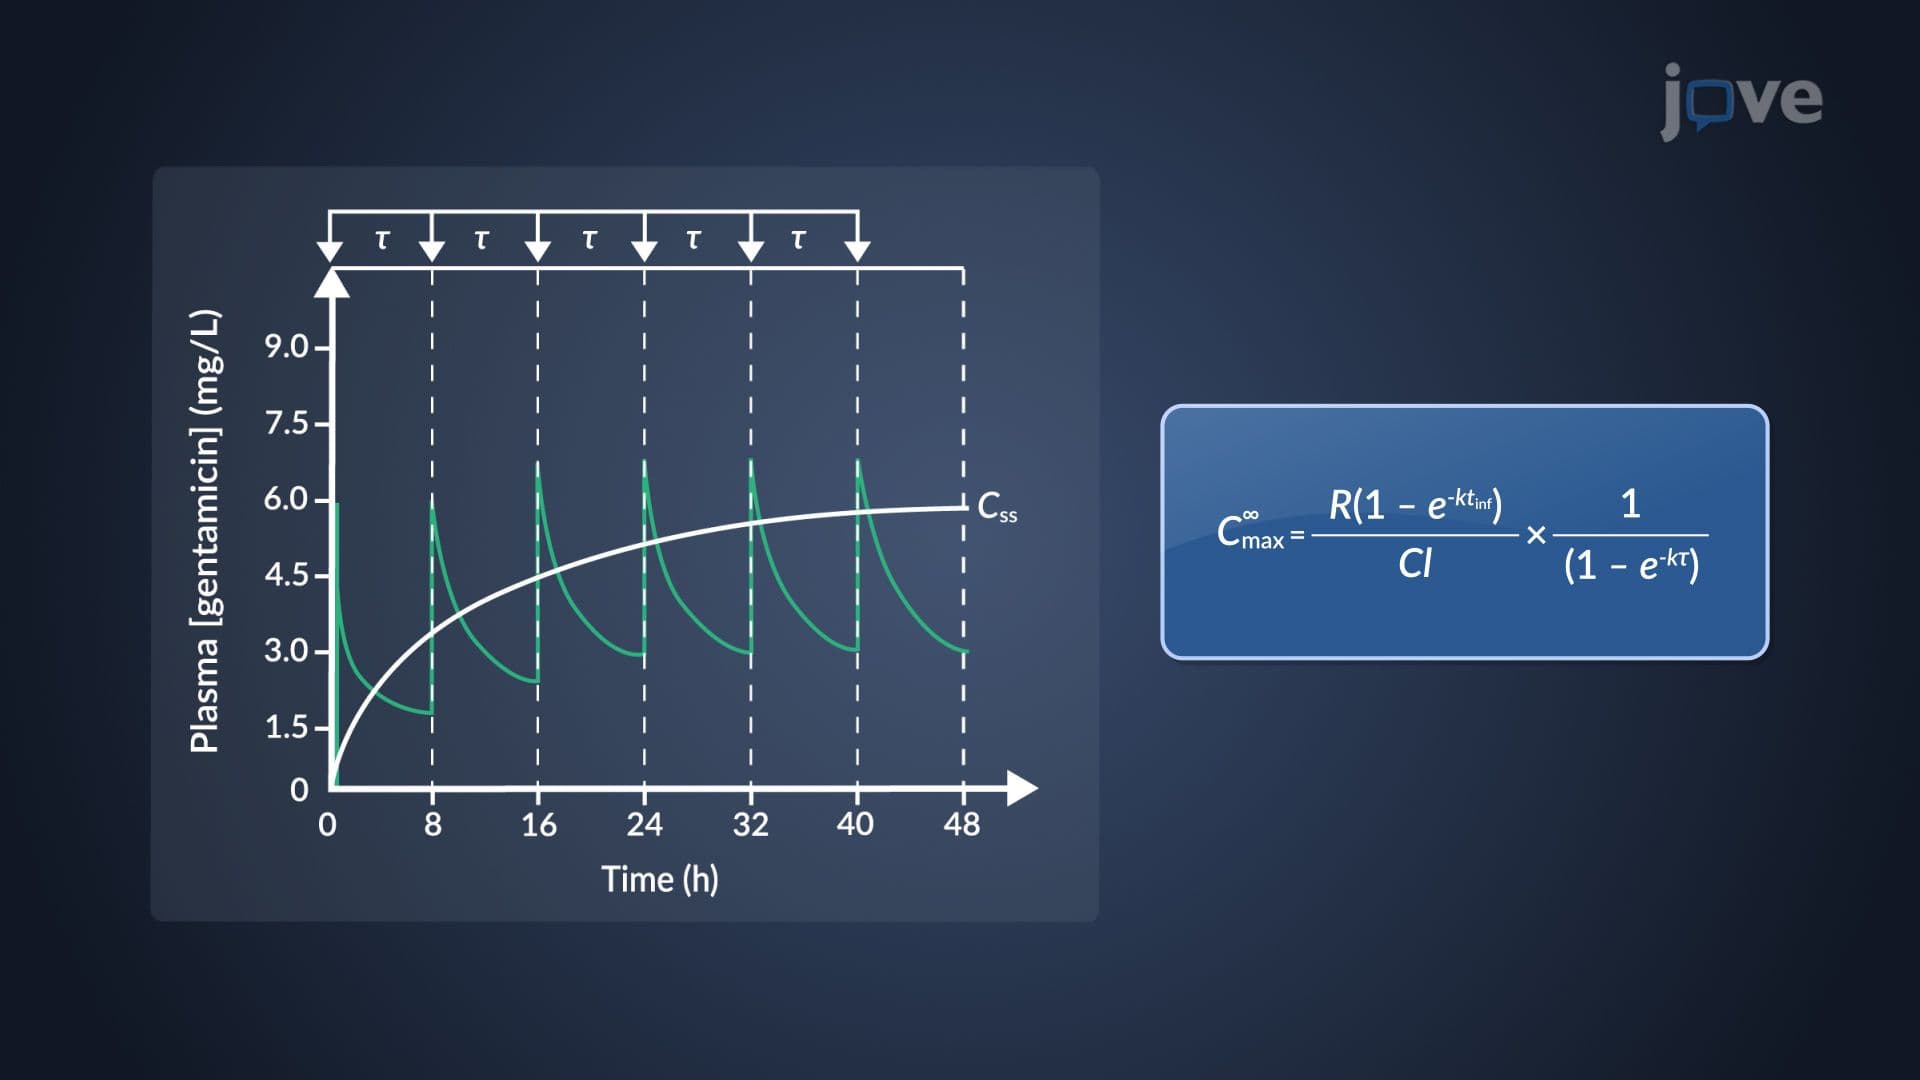
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
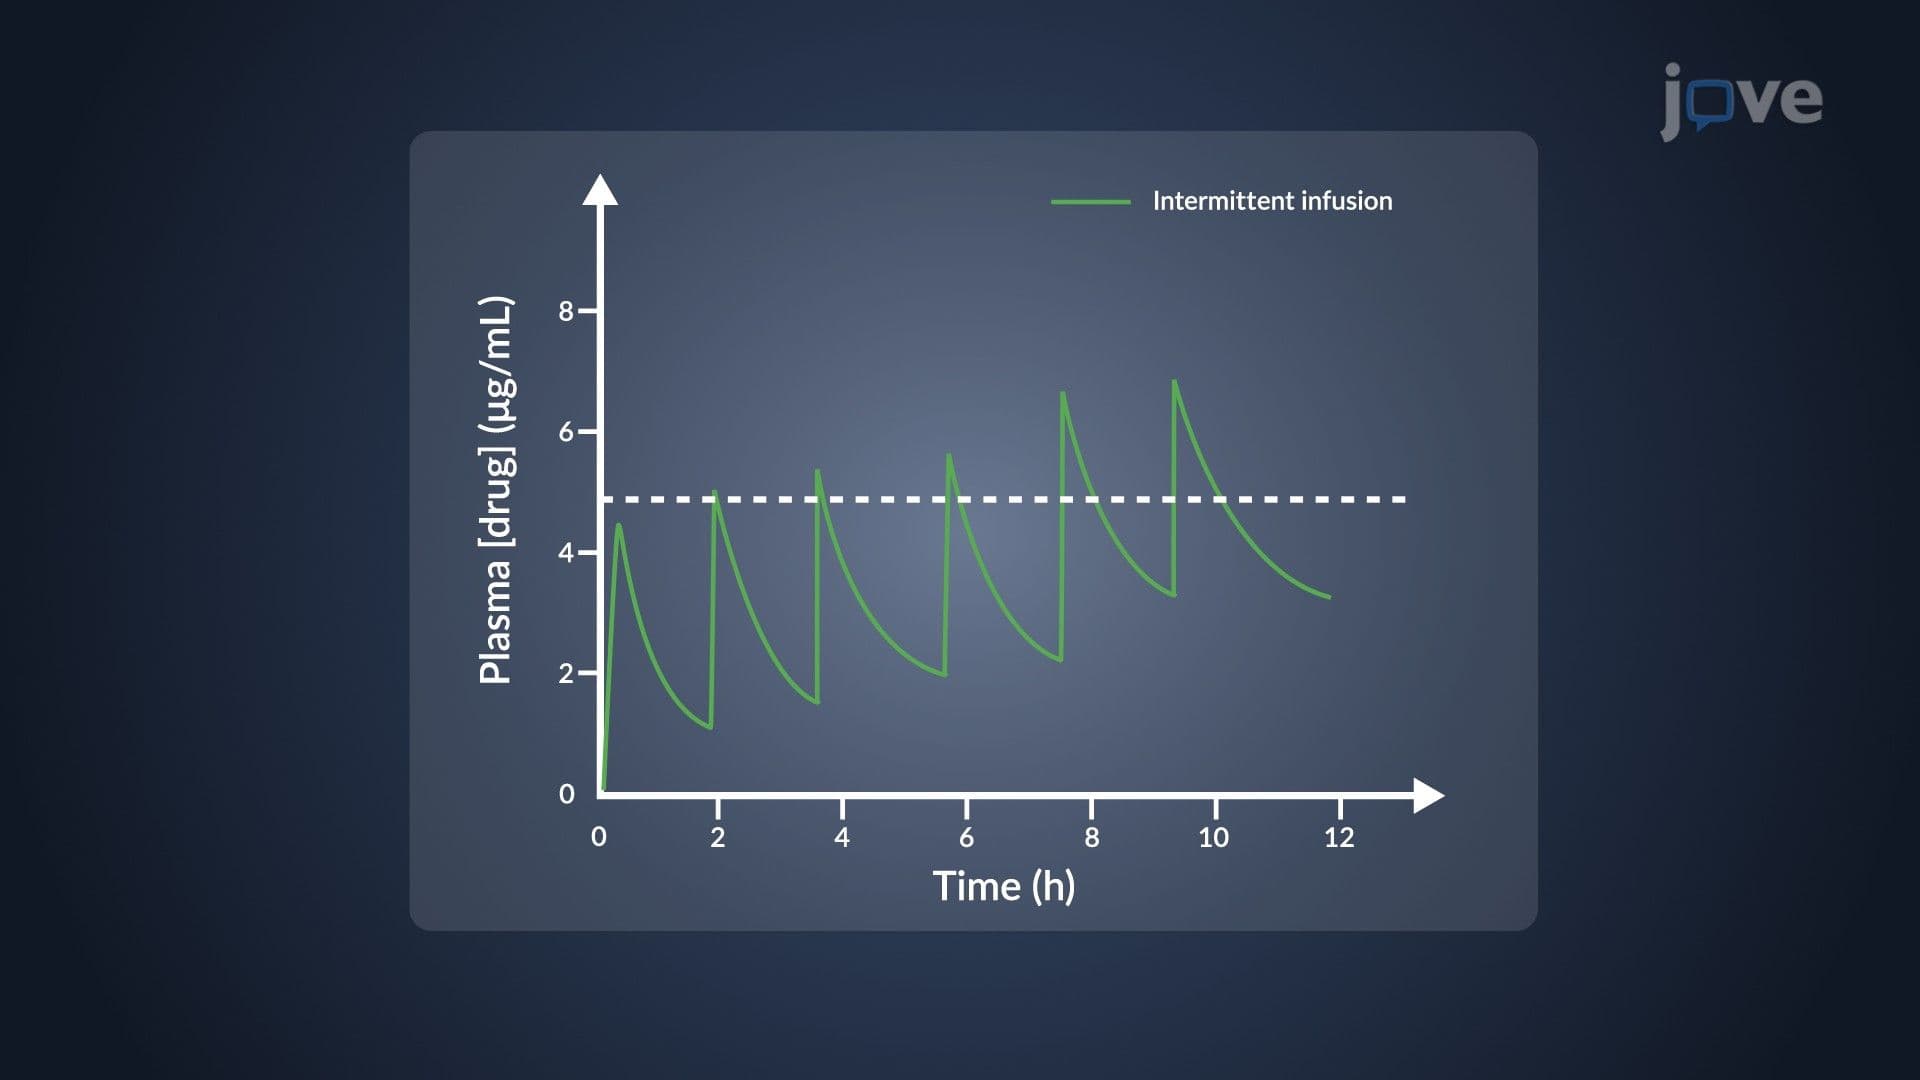
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention