Related Experiment Video For Alkaline phosphatase
Updated: Jan 6, 2026
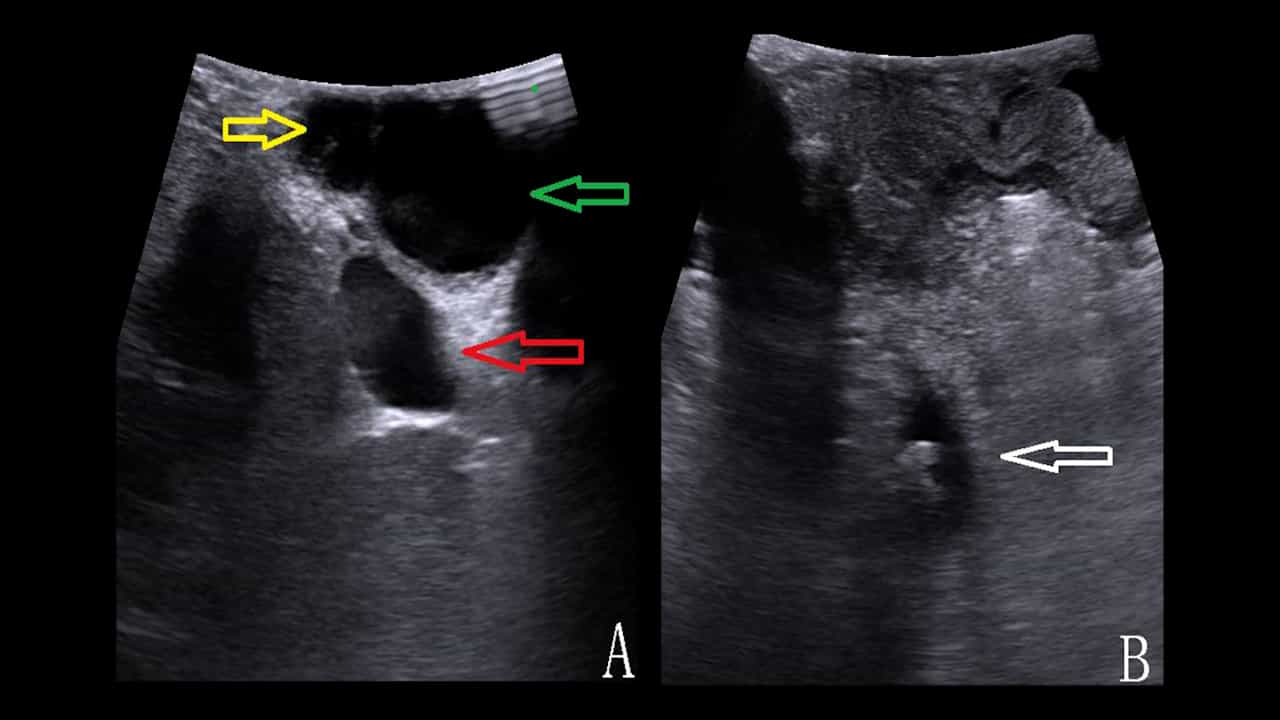

Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Optimizing Care in Primary Biliary Cholangitis: Current Treatments and the Second-Line Decision
Gina Choi1,2, Arun B Jesudian3, Sammy Saab4,5
1Departments of Medicine and Surgery, David Geffen School of Medicine at UCLA, Los Angeles, CA, USA.

Abstract:
Primary biliary cholangitis (PBC) is a chronic, autoimmune, cholestatic liver disease characterized by small bile duct injury that can lead to advanced liver disease including cirrhosis and liver failure. Early diagnosis of PBC is crucial to mitigate the onset of advanced liver disease. However, even after diagnosis, some patients with PBC remain untreated or continue to progress to advanced disease despite initiation of treatment. Further, extrahepatic symptoms such as pruritus and fatigue substantially affect quality of life yet may not be addressed with standard treatment. Ursodeoxycholic acid (UDCA) stands as the first-line treatment for PBC and has been shown to increase survival and reduce the need for liver transplantation. Nonetheless, some patients have an inadequate response or are intolerant to UDCA. Furthermore, UDCA does not address pruritus or fatigue. Approved second-line therapies for PBC include elafibranor and seladelpar. Elafibranor and seladelpar were recently granted Food and Drug Administration (FDA) approval in the accelerated pathway after reducing alkaline phosphatase (ALP) levels and showing promise in improving patient-reported symptoms such as pruritus and fatigue, though they are not without adverse events. With the availability of these new, second-line therapies, current treatment guidelines should be updated to emphasize early evaluation of treatment response to UDCA and to incorporate patient-reported outcomes that impact symptom burden and quality of life. With the current emphasis on patient engagement and personalized medicine, clinicians should consider evaluating symptom burden at diagnosis and improving quality of life to be as important as ALP levels in terms of successful PBC treatment.


Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:29
Inflammatory Bowel Disease IV: Pharmacological Management
Pharmacologic...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...