Related Experiment Video
Updated: Jan 10, 2026

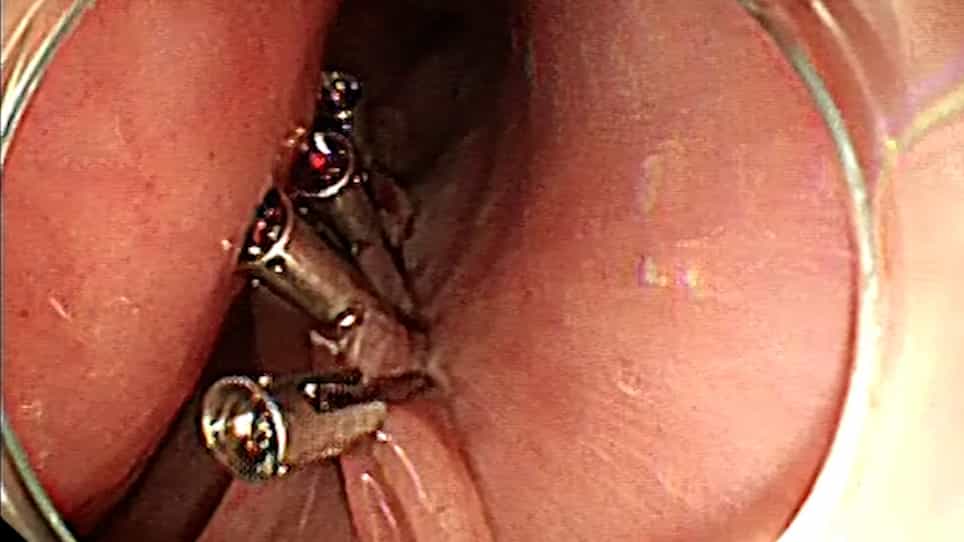
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Early Presentation of Achalasia to the Otorhinolaryngology Department
Trinyanasuntari Munusamy1, How Kit Thong2,3, Primuharsa Putra Sabir Husin Athar3
1Otolaryngology - Head and Neck Surgery, Graduate School of Medicine, KPJ Healthcare University, Nilai, MYS.

Abstract:
Achalasia is a rare esophageal motility disorder characterized by impaired peristalsis and incomplete relaxation of the lower esophageal sphincter (LES), leading to progressive dysphagia, regurgitation, retrosternal pain, and weight loss. Although the disease is usually detected in adults, pediatric presentations are uncommon and often overlooked, resulting in delayed diagnosis and management. The underlying pathophysiology involves degeneration of inhibitory neurons in the myenteric plexus, causing an imbalance between excitatory and inhibitory neurotransmission, which leads to esophageal outflow obstruction. We describe the case of a 13-year-old female who presented with a two-year history of progressive dysphagia to both solids and liquids, frequent regurgitation, and meal-associated retrosternal pain. She reported significant weight loss of 2 kg over two months despite preserved appetite. A barium swallow demonstrated the characteristic "rat-tail" sign at the gastroesophageal junction, while upper gastrointestinal endoscopy and computed tomography confirmed esophageal dilatation and tapering at the LES. With an Eckardt score of 10, indicating moderate-to-severe disease, the patient was referred for surgical management. She subsequently underwent laparoscopic Heller's cardiomyotomy with Dor's fundoplication. Postoperatively, she demonstrated marked symptomatic improvement, weight recovery, and rapid return to normal daily activities. This case highlights the importance of considering achalasia in the differential diagnosis of persistent pediatric dysphagia, which may initially present to specialties such as otorhinolaryngology. Early recognition through imaging and high-resolution manometry is critical to avoid complications such as aspiration, malnutrition, or airway obstruction. Multidisciplinary evaluation and timely surgical intervention remain the cornerstone of treatment, offering excellent long-term outcomes in both pediatric and adult populations.

Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...