Related Experiment Video
Updated: Jan 10, 2026
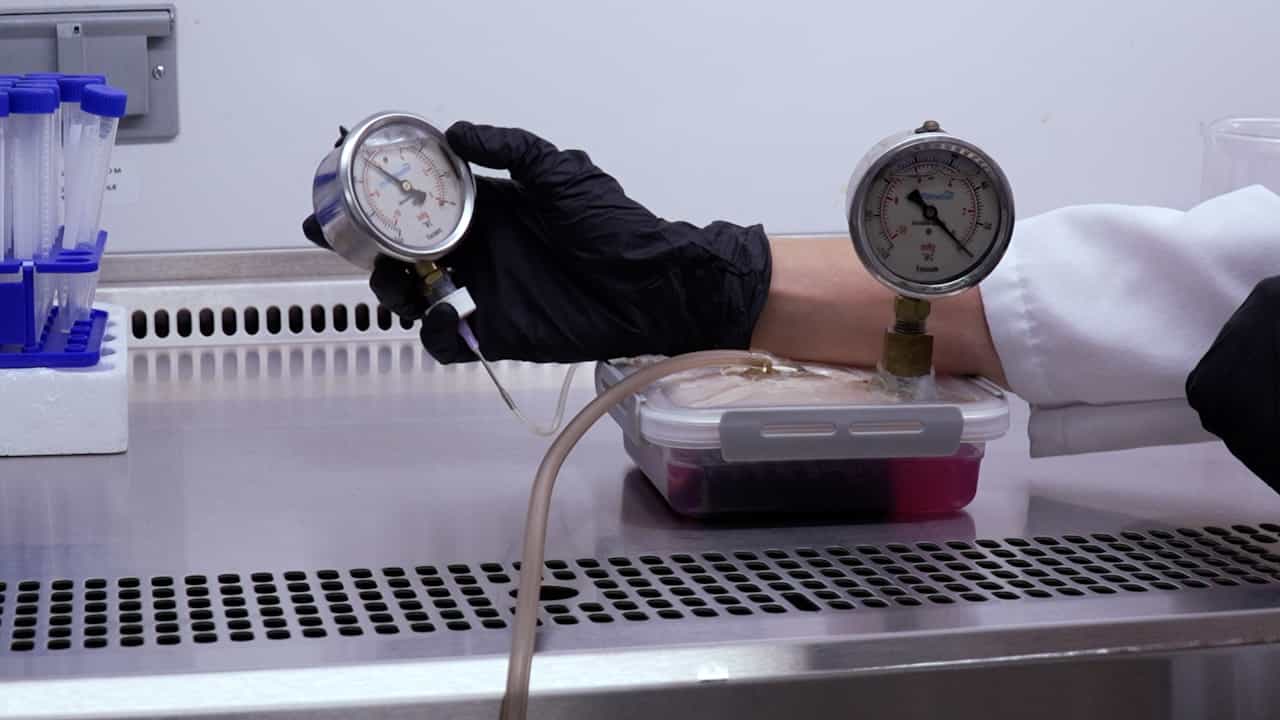

Development of a Benchtop Model for Evaluating the Compatibility of Wound Dressing Materials with Negative Pressure Wound Therapy Systems
Published on: May 2, 2025
Negative pressure wound therapy for combat-related extremity vascular injuries: clinical experience from the war in
Iurii I Sivash1,2, Boris M Koval3,4
1National Military Medical Clinical Center "Main Military Clinical Hospital", Kyiv, Ukraine. y.sivash@gmail.com.

Background:
Extremity vascular injuries are among the most challenging problems in military surgery. They are frequently accompanied by extensive soft tissue loss and heavy contamination, which increases the risk of infection and limb loss. Although negative pressure wound therapy (NPWT) is widely used in civilian practice, its role in combat vascular injuries remains unclear. The war in Ukraine provided an opportunity to evaluate NPWT as part of staged surgical care under modern battlefield conditions.
Methods:
We retrospectively reviewed 85 service members with severe combat-related extremity vascular injuries admitted to a Role IV facility in 2022. Among these patients, 69/85 (81.2%) had extensive soft-tissue defects overlying vascular reconstructions and received NPWT; this subgroup constituted the analytic cohort. A standardised two-layer NPWT technique was used: an inner nonadherent barrier/PVA sponge directly over the reconstruction site and an outer polyurethane foam connected to continuous -70 to -80 mmHg. The dressing was changed every 3-4 days. The outcomes included infectious complications, erosion-related bleeding, arterial thrombosis, secondary amputation, the method of definitive wound closure, and the length of stay.
Results:
The mechanisms of injury were mine blast (71%), gunshot (23%), and other explosive trauma (6%). Combined arterial-venous injuries occurred in 40% (n = 28/69), fractures in 42% (n = 29/69), and primary wound contamination in 57% (n = 39/69) of the patients. Definitive closure was achieved by primary approximation in 75.4% (n = 52/69), skin grafting in 17.4% (n = 12/69), and flap techniques in 4.3% (n = 3/69). Complications occurred in 27.5% (n = 19/69): erosion-related bleeding (13%, n = 9/69), arterial thrombosis (8.7%, n = 6/69), and infection (5.8%, n = 4/69). Erosion-related bleeding clustered in two risk windows: days 7-10 and 18-30. Secondary amputation was required in 2.9% (n = 2/69); in-hospital mortality was 0%.
Conclusions:
A two-layer NPWT protocol at -70 to -80 mmHg was a safe and effective adjunct in the staged management of combat-related extremity vascular injuries with extensive soft-tissue defects. This approach is associated with the preservation of vascular reconstructions and limbs, low infection and amputation rates, the mitigation of erosion-related bleeding, and timely wound closure. Prospective multicenter studies are needed to optimise and standardise NPWT protocols in this setting.
Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:27
Peripheral Artery Disease III: Interprofessional Care