Related Experiment Video
Updated: Jun 16, 2026
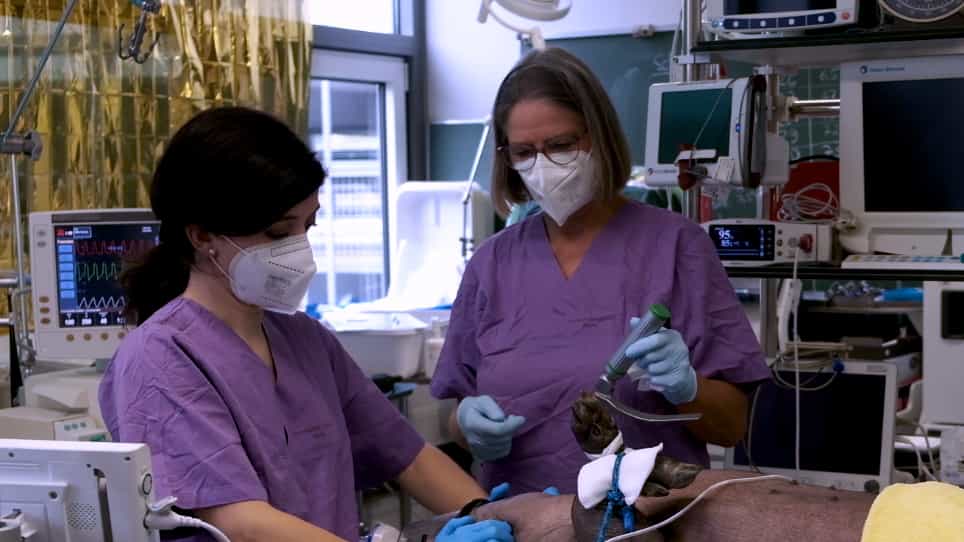

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
All India Difficult Airway Association 2025 guidelines for the management of unanticipated difficult airway in
Jeson R Doctor1, Amit P Shah2, Pankaj Kundra3
1Professor, Department of Anaesthesiology, Critical Care and Pain, Tata Memorial Hospital, Homi Bhabha National Institute, Mumbai, Maharashtra, India.

Insights
When a child experiences an unanticipated difficult airway, prioritize oxygenation and seek experienced help. Guidelines offer a circular algorithm for managing pediatric airway emergencies, including rescue devices and surgical options.
Area of Science:
- Anesthesiology
- Pediatric Emergency Medicine
- Airway Management
Background:
- Pediatric airways present unique anatomical and physiological differences compared to adult airways.
- Unanticipated difficult airways in children pose significant management challenges.
Purpose of the Study:
- To provide evidence-based guidelines for managing unanticipated difficult airways in children aged 1-12 years.
- To establish a structured approach prioritizing oxygenation and timely intervention.
Main Methods:
- Development of a circular algorithm for managing pediatric airway emergencies.
- Recommendations for device selection, including 2nd generation supraglottic airways (SGA) and face masks (FM).
- Emphasis on 'Call for help' (Code D) and continuous oxygenation.
Main Results:
- The algorithm allows for device interchangeability and prioritizes maintaining peripheral oxygen saturation (SpO2) above 95%.
- Defines clear steps for escalation, including re-intubation attempts, use of rescue devices, or proceeding to emergency surgical airway.
- Outlines post-resuscitation care and parent education with an 'Airway Alert Card'.
Conclusions:
- The guidelines offer a systematic, flexible approach to pediatric airway emergencies.
- Prioritizing oxygenation and structured escalation improves patient outcomes.
- Effective management involves prompt decision-making regarding airway devices and surgical intervention when necessary.
Abstract:
The paediatric airway differs from the adult airway both anatomically and physiologically. These guidelines are recommended for use in unanticipated difficult airways in children aged 1-12 years. If the initial intubation attempt fails, the anaesthesia team should "Call for help" (Code D) and prioritise providing oxygen to maintain peripheral oxygen saturation (SpO2) above 95%. While awaiting help, the anaesthesia team may re-attempt tracheal intubation, this time by a more experienced operator, after reoptimising position and considering alternate airway devices. The anaesthesiologist may opt for a 2nd generation supraglottic airway (SGA) device as a rescue device or continue the anaesthetic using a face mask (FM). Maintaining oxygenation throughout the period is essential. The current guidelines introduce a circular design for the algorithm, allowing device interchangeability. If satisfactory oxygenation is achieved with either a 2nd generation SGA device or FM, the decision to continue anaesthesia or wake the child will depend on the urgency of the procedure and the comfort of the anaesthesiologist. If satisfactory ventilation cannot be maintained with a 2nd generation SGA device or FM or following a failed tracheal intubation, declare "complete ventilation failure" and prepare for an emergency surgical airway. The options for emergency surgical airway depend on the availability of trained surgical help and the age of the child. Post-resuscitation care should address the various steps taken to return the child to normalcy and to discharge. This should include giving an "Airway Alert Card" to the parents to avoid similar life-threatening situations in future.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.