Related Experiment Video
Updated: Jan 10, 2026


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Avoiding Unnecessary Urethroplasty by Periurethral Mobilization as a Treatment Option for Small Urethral Strictures:
Lalit Kumar1, Singathala Gnana Sree1, Yashasvi Singh1
1Department of Urology, Institute of Medical Sciences, Banaras Hindu University, Varanasi, IND.

Abstract:
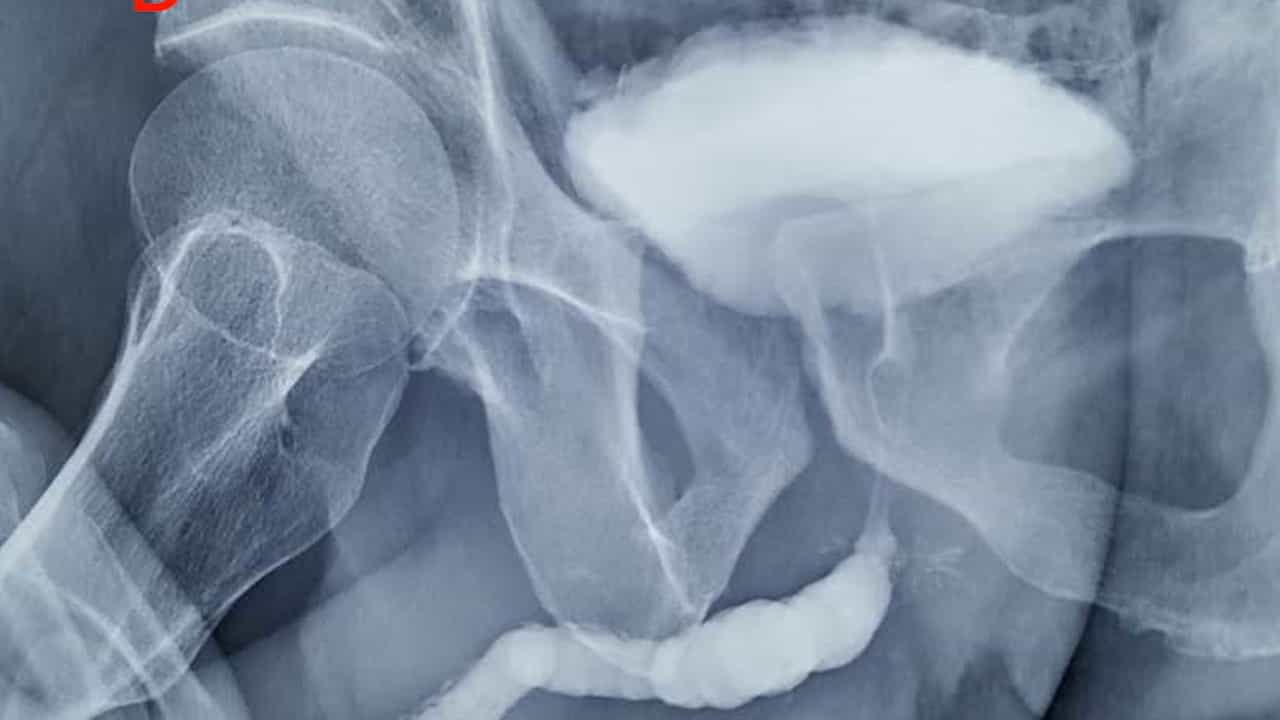
Urethral stricture remains a frequently encountered urological condition, with urethroplasty often regarded as the standard approach for complex or recurrent cases. However, in specific scenarios, intraoperative assessment may reveal less severe pathology, allowing for a more conservative and less invasive management strategy. This case series describes male patients who were scheduled for urethroplasty but were ultimately treated successfully with periurethral mobilization, adhesiolysis, and catheterization alone. Four male patients, aged between 19 and 51 years (mean age 31 years), presented with lower urinary tract symptoms, including weak urinary stream, straining, incomplete emptying, and acute urinary retention. Preoperative imaging with retrograde urethrogram and micturating cystourethrogram suggested bulbar urethral strictures with stricture length ranging from 0.5 to 2cm (mean 1.5 cm), and all patients were planned for urethroplasty. Initial maximum urinary flow rates (Qmax) ranged from 2 to 6 mL/second, with a mean of 3.75 mL/second, while post-void residual (PVR) urine volumes ranged from 200 to 320 mL, with a mean of 237.5 mL. Intraoperatively, after mobilizing the urethra, dense periurethral adhesions were observed without significant intraluminal narrowing. Gentle insertion of a 16 Fr Foley catheter was successful in each case, leading to the decision to avoid urethroplasty. All patients were managed with adhesiolysis and catheter drainage. Postoperative follow-up demonstrated marked improvement in symptoms, with Qmax ranging from 24 to 27 mL/second, with a mean of 25.25 mL/second, and PVR volumes decreasing to 10 to 15 mL, with a mean of 12.75 mL. This series highlights the importance of intraoperative re-evaluation in patients with suspected urethral stricture. Careful mobilization and catheter testing can help identify those who can be effectively managed without urethroplasty, thereby minimizing surgical morbidity. Incorporating and reinforcing this step into operative planning can support more individualized and less invasive treatment strategies.
More Related Videos
 03:55
Urethroplasty with Pedicled Tunica Vaginalis for the Treatment of Long-segment Anterior Urethral Stricture Caused by Lichen Sclerosus of Glans Penis
Published on: October 18, 2024
 03:37
Iatrogenic Injury Recapitulated: Electroexcision Technique for Urethral Stricture Modeling in Rats
Published on: October 11, 2024
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:19
Urodynamic Studies: Uroflowmetry
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination