Related Experiment Video
Updated: Jun 30, 2026
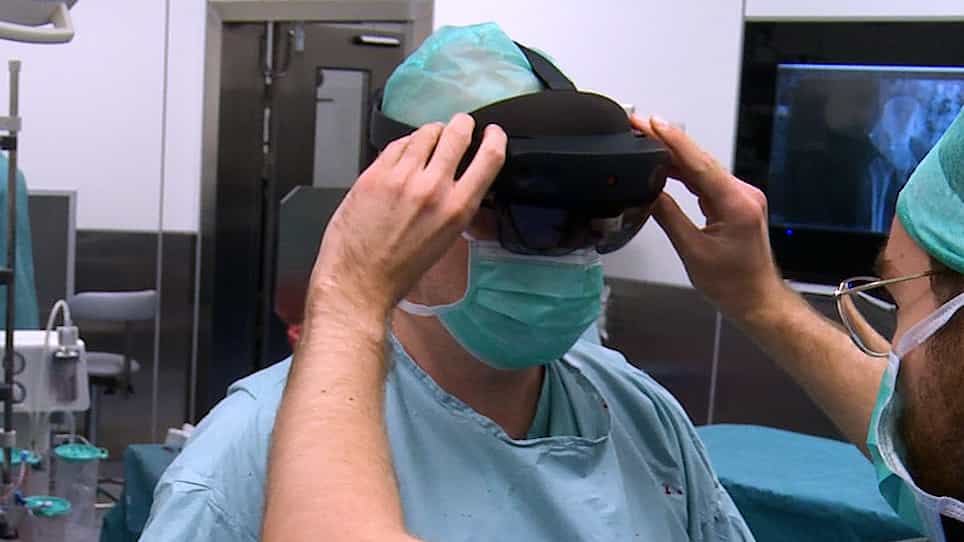
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Pricing matters: A retrospective national study of pricing reform impact on hip fracture procedures in Israel
Gideon Leibner1, Meir Liebergall1, Shuli Brammli-Greenberg2
1The Hebrew University-Hadassah, Faculty of Medicine, Jerusalem, Israel; The Hebrew University-Hadassah, Faculty of Medicine, Hadassah Medical Center, Department of Orthopedics, Jerusalem, Israel.

Background:
This study examines the effects of a 2015 national reform in the Israeli healthcare system in the pricing structure for hip fracture procedures, where hospitals are reimbursed at a fixed rate based on the relevant Procedure-Related Group (PRG). The reform increased reimbursement rates for urgent hip-replacements, shifting the relative financial incentives between procedures.
Objective:
To estimate the impact of the PRG tariff change on procedure mix and patients' likelihood of undergoing hip replacement.
Methods:
Utilizing a longitudinal retrospective case study approach, this national, multicenter, population-based study analyzed data from all 88,585 publicly funded urgent hip surgical procedures carried out in Israel from 2007 to 2018. The empirical strategy included a descriptive analysis of trends, Interrupted Time Series (ITS) and Projection-Based Adaptation of DID (Projected-DID).
Results:
Among 88,585 urgent hip surgeries, 68.2% occurred before and 31.8% after the reform. Internal hip fixation (86.5%) remained most common, but total hip arthroplasty (THA) rose from 10.5% in 2007 to 32.2% in 2018, accompanied by a corresponding decline in hemiarthroplasty (HA). ITS analysis showed accelerated THA adoption post-reform (slope-change OR 1.06/quarter), with immediate declines in HA and IHF. The projected-DID estimates indicated the reform more than doubled the probability of THA, while moderating trends in HA and IHF. Overall, higher reimbursement increased likelihood of joint replacement, shifting from HA to THA.
Conclusions:
Our study joins the extensive literature showing that compensation mechanisms are powerful tools for policymakers and payers to influence clinical decisions and shift practice at both hospital and departmental levels.

