Related Experiment Video
Updated: Jan 9, 2026
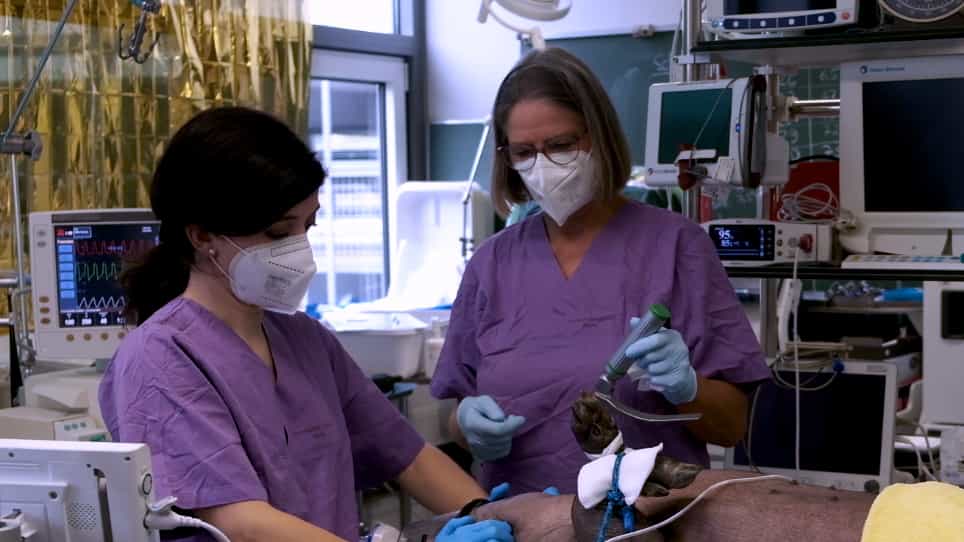
Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Hospital and long-term outcomes for subglottic suction and polyurethane cuff versus standard endotracheal tubes in
Miriam M Treggiari1, Emily S Sharp2, Tetsu Ohnuma3
1Department of Anaesthesiology, Duke University School of Medicine, Duke University, Durham, NC, USA; Department of Neurology, Yale University, New Haven, CT, USA.

Background:
Endotracheal tubes with subglottic ports and a polyurethane cuff are recommended for reducing microaspiration in patients who are ventilated. However, their long-term safety and efficacy after emergency intubation are uncertain.
Methods:
In this randomised controlled phase 2 trial conducted at two single centres (Oregon Health and Science University [OHSU, Portland, OR, USA] and Yale New Haven Hospital [YNHH, New Haven, CT, USA]), all patients aged 18 years or older requiring endotracheal intubation either in the emergency department or elsewhere in hospital for acute respiratory distress or failure were randomly assigned to receive a polyurethane-cuffed endotracheal tube with subglottic suction (PU-EVAC) or a polyvinylchloride-cuffed endotracheal tube (PVC). Individuals who were electively intubated in the operating room and protected populations (children [aged younger than 18 years], pregnant women, and prisoners) were ineligible to participate. Patients were randomised 1:1 into the two treatment arms using a fair coin randomisation scheme. Patients assigned to the PVC group were treated according to usual care, and patients assigned to the PU-EVAC group received continuous subglottic suctioning until removal of the endotracheal tube. The coprimary endpoints at 6 months were laryngeal injury, quality of life (Short Form-36 [SF-36] physical component summary [PCS] and mental component summary [MCS] scores), and cognitive function. Secondary endpoints were infection-related ventilator-associated complications (IVAC) and possible ventilator-associated pneumonia (VAP). This trial is registered at ClinicalTrials.gov (NCT03705286) and is now completed.
Findings:
Between May 6, 2019, and July 31, 2019 (Oregon Health and Science University), and Sept 29, 2020, to Feb 11, 2022 (Yale New Haven Hospital), 1074 adult patients were enrolled and 1068 were randomly assigned to either the PVC (n=533) or the PU-EVAC (n=535) endotracheal tube group. Participants had a mean age at intubation of 62·9 years (SD 15·7), were mostly male (671 [63%] of 1068), and mostly White (718 [67%]). IVAC occurred in 43 (8%) of 535 patients in the PU-EVAC group and in 33 (6%) of 533 patients in the PVC group (risk difference 0·02 [95% CI -0·01 to 0·05]); possible VAP occurred in 30 (6%) patients in the PU-EVAC group and 24 (5%) patients in the PVC group (0·01 [-0·02 to 0·04]). At 6-month follow-up, 558 patients had died (274 [51%] in the PU-EVAC group and 284 [53%] in the PVC group). 157 completed the 6-month follow-up visit. Laryngeal injury was reported in 71 (83%) of 86 patients in the PU-EVAC group and in 49 (70%) of 70 patients in the PVC group (0·11 [-0·03 to 0·20]; p=0·098). Mean PCS was 39·97 (SD 10·97) in the PU-EVAC group and 40·49 (11·92) in the PVC group (mean difference -0·52 [95% CI -4·21 to 3·17]; p=0·78) and mean MCS was 45·91 (13·10) in the PU-EVAC group and 48·89 (12·22) in the PVC group (-2·98 [-7·03 to 1·07]; p=0·15). Cognitive impairment was present in 70 (85%) of 82 in the PU-EVAC group and 54 (81%) of 67 patients in the PVC group (risk difference 0·05 [-0·07 to 0·17]; p=0·44).
Interpretation:
The PU-EVAC did not reduce the incidence of IVAC or possible VAP compared with a standard PVC endotracheal tube with no subglottic drainage. At 6-month follow-up, neither quality of life, cognitive function, nor laryngeal injury differed between groups. However, the small number of survivors who provided information on their physical and mental status limits the conclusions that can be drawn regarding long-term outcome differences.
Funding:
National Institutes of Health and National Heart, Lung, and Blood Institute.


Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
Tracheostomy Suctioning II: Procedure