Related Experiment Video
Updated: Jan 9, 2026
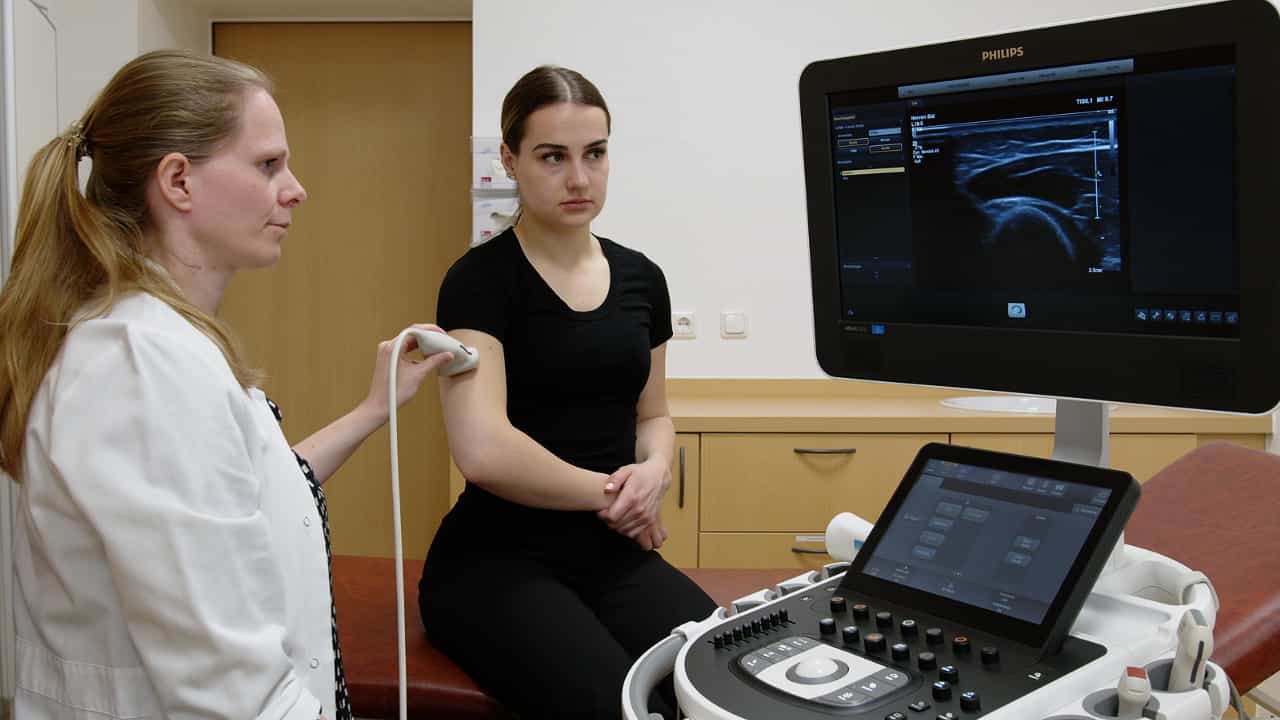

Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Nerve ultrasound, neuronopathy and cough predict sensory neuropathy patients with RFC1 expansions
Anthony Garvey1, I Zay Melville2, Carolin K Scriba3
1Neurology Department, Dunedin Hospital, He hauora, he kuru pounamu, Health New Zealand, Te Whatu Ora, Dunedin 9054, New Zealand.

Abstract:
The finding of biallelic pathogenic pentanucleotide RFC1 expansions has extended the spectrum of disease in cerebellar ataxia, neuropathy and vestibular areflexia syndrome. It is clear that for many, a sensory neuropathy is an early feature and raises the question of how to identify which patients with this common neurophysiological presentation should be tested genetically for the condition. We identified patients with idiopathic, sensory predominant neuropathies who had attended the Neurophysiology Department of Auckland Hospital for nerve conduction studies. We undertook a systematic clinical re-evaluation to test whether any of the following hypothesized variables distinguish the presence of pathogenic RFC1 expansions. These were (i) chronic cough, (ii) ataxia, (iii) pure sensory changes on nerve conduction, (iv) a non-length-dependent pattern of sensory loss on nerve conduction studies, (v) small nerves on peripheral nerve ultrasound, (vi) bilateral vestibular dysfunction and (vii) autonomic dysfunction. We recruited 53 patients, of whom 10 had normal repeat nerve conductions. Among the 43 (25 males, 18 females) remaining patients, five were positive for the pathogenic RFC1 expansions. All five reported a chronic cough (versus 4/38 RFC1-negative cases, P = 0.0002). None of the five cases had abnormal motor findings (versus 20/37 RFC1-negative cases, P = 0.07). Four of the five cases had small (<5.2 mm2) mean upper limb nerves by cross-sectional area on ultrasound (versus 2/38 RFC1-negative cases, P = 0.0006). The fifth had concurrent diabetes, which might explain their normal sized nerves. Four of the five cases had a non-length-dependent sensory neuropathy, and one had a length-dependent sensory neuropathy. The RFC1-positive case with a length-dependent neuropathy had small upper limb nerves on ultrasound. There were no differences in ataxia scores between the groups, and only two RFC1-positive cases had vestibular involvement. Two of the five RFC1-positive cases, both Sāmoan, had a novel arrangement in their RFC1 expansion in which the pathogenic AAGGG expansion was preceded by a short AAAAG expansion. Taken together, in this small sample, the presence of a chronic cough with either a non-length-dependent neuropathy on nerve conduction studies or a mean upper limb nerve cross-sectional area <5.2 mm2 was strongly associated with the RFC1 expansion (sensitivity 100%, specificity 97%). Patients who fit these criteria should be tested genetically for RFC1. Ultrasound and nerve conduction studies should be seen as complementary in the workup of patients for RFC1 expansions.
More Related Videos
 06:40
Screening of Axonal Degeneration in Carpal Tunnel Syndrome Using Ultrasonography and Nerve Conduction Studies
Published on: January 11, 2019
 09:39
Establishing a Mouse Model of a Pure Small Fiber Neuropathy with the Ultrapotent Agonist of Transient Receptor Potential Vanilloid Type 1
Published on: February 13, 2018
