Related Experiment Video
Updated: Jan 9, 2026
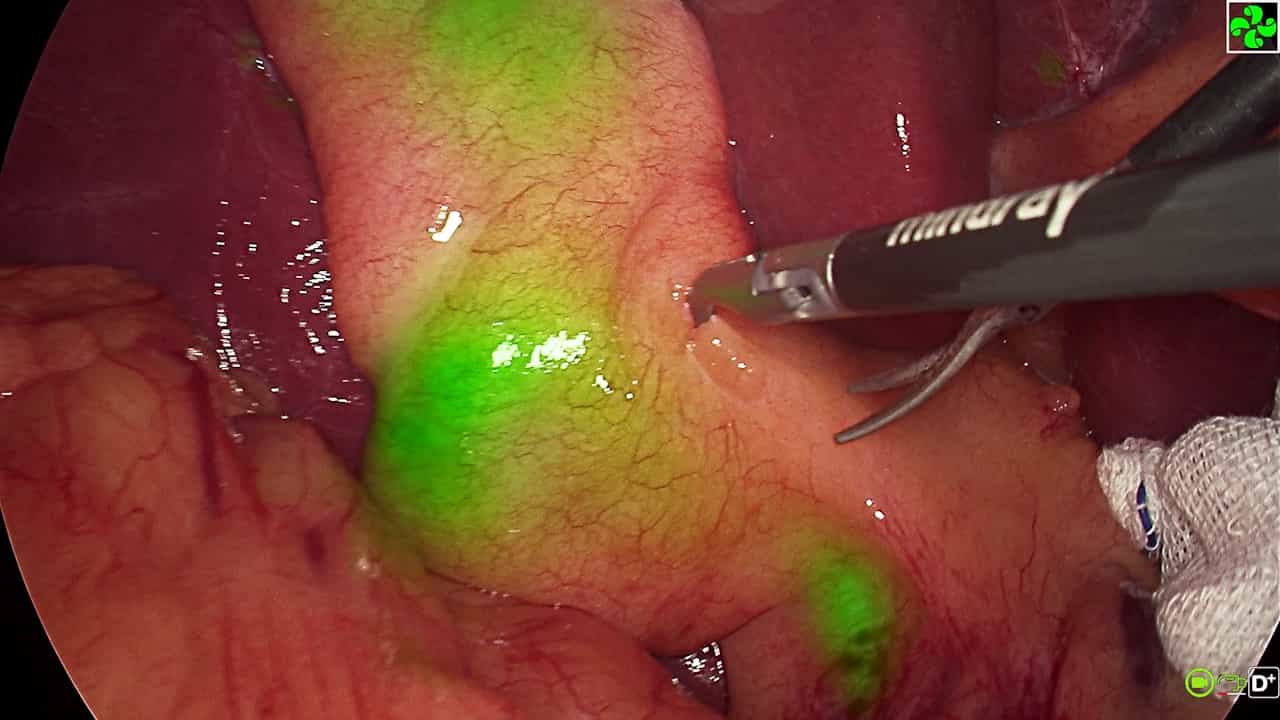

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Type II Gallbladder Perforation: A Management Conundrum or a Surgical Indecision?
Marco Youssef1, Mina Aziz2, Ashraf Rasheed3
1Upper Gastrointestinal Surgery, The Grange University Hospital - Aneurin Bevan University Health Board NHS, Wales, GBR.

Background:
Gallbladder perforation (GBP) is a rare but serious complication of acute cholecystitis. Niemeier Type II, characterized by localized perforation with pericholecystic abscess, represents the most common subtype but lacks standardized management guidelines. This study aimed to evaluate clinical, radiologic, and comorbidity-related factors influencing treatment selection and outcomes in Type II GBP.
Methods:
We retrospectively reviewed all radiologically diagnosed cases of GBP at a single university hospital between 2014 and 2022. Patients were classified according to Niemeier's system, with Type II cases subdivided by management approach: cholecystectomy, percutaneous cholecystostomy, interventional radiology (IR) drainage, or antibiotics alone. Data collected included demographics, Charlson Comorbidity Index (CCI), CT findings, length of stay (LOS), reintervention, readmissions, and mortality. Multivariate analysis identified predictors of management strategy and outcomes.
Results:
Ninety-one patients were identified, of whom Type II perforation accounted for 72 cases. Management strategies included cholecystectomy in 9 (13%) , cholecystostomy in 12 (17%), IR drainage in 17 (24%), and antibiotics alone in 33 (46%). One patient underwent combined IR drainage and cholecystostomy. Patients undergoing surgery had the lowest CCI, while conservative strategies were more common among older patients with a higher comorbidity burden. Gallbladder distension predicted cholecystostomy, while loculated collections were associated with IR drainage. Receiver operating characteristic (ROC) analysis demonstrated that a CCI greater than 5.5 effectively excluded patients from cholecystectomy. No significant differences were observed in mortality, LOS, or reintervention rates between treatment groups.
Conclusion:
Comorbidity burden, age, and CT morphology are key determinants of management in Type II GBP. While surgery remains the definitive treatment, individualized nonoperative strategies can achieve comparable short- and intermediate-term outcomes in high-risk patients. Larger multicenter studies are required to establish evidence-based guidelines.

Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:17
Pericarditis III: Medical Management
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...