Related Experiment Video
Updated: Jan 9, 2026

Determining Soil-transmitted Helminth Infection Status and Physical Fitness of School-aged Children
Published on: August 22, 2012
Strongyloides stercoralis hyperinfection with thrombosis: A systematic review of case reports
Darío S López-Delgado1, Carlos A Narváez2, Roberto Bonfante-Villalobos3
1Hospital Universitario Departamental de Nariño, Pasto, Nariño, Colombia.

Background:
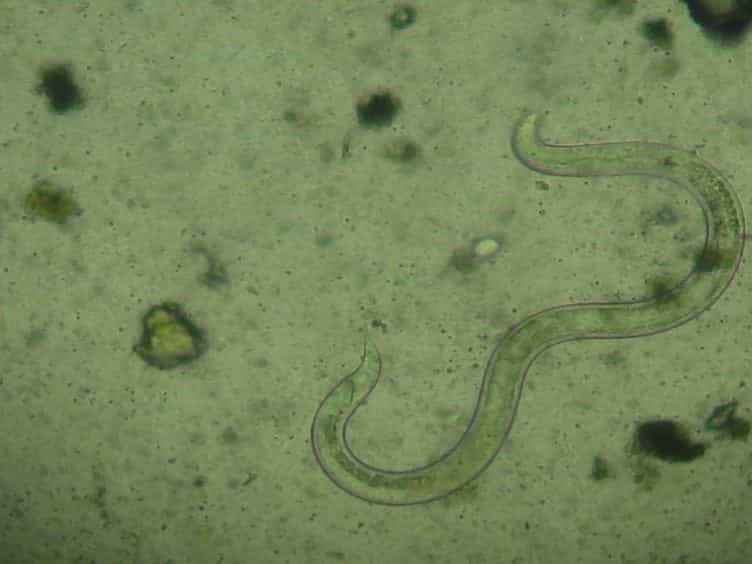
Strongyloides stercoralis hyperinfection syndrome (SHS) is a severe complication of strongyloidiasis, typically in immunosuppressed patients. While sepsis and multiorgan dysfunction are well recognized, the association with thrombotic complications remains underexplored.
Methods:
We conducted a systematic review of case reports and case series following PRISMA 2020 guidelines. PubMed, Embase, Scopus, Web of Science, and Google Scholar were searched through December 2024. Eligible studies included patients with SHS or disseminated strongyloidiasis and confirmed thrombotic events. Data on demographics, risk factors, infection characteristics, thrombosis, treatment, and outcomes were extracted and narratively synthesized.
Results:
Fourteen studies describing 16 cases of SHS with thrombosis published between 2013 and 2024 were included. Median age was 66 years (range 40-87), with a slight male predominance. Most patients (68.8%) were immunosuppressed, primarily due to corticosteroid therapy. Thrombotic events were heterogeneous, including deep vein thrombosis, pulmonary embolism, portal and renal vein thrombosis, intracardiac thrombi, and disseminated intravascular coagulation. Multifocal thrombosis (arterial + venous) occurred in 3/16 (18.8%) cases; shock was present in 5/16 (31.3%). Ivermectin was the mainstay of therapy, alone or with albendazole, although treatment regimens were inconsistently reported. Anticoagulation was frequently initiated, and two cases required thrombectomy. Despite treatment, overall mortality reached 31.3%, particularly among immunosuppressed patients with shock or disseminated thrombosis.
Conclusions:
SHS can be complicated by diverse and often fatal thrombotic events, especially in immunosuppressed individuals. Clinical suspicion should be heightened in patients from endemic regions or those receiving corticosteroids. Early empiric antiparasitic therapy, timely investigation for thrombotic complications, and individualized anticoagulation strategies are essential to improving outcomes. Given the reliance on case-level evidence, prospective studies and standardized reporting are urgently needed to characterize better risk factors, optimal management, and prognosis of this neglected but critical complication.


Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Venous Thrombosis I: Introduction
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...