Optimizing prostate biopsy: the role of targeted, regional, and systematic approaches
Related Experiment Video
Updated: Jan 9, 2026
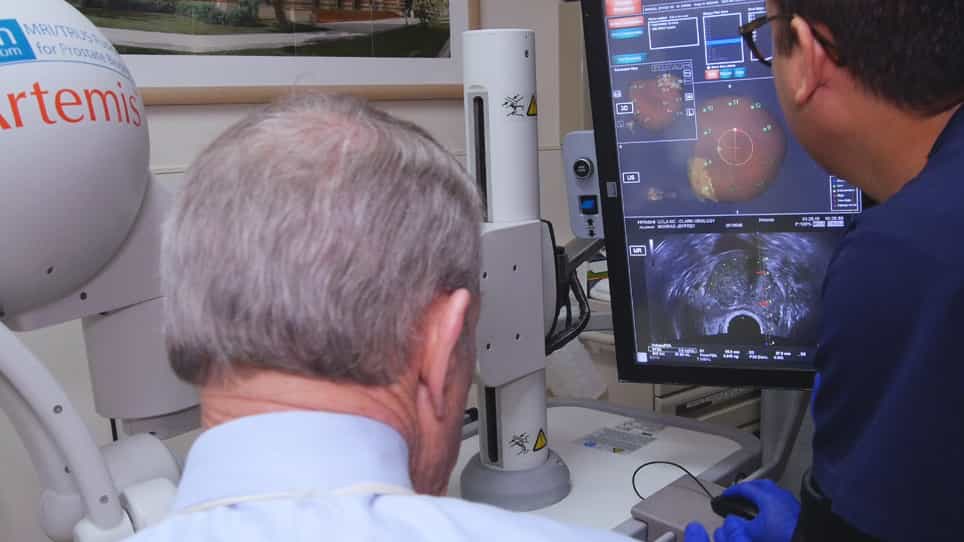
Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Kayhan Tarim1,2, Hasim Bakbak3, Ahmet Furkan Sarikaya4
1Department of Urology, Koc University, Istanbul, Turkey. ktarim@ku.edu.tr.

Abstract:
PURPOSE: Prostate biopsy remains the gold standard for diagnosing prostate cancer (PCa). Recent studies suggest that the necessity and contribution of systematic biopsy (SB), where the entire prostate is sampled, are decreasing. The EAU has updated its guidelines, replacing the recommendation of targeted biopsy (TB) + SB with TB + regional biopsy (RB). This study aims to compare the detection rates of TB alone, TB + RB, and TB + SB combinations. METHODS: 803 patients with a single lesion on mpMRI who underwent TB + SB between 2019 and 2025 were retrospectively analyzed. All patients underwent TB + SB, and each core was reported separately and grouped into categories as TB, TB + RB, TB + SB. RESULTS: In PIRADS 3 and 5 lesions, TB alone performed similar to TB + SB in detecting clinically significant prostate cancer (csPCa) (p = 0.063 and p = 0.5). In the PIRADS 4 group, TB’s sensitivity was 80.5% (p < 0.001). Among 23 PIRADS 4 patients where csPCa was detected by SB but missed by TB, the lesions were smaller in size (7.15 mm vs. 9.88 mm, p < 0.001). ROC analysis determined a cut-off value of 9.25 mm. In lesions < 9.25 mm, csPCa was detected in 59 patients, with TB detecting 39 of these (66.1%) (p < 0.001). TB + RB detected 56/59 (94.9%) csPCa in < 9.25 mm lesions (p = 0.125). For PIRADS 4 lesions ≥ 9.25 mm, csPCa was detected in 59 patients, with TB detecting 56 of these (94.9%) (p = 0.25). CONCLUSION: The findings suggest that the current recommendation of TB + RB may not be universally optimal and biopsy strategies can be individualized based on PIRADS score, location, and size.TB + RB is essential for optimizing csPCa detection in PIRADS 4 lesions < 9.25 mm. In contrast, TB alone may be adequate for PIRADS 4 lesions ≥ 9.25 mm, PIRADS 5 lesions, non–peripheral zone lesions, and lesions involving both hemiglands, without compromising csPCa detection. Furthermore, the addition of RB or SB to TB, increases the detection of clinically insignificant prostate cancer (CIPC) in PIRADS 3 lesions, PIRADS 4 lesions ≥ 9.25 mm, and non–peripheral zone lesions.

