Related Experiment Video
Updated: May 2, 2026

A Mobile Outside-in Technique of Transforaminal Lumbar Endoscopy for Lumbar Disc Herniations
Published on: August 7, 2018
Risk Factors for Residual Back Pain After Percutaneous Endoscopic Lumbar Discectomy for Lumbar Disc Herniation: A
Zhengao Huang1, Hao Chen2, Yi Ding3
1The Fourth School of Clinical Medicine, Zhejiang Chinese Medical University, Hangzhou First People's Hospital, Hangzhou, China.

Objective:
To investigate the incidence and risk factors for residual back pain in lumbar disc herniation (LDH) patients after percutaneous endoscopic lumbar discectomy (PELD).` METHODS: We retrospectively analyzed prospectively collected data from consecutive patients with LDH who underwent PELD from May 2021 to September 2022. Back pain intensity was assessed using a visual analog scale after surgery. Residual back pain was defined as persistent moderate-to-severe pain (average visual analog scale score≥ 4) at 1 day and 1 month postoperatively, and the variables comprised the patients' characteristics, radiological parameters, surgical factors, and postoperative factors. Univariate and multivariate logistic regression analyses were performed to identify risk factors.
Results:
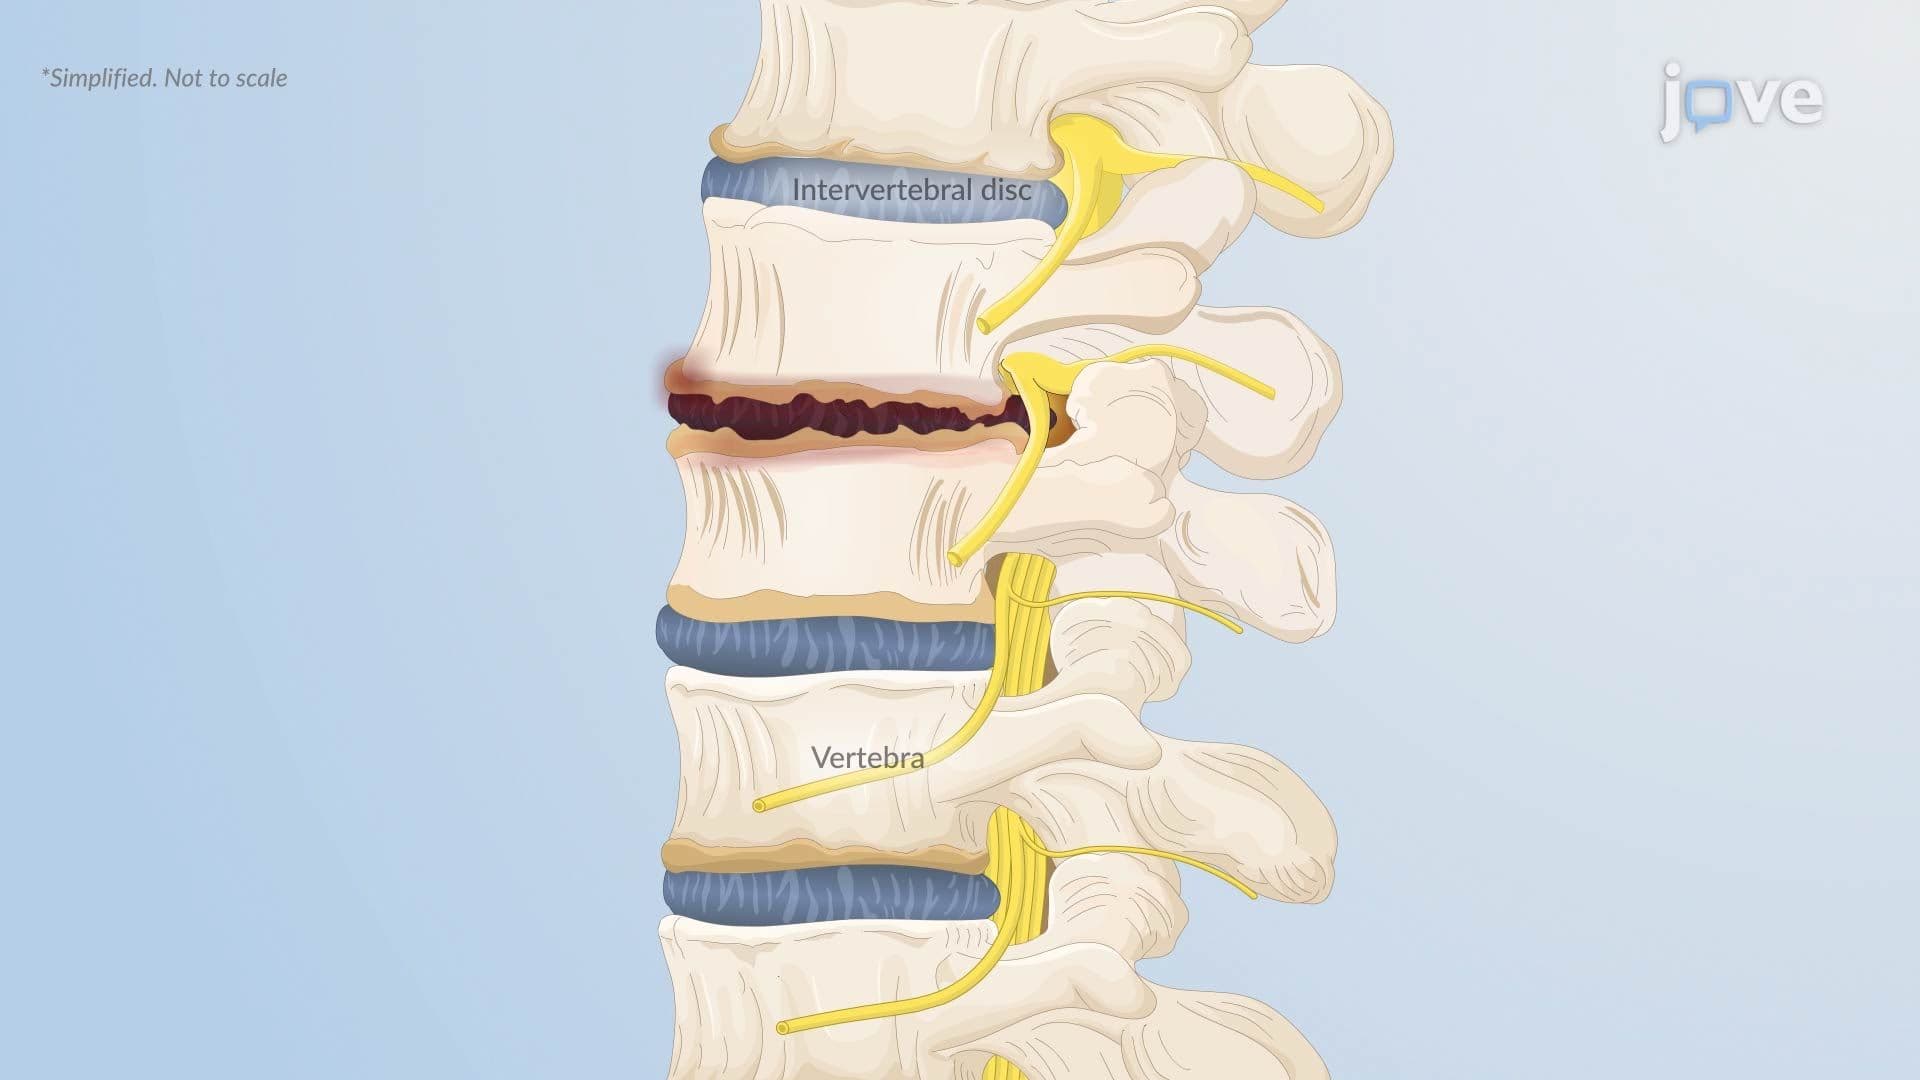
A total of 563 patients were included, and residual back pain was identified in 129 (22.9%). Multivariate analysis identified the following independent risk factors: Modic change (odds ratio (OR) = 1.895; P < 0.001), cartilage endplate injury (OR = 2.587; P = 0.019), unsuitable posterior longitudinal ligament incision (OR = 3.205; P = 0.001), prolonged bracing (OR = 2.044; P = 0.016), and depression (OR = 2.785; P = 0.016).
Conclusions:
In patients with LDH, Modic change, cartilage endplate injury, unsuitable posterior longitudinal ligament incision, prolonged orthosis use, and depression were identified as independent risk factors for residual back pain after PELD. These factors can inform clinical decision-making for surgeons.