Related Experiment Video
Updated: Jan 9, 2026
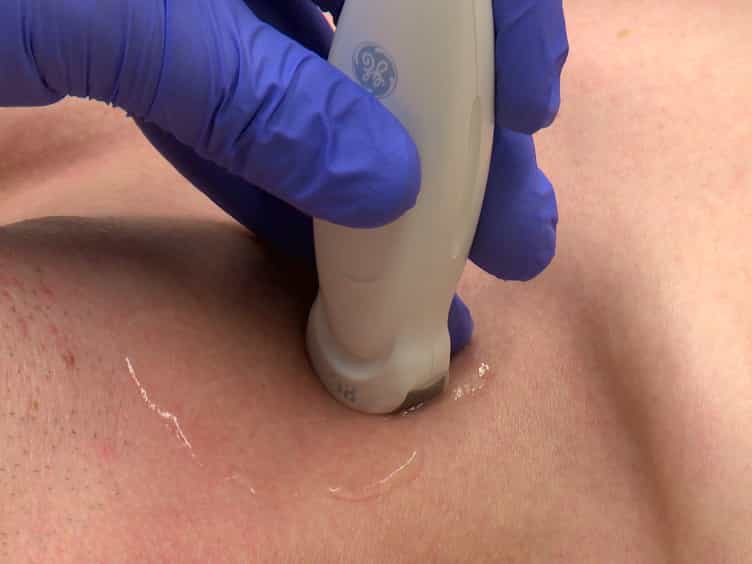

The Supraclavicular Fossa Ultrasound View for Central Venous Catheter Placement and Catheter Change Over Guidewire
Published on: December 23, 2014
Site-specific complications of central venous catheterization under systematic ultrasound guidance: a target trial
Nicolas Boulet1, Antoine Gavoille2,3, Jeanne Iachkine4
1UR-UM103 IMAGINE, Univ Montpellier, Intensive Care Unit, Department of Anesthesiology, Critical Care, Pain and Emergency Medicine, Nîmes University Hospital, Place du Professeur Debré, 30900, Nîmes, Gard, France. nicolas.boulet@chu-nimes.fr.

Background:
Central venous catheterization is the most common invasive procedure in intensive care units but remains burdened by infectious, thrombotic, and mechanical complications. Although real-time ultrasound guidance is now widely adopted, its effect on site-specific differences in overall complication rates has not been established. The 3SITES randomized clinical trial previously demonstrated lower infection and thrombosis rates with subclavian access but higher mechanical complications. However, as only a third of its procedures were ultrasound-guided in this study, these findings may not apply to current practice. The objective of the study was to compare complication rates across these three sites under a counterfactual framework assuming universal ultrasound guidance.
Methods:
This study was an emulated a target trial using the 3SITES dataset. Inverse probability weighting was applied to adjust for confounders of site assignment and ultrasound guidance. Weighted outcomes across catheter sites were compared under a counterfactual framework assuming universal ultrasound guidance. The primary outcome was a composite of time to catheter-related bloodstream infection or symptomatic deep-vein thrombosis. Secondary outcomes included each component separately, asymptomatic thrombosis, and major mechanical complications.
Results:
A total of 3409 catheters were included: 1153 in the femoral, 1267 in the internal jugular, and 989 in the subclavian site. Subclavian site showed a lower incidence of the primary outcome compared with femoral (P = .02) and jugular (P = .001) sites. The primary composite outcome did not differ between internal jugular and femoral sites (P = .97). Catheter-related bloodstream infections were significantly fewer with subclavian versus jugular access (P = .001). Asymptomatic thrombosis was more frequent at femoral and jugular sites. Major mechanical complications were rare and did not differ significantly across sites.
Conclusion:
Assuming universal real-time ultrasound-guided central venous catheterization, subclavian access retains lower infectious and thrombotic risk without an observed increase in mechanical complications, supporting its preferential use in intensive care units.
More Related Videos
Related Concept Videos
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:26
Cardiac Catheterization IV: Nursing Management
 01:17
Ultrasonography
During an ultrasonography procedure, a handheld device called...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:22
Aneurysm IV: Nursing Management