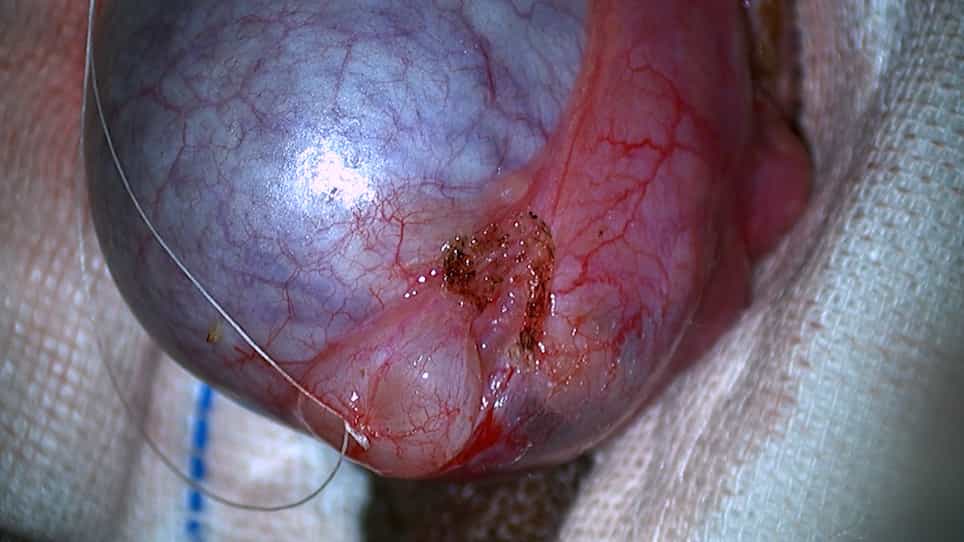
Unilateral testicular rupture after blunt scrotal trauma: A case report and literature review
Related Experiment Video
Updated: Jan 9, 2026
Combined Supine and Standing Imaging for Varicocele: An Improved Diagnostic Approach
Published on: November 22, 2024
Denis Mucunguzi1, Donald Dominick Lema2, Orgeness Jasper Mbwambo2
1Faculty of Medicine, KCMC University, P.O BOX 3010, Moshi, Tanzania; Department of Urology, Kilimanjaro Christian Medical Centre, P.O BOX 3010, Moshi, Tanzania; Division of Urology, Mbarara University of Science & Technology, P.O BOX 1410, Mbarara, Uganda.

Introduction:
Testicular trauma, accounting for up to 66 % of urological injuries, mainly affects males aged 15 to 40 due to sports, violence, and traffic accidents. Rupture occurs in 48 % to 60 % of blunt injuries, often involving the right testis. Early ultrasonographic diagnosis and prompt surgical exploration are vital to prevent complications, infertility, or orchiectomy.
Case Presentations:
A 57-year-old man presented with a three-month history of right-sided scrotal swelling following blunt perineal trauma from a fall. Initial treatment with analgesics and antibiotics from lower level health facilities relieved pain but not swelling. Examination revealed a non-tender, irreducible right scrotal mass with a non-palpable right testis. Ultrasound showed a large, mixed-echo fluid collection with increased peripheral vascularity. Laboratory results were normal. A differential diagnosis of scrotal haematoma versus abscess was made, prompting surgical exploration. Intraoperatively, a 150 mL old haematoma and a ruptured right testis (AAST grade V) with torn tunica albuginea, extruded seminiferous tubules, and necrotic tissue were found. A right orchiectomy and debridement were performed. Hemostasis was achieved, and layered closure of the scrotum was completed using absorbable sutures. The postoperative course was uneventful, and at one-month follow-up, the patient had recovered well. Early evaluation and surgical intervention were key to an optimal outcome in this case of delayed testicular rupture.
Discussion:
Blunt testicular trauma, although rare, requires early ultrasonographic assessment and immediate surgical exploration to maximise testicular salvage and minimise orchiectomy rates. Ruptures often occur from sports or falls, with atypical presentations making diagnosis more difficult. The AAST grading system informs treatment, and early intervention enhances fertility, hormonal function, and psychosocial outcomes.
Conclusion:
Testicular rupture is uncommon but serious, requiring prompt assessment to optimise testicular preservation, especially in high-risk patients.