Related Experiment Video
Updated: Jul 14, 2026
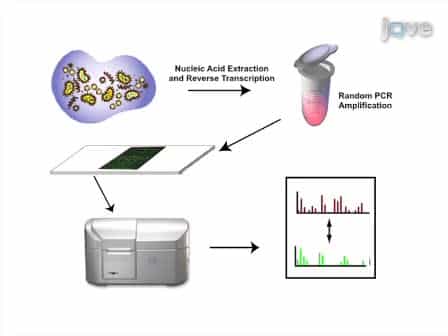

Using a Pan-Viral Microarray Assay Virochip to Screen Clinical Samples for Viral Pathogens
Published on: April 27, 2011
Impact of Multiple Viral Detections by FilmArray® on the Severity of Pediatric Respiratory Infections: A
Shinya Tomori1, Kazuhiro Takahashi1, Masakazu Mimaki1
1Pediatrics, Teikyo University School of Medicine, Tokyo, JPN.

Abstract:
Introduction FilmArray® Respiratory Panel (FA) is a rapid multiplex polymerase chain reaction (PCR) assay that can detect various viruses. While some studies have indicated that viral co-infections might exacerbate severity, others have found no notable difference when compared to single-virus infections, leaving the overall impact uncertain. Methods We retrospectively reviewed pediatric patients diagnosed with viral respiratory infections who underwent FA testing at the Teikyo University Hospital between April 2020 and March 2025. Only cases of viral detection were included. FA detects pathogens, including severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), human metapneumovirus (hMPV), human rhinovirus/enterovirus, influenza A and B viruses, human parainfluenza virus type 1-4, respiratory syncytial virus (RSV), common coronaviruses, and adenovirus. Clinical severity indicators were compared between the single- and multiple-virus groups using multivariate regression. Patients with Bordetella pertussis, Bordetella parapertussis, Chlamydophila pneumoniae, and Mycoplasma pneumoniae detected by FA were excluded because bacterial infection was the primary cause. Although secondary bacterial pneumonia often follows viral infection, cases with significant bacteria identified through sputum or blood cultures were excluded as bacterial pneumonia cases. Moreover, patients with a positive rapid test for group A β-hemolytic streptococcus and suspected streptococcal infection were excluded from the analysis. Results Of 122 patients (median age 1.8 years), 83 (68.0%) had single-virus detection and 39 (32.0%) had multiple-virus detection. Rhinovirus/enterovirus (38.2%), RSV (17.6%), and hMPV (14.7%) were the most common viruses detected. There were no significant differences in hospital stay (median 6.0 days, p=0.43) between the groups. Similarly, there were no significant differences in clinical severity, chest retraction (OR=2.00, p=0.10, 95% CI=0.87-4.82), pneumonia (OR=1.06, p=0.88, 95% CI=0.48-2.36), poor oral intake (OR=0.76, p=0.48, 95% CI=0.34-1.65), oxygen requirement (OR=0.96, p=0.92, 95% CI=0.44-2.14), tachypnea (OR=0.81, p=0.62, 95% CI=0.36-1.86), or worsening symptoms after admission (OR=1.18, p=0.77, 95% CI=0.39-4.06) between the groups. In addition, subgroup analyses were conducted based on age group, presence or absence of underlying medical conditions, presence or absence of RSV co-infection, co-infections with rhinovirus/enterovirus and single-virus infection, and co-infections with rhinovirus/enterovirus and those without rhinovirus/enterovirus. However, no significant differences were observed between groups. Conclusion Viral detection counts from multiplex PCR should not solely guide treatment, as clinical findings remain crucial for assessing severity. While multiple detections did not correlate with worse outcomes, the limited sample size requires careful interpretation. Further prospective studies are needed to determine the significance of viral codetection in children.


Related Concept Videos
 01:27
Cytomegalovirus Disease
 01:29
Respiratory Syncytial Virus Disease