Related Experiment Video
Updated: Jan 9, 2026
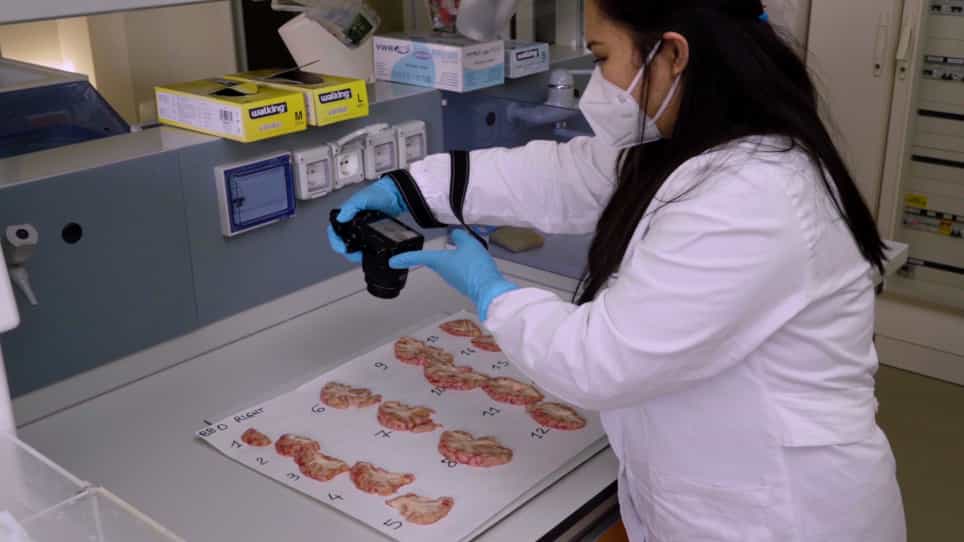
Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Longitudinal assessment of cognitive decline and resilience in high-level Alzheimer disease neuropathologic change
Timothy E Richardson1,2, Shrishtee Kandoi3,4,5, Francisco C Almeida6,7,8
1Department of Pathology, Molecular and Cell-Based Medicine, Icahn School of Medicine at Mount Sinai, 1468 Madison Ave, New York, NY, 10029, USA. timothy.richardson@mountsinai.org.

Abstract:
BACKGROUND: Alzheimer disease neuropathologic change (ADNC) is the most common pathology underlying cognitive impairment and dementia in the aging population, but there is significant variation in outcome between affected individuals. Moreover, other common neurodegenerative processes are often concurrent and may significantly worsen cognition, but the degree to which these processes interact and affect the rate of cognitive decline remains unclear. Herein, we aim to investigate features influencing cognitive trajectories over the final 15 years of life in individuals with high-level ADNC. METHODS: We performed a cross-sectional cohort study of 586 participants from the National Alzheimer’s Coordinating Center (NACC) database, who were ≥ 65 years of age and displayed high-level ADNC at autopsy, and who had available longitudinal cognitive data and Clinical Dementia Rating (CDR) performed within the final 24 months of life. This cohort was subdivided into “resilient” individuals/those with minimal progression of cognitive decline (MinP; n = 75), intermediate/moderate progression of cognitive decline (ModP; n = 255), and rapid/maximal progression of cognitive decline (MaxP; n = 256) as determined by global cognitive performance and the rate of cognitive decline. Demographic, neuropathologic, genetic, and clinical features were evaluated using multivariable logistic regression analysis. RESULTS: Individuals with rapid progression were more likely to have at least one APOE ε4 allele (OR: 2.08 [95% CI: 1.16–3.74], p < 0.01), higher Braak stage (2.19 [1.20–3.98], p < 0.01), higher Thal phase (2.45 [1.24–4.83], p < 0.01), more severe white matter rarefaction (1.68 [1.21–2.35], p < 0.01), and in the final 24 months of life, more frequent untreated/undertreated hyperlipidemia (1.74 [1.35–5.56], p < 0.01) and less frequent untreated/undertreated depression (0.40 [0.17–0.91], p < 0.05). Conversely, resilient individuals harbored less frequent APOE ε4 alleles (0.17 [0.06–0.55], p < 0.01), lower Thal phase (0.33 [0.12–0.95], p < 0.05), lower CERAD neuritic plaque score (0.32 [0.11–0.97], p < 0.05), less frequent untreated/undertreated psychosis (0.06 [0.01–0.39], p < 0.01), and more frequent untreated/undertreated depression (8.73 [2.12–35.85], p < 0.01). CONCLUSIONS: These data suggest that resilience and progression in ADNC are impacted by AD-relevant genetics and the severity of late-stage ADNC (even within the narrow range of values compatible with high-level ADNC), additional pathologic features, and potentially the clinical management of underlying systemic disorders.
More Related Videos
 07:47
Longitudinal In Vivo Imaging of the Cerebrovasculature: Relevance to CNS Diseases
Published on: December 6, 2016
 10:02
Assessment of Spontaneous Alternation, Novel Object Recognition and Limb Clasping in Transgenic Mouse Models of Amyloid-β and Tau Neuropathology
Published on: May 28, 2017
Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ...
 01:30
Cognitive Development During Adulthood
 01:22
Alzheimer's Disease: Treatment