Related Experiment Video
Updated: Jan 9, 2026
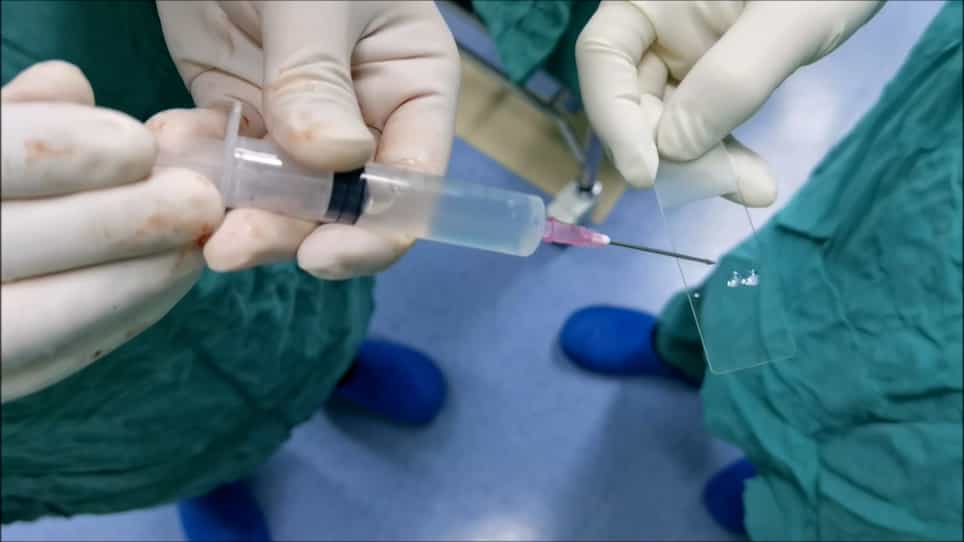

Clinical Application of 24 G Cannula Needle and 3-0 Polypropylene Suture in Vas Deferens Exploration
Published on: February 10, 2023
Contralateral exploration during open inguinal hernia repair in infants aged 0-6 months to prevent recurrent hernia
Sanne C Maat1, Kelly M A Dreuning1, HanR Anema2
1Department of Pediatric Surgery, Emma Children's Hospital, Amsterdam University Medical Center, University of Amsterdam & Vrije Universiteit Amsterdam, Amsterdam Reproduction and Development Research Institute and Amsterdam Gastroenterology Metabolism & Endocrinology, Amsterdam, the Netherlands.

Background:
An metachronous contralateral inguinal hernia (MCIH) occurs in 7%-15% of infants undergoing unilateral hernia repair, requiring a second anesthesia and surgery. Contralateral exploration (CE) can prevent development of MCIH, but also exposes infants to additional risks if no contralateral hernia is present. This study assesses the (cost)effectiveness of open primary unilateral inguinal hernia repair with and without CE in infants aged 0-6 months to prevent second surgery for MCIH.
Methods:
This multicenter randomized controlled trial randomly assigned infants to open unilateral inguinal hernia repair with CE (intervention group) or without CE (control group). Infants aged 0-6 months with a primary unilateral inguinal hernia undergoing open hernia repair were eligible for inclusion. The primary outcome was the number of re-operations within 1 year after the primary surgery and the subsequent number needed to treat (NNT). Secondary outcomes included operation time, hospital admission(s), complications, parental distress, and anxiety. An additional economic evaluation was performed.
Results:
Re-operation was performed in four out of 204 patients in the intervention group and 12 out of 198 patients in the control group [2.0% vs 6.1%, OR 95% CI 0.3 (0.1-1.0)], with a NNT of 24. Six re-operations in the control group were because of MCIH. Mean total operation time was shorter in the control group. Hospital admission, complication rate, and parental distress and anxiety did not differ between groups. The intervention had a relatively high probability of being cost-effective.
Conclusion:
Additional CE results in fewer re-operations compared with unilateral repair alone. However, the NNT is high ( n = 24); therefore, CE should not be implemented as standard care.

