Related Experiment Video
Updated: Jan 6, 2026
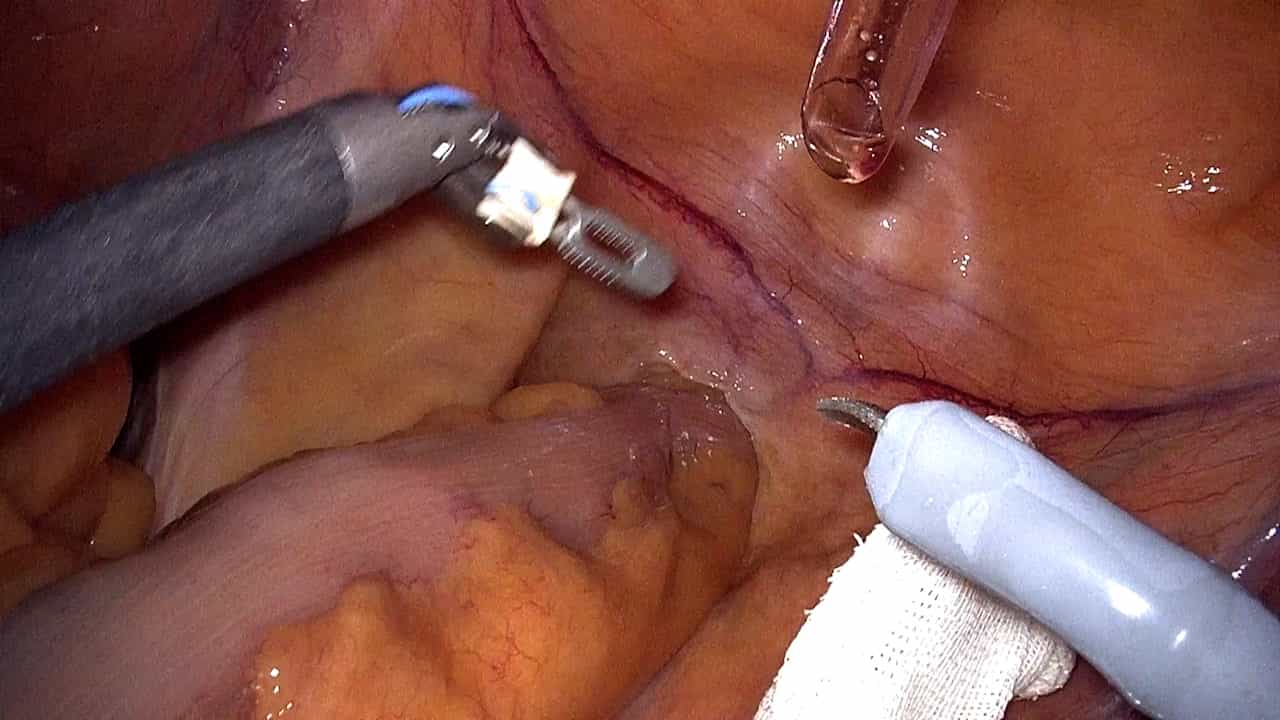
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
Prevalence of and risk factors for low anterior resection syndrome based on the international consensus definition: a
Yosuke Atsumi1, Masakatsu Numata2, Koji Numata3
1Department of Surgery, Gastroenterological Center, Yokohama City University Medical Center, 4-57 Urafune-cho, Minami-ku, Yokohama, 232-0024, Kanagawa, Japan.

Purposes:
The symptoms of low anterior resection syndrome (LARS) are diverse, and its ambiguous definition has made estimating its prevalence difficult. In 2018, an international consensus proposed a new LARS definition based on eight symptoms and consequences. We conducted this study to evaluate the prevalence of LARS, using this new definition (LARS-ND), and to identify its risk factors.
Methods:
This multicenter, cross-sectional study surveyed patients who underwent curative resection for rectal tumors between 2020 and 2022 at 10 institutions. A one-time questionnaire based on the new LARS definition was distributed. Outcomes included LARS-ND prevalence and risk factors.
Results:
A total of 343 patients responded (response rate: 86.6%). The prevalence of LARS-ND was 72.5%, with no significant differences across groups with different follow-up durations. The most frequent symptom and consequence were "emptying difficulties" (93.3%) and "the need for strategies and compromises" (47.5%). Among patients categorized as having "no LARS" by the conventional score, 25% were diagnosed with LARS-ND. Multivariate analysis identified younger age (< 70 years; OR = 2.28) and short anastomosis distance (≤ 5 cm; OR = 1.96) as risk factors.
Conclusions:
The prevalence of LARS-ND was high, and the new LARS definition identified patients with symptoms previously missed by the conventional score. Younger age and a lower anastomosis level appear to be risk factors for LARS-ND.


