Related Experiment Video
Updated: Jan 9, 2026
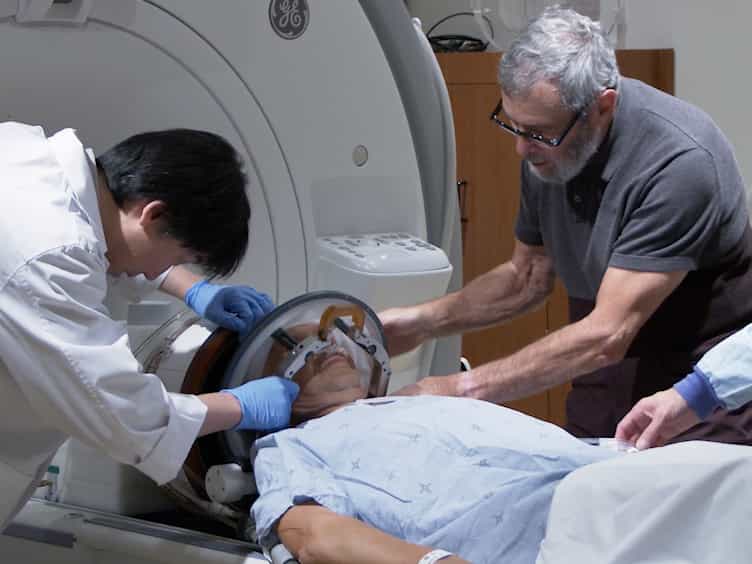

MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
Preoperative Treatment with Bisphosphonates Does Not Change the Thermal Response of Focused Ultrasound Thalamotomy
Matthew C Henn1, Nemanja Useinovic1, James Cahill1
1Department of Neurological Surgery, Oregon Health and Science University, Portland, Oregon, USA.

Introduction:
Skull density ratio (SDR) is an important criterion for predicting efficacy of high-intensity focused ultrasound (HIFU) thalamotomy for essential tremor and tremor-dependent Parkinson's disease. Bisphosphonates are known to increase bone density and are postulated to raise SDR and improve HIFU energy transmission efficiency. However, the impact of bisphosphonate pre-treatment on HIFU outcomes has not been investigated.
Methods:
A retrospective analysis was conducted on the sonication parameters of patients with SDR <0.45 who were pre-treated off-label with bisphosphonates prior to HIFU. For comparison, the sonication parameters were also collected for patients with SDR <0.45 not pre-treated with bisphosphonates, patients with mid-range SDR (0.45-0.49), and patients with high SDR (0.5-0.55). All patients underwent HIFU thalamotomy between March 2022 and December 2024.
Results:
The bisphosphonate pre-treatment group (28 patients) and the low-SDR untreated group (29 patients) both had mean SDRs of 0.41. Respectively, the bisphosphonate-treated and low-SDR untreated group had mean final sonication energy of 23 kJ versus 26 kJ, final sonication duration of 27.1 versus 28.6 s, mean maximum temperature of 52.8°C versus 53.2°C, and average of 5.6 versus 4.9 sonications per treatment (p > 0.05 for each comparison). No significant differences between the two low-SDR groups were found for the thermal efficiency of sonication. Compared to the bisphosphonate-treated low-SDR group, the mid- and high-SDR groups exhibited significantly decreased sonication energy (p < 0.0001), final sonication duration (p < 0.0001), and higher final sonication max temperature (p < 0.01). Across all patients, a negative correlation was observed between SDR and final sonication energy (p < 0.0001, r = -0.48) and a positive correlation was observed between SDR and last sonication temperature (p < 0.005, r = 0.27), although in the low-SDR cohort, a correlation was not observed. No clinically significant differences were found in demographics, self-reported tremor improvement, or incidence of side effects.
Conclusion:
No significant differences were found in sonication response parameters between the bisphosphonate-treated and untreated low-SDR groups, whereas mid- and high-SDR groups had significantly reduced sonication energy and time to produce greater heat. These findings show that while bisphosphonates are an established way of raising bone density in osteoporosis, pre-treatment with bisphosphonates does not shift the sonication response from that of a low SDR to a mid-range SDR. Additionally, other factors besides just skull density likely determine the thermal response to sonication.
More Related Videos
 14:10
Contrast Ultrasound Targeted Treatment of Gliomas in Mice via Drug-Bearing Nanoparticle Delivery and Microvascular Ablation
Published on: December 15, 2010
 13:41
Magnetic Resonance-Guided High Intensity Focused Ultrasound Generated Hyperthermia: A Feasible Treatment Method in a Murine Rhabdomyosarcoma Model
Published on: January 13, 2023