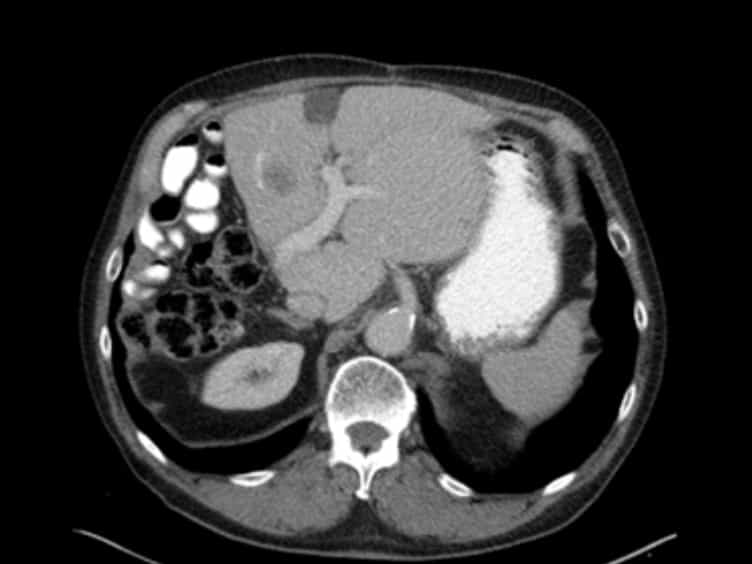
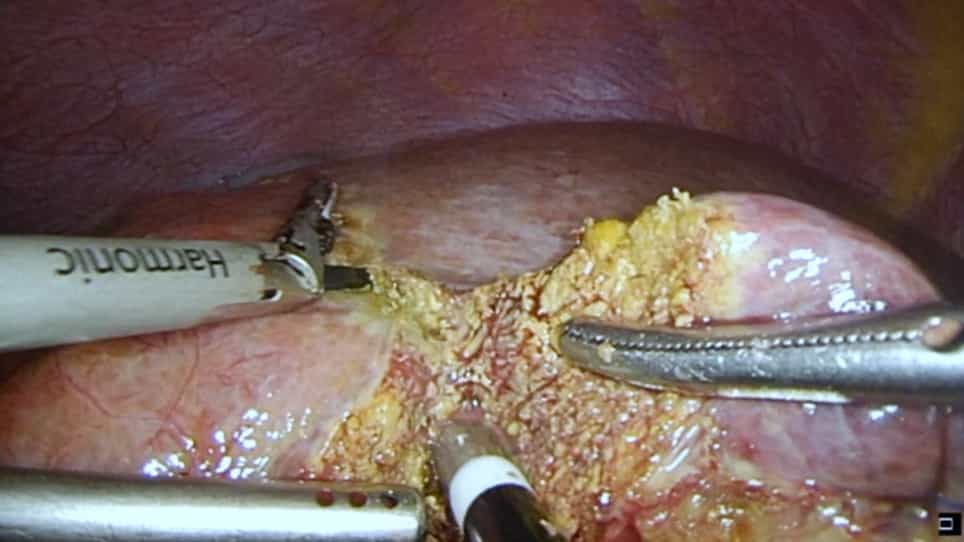
Related Experiment Video
Updated: Jan 9, 2026

Author Spotlight: Investigating Immune Cell Dynamics in the Tumor Microenvironment — Challenges and Innovations in Cancer Prognosis
Published on: April 12, 2024
The overarching prognostic role of tumor progression prior to cytoreductive hepatectomy in NETLM
Vanja Podrascanin1, Markus Ammann1, Hallbera Gudmundsdottir2
1Department of Surgery, Division of Hepatobiliary and Pancreas Surgery, Mayo Clinic, Rochester, MN, USA; Department of Surgery, University Clinic Wiener Neustadt, Wiener Neustadt, Austria.

Background:
Cytoreductive hepatectomy can offer prolonged survival in patients with neuroendocrine tumor liver metastases (NETLM) but reliable predictors of early mortality, particularly in patients with otherwise similar clinical characteristics, remain unclear. This study aimed to identify preoperative predictors of early mortality following cytoreductive hepatectomy for well-differentiated NETLM.
Methods:
We retrospectively analyzed patients who underwent cytoreductive hepatectomy for well-differentiated NETLM at Mayo Clinic Rochester (2000-2020). Patients were stratified as short-term (<3 years) or long-term (≥3 years) survivors. Preoperative hepatic tumor progression was assessed using RECIST 1.1. Multivariate and subgroup analyses identified predictors of survival.
Results:
Among 383 patients, 13 % (n = 51) were short-term and 87 % (n = 332) long-term survivors. Preoperative hepatic progressive disease (PD) per RECIST was significantly more frequent in short-term (47 %) than in long-term survivors (16.6 %, p < 0.001). Patients with pancreatic neuroendocrine tumors (PNET), grade 3 (G3), and RECIST-PD had particularly poor median overall survival (mOS: 1.8 years, p = 0.042). In contrast, among patients with stable disease, survival did not differ by tumor origin (PNET 9.5 years; small bowel neuroendocrine tumors (SBNET) 10 years). Tumor growth >20 % and weekly growth >1.04 % were associated with early mortality (p < 0.001). RECIST-PD (HR: 2.23), larger hepatic metastases (HR: 1.07), and shorter progression-free survival (HR: 1.13) independently predicted worse OS (p < 0.001).
Conclusion:
Preoperative hepatic tumor progression is the strongest independent predictor of early mortality following hepatectomy for NETLM. In the absence of progression, long-term survival is excellent regardless of tumor origin. These findings support incorporating objective tumor progression metrics into preoperative surgical selection.