Related Experiment Video
Updated: Jan 9, 2026

Normothermic Negative Pressure Ventilation Ex Situ Lung Perfusion: Evaluation of Lung Function and Metabolism
Published on: February 14, 2022
Pressure Support Ventilation in Neurosurgical Patients: Can We Safely Reduce Assistance? Evaluation of Neurosurgical
Vorakamol Phoophiboon1,2,3,4, Antenor Rodrigues1,2, Matthew Ko1,2
1Keenan Centre for Biomedical Research, Li Ka Shing Knowledge Institute, Unity Health Toronto, Toronto, ON, Canada.

Objectives:
To identify the prevalence of over-assistance from mechanical ventilation (MV) and to assess whether reducing MV support could be done safely in neurosurgical ICU patients in terms of risk of under-assistance and brain's oxygenation.
Design:
Prospective observation study.
Setting:
Neurosurgical trauma ICU, Toronto, ON, Canada.
Patients:
Twenty-seven brain-injured patients on MV having indication of a spontaneous breathing trial (SBT).
Interventions:
Level of pressure support ventilation (PSV).
Measurements And Main Results:
In neurosurgical patients, regional ventilation distribution using electrical impedance tomography, patient's respiratory drive (airway occlusion at 100 ms [P0.1]), respiratory muscle pressure (Pmus), diaphragm and parasternal intercostal (PI) thickening fraction, brain oximetry, and electroencephalogram were assessed at clinical PSV (ClinPS), low PSV (LowPS, pressure support [PS] 5 cm H2O, positive end-expiratory pressure [PEEP] 5 cm H2O), SBT, PS 0 cm H2O, and PEEP 0 cm H2O. Over-assistance was defined by pressure muscle index less than 0 cm H2O; under-assistance was defined as Pmus greater than or equal to 15 cm H2O. Mixed effects models were used for analysis. Imbalanced dorsal/ventral distribution of ventilation improved by reducing assistance while respiratory effort increased. Over-assistance was present in ten cases (37%) during ClinPS and in none at LowPS and SBT; under-assistance was present in two, four, and seven cases at ClinPS, LowPS, and SBT. During SBT, compliance and end-expiratory lung volume decreased (p < 0.0001). Brain activity did not vary. P0.1 greater than or equal to 4 cm H2O was associated with Pmus greater than or equal to 15 cm H2O with 80% sensitivity and 91% specificity during SBT.
Conclusions:
Neurosurgical patients seem to frequently be overassisted under PSV. Reducing the ventilatory support is often feasible and Pmus and P0.1 can help with detecting under-assistance.
More Related Videos


Related Concept Videos
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:14
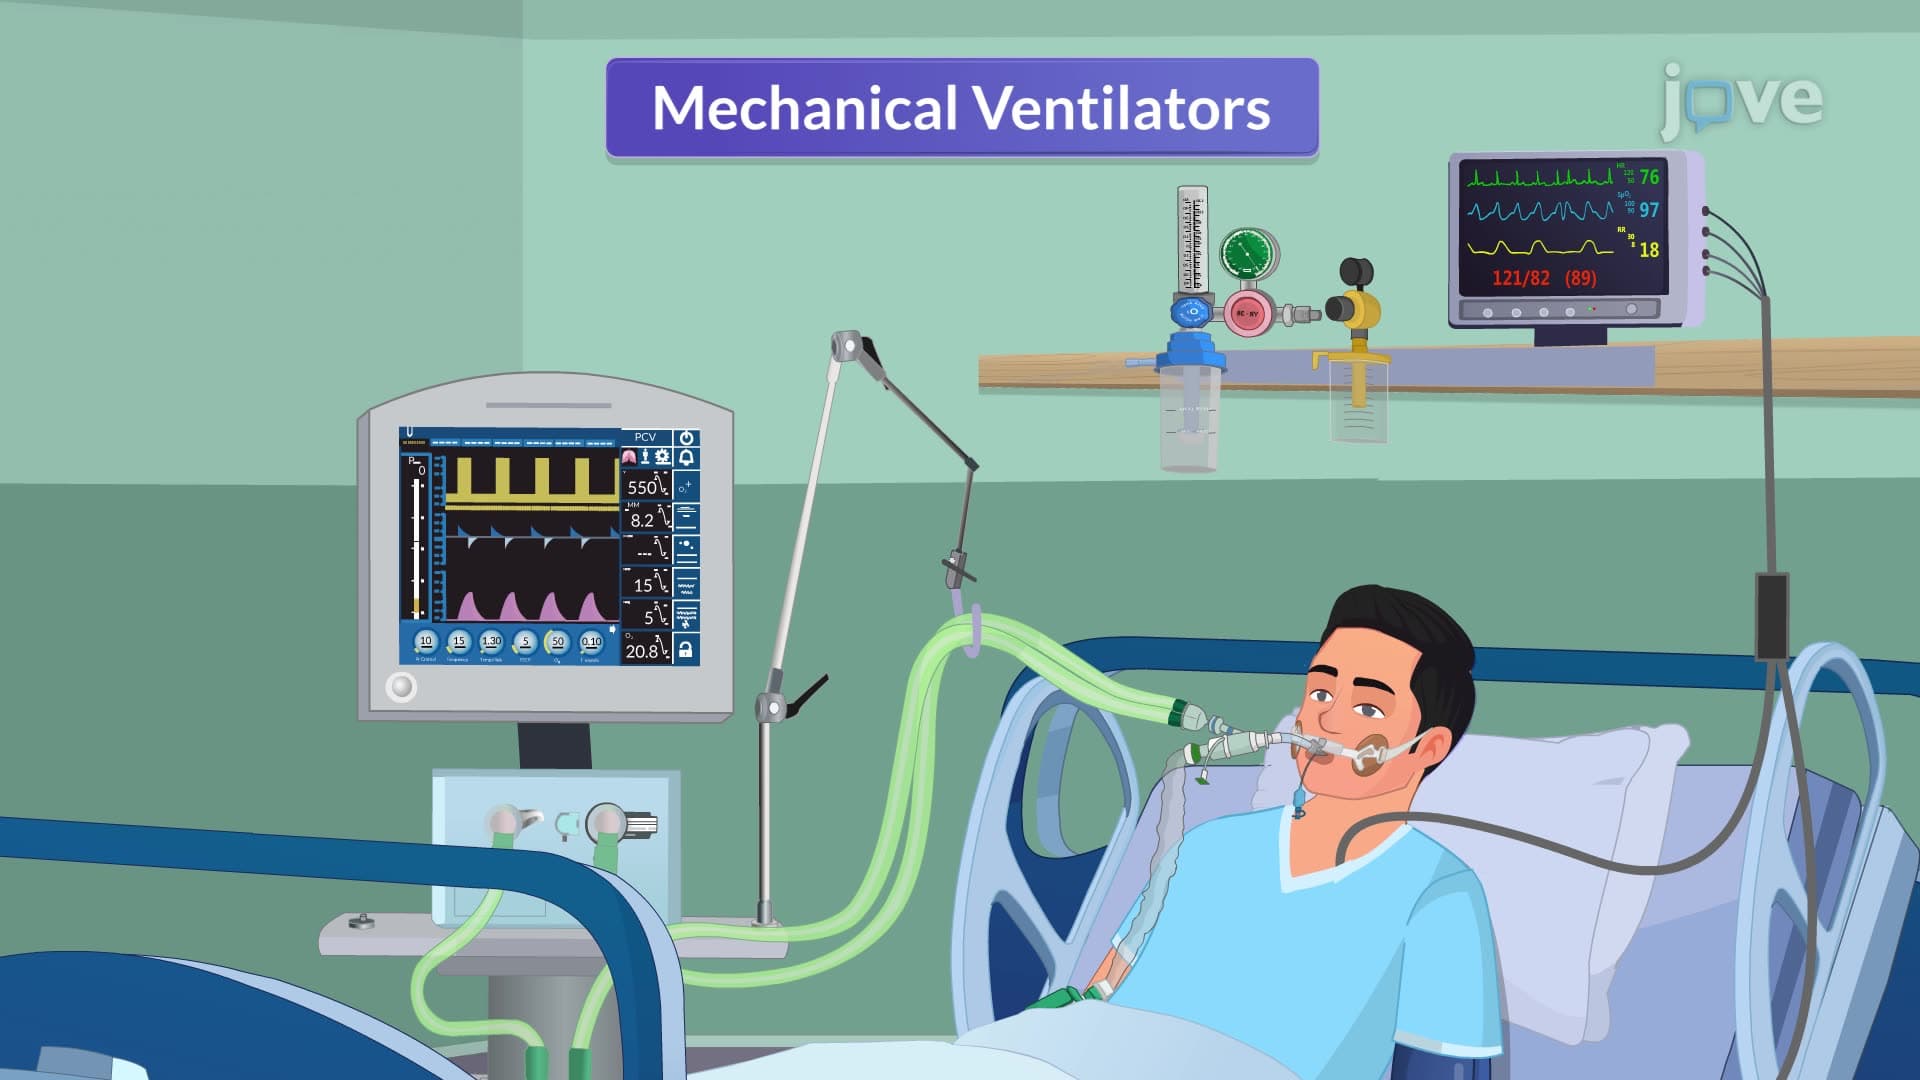
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Mechanical Ventilation I: Indication and Settings
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...