Related Experiment Video
Updated: Jan 9, 2026
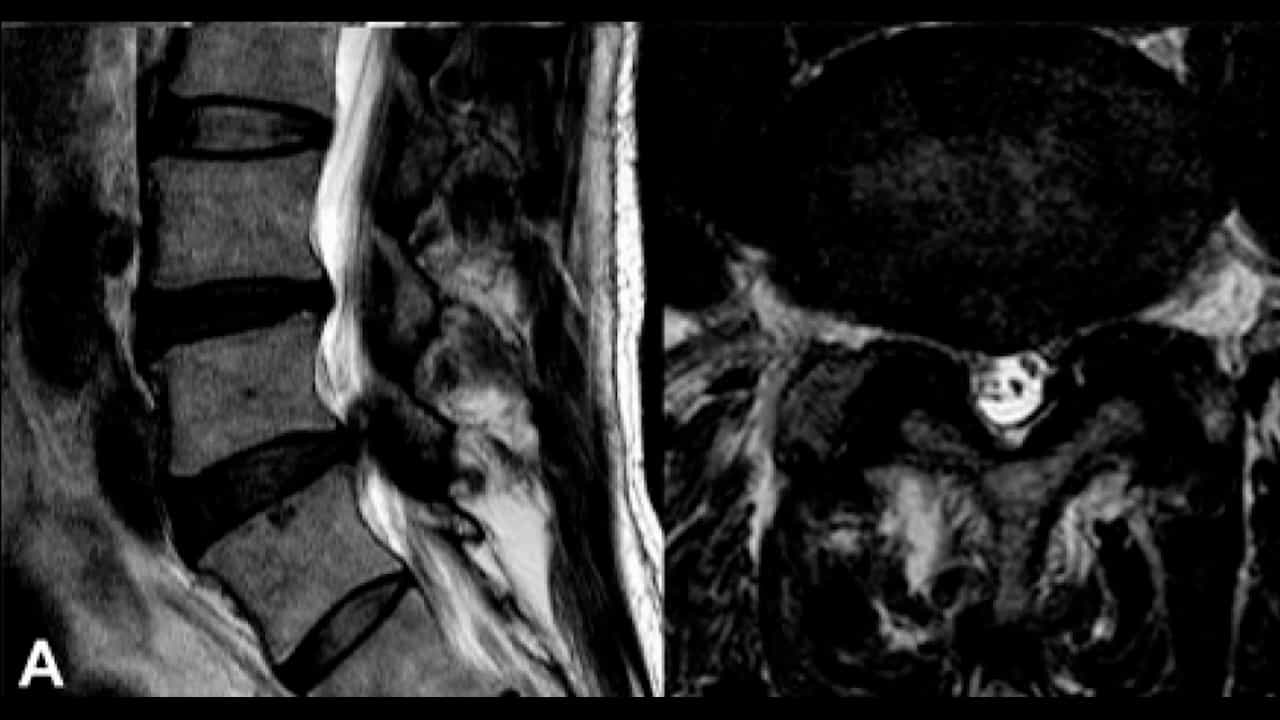

Full-Endoscopic Interlaminar Approach for Decompression of Lateral Recess Stenosis
Published on: February 24, 2023
Achieving Efficiency in Full Endoscopic Interlaminar Lumbar Decompression: A Prospective Learning-Curve Cumulative
José Machado1, Patrícia Martins1, Pedro Mendes Santos1
1Orthopaedics, Hospital Pedro Hispano, Matosinhos, PRT.

Abstract:
Background and objective Full endoscopic interlaminar lumbar decompression is increasingly being adopted for lumbar spinal stenosis, yet the learning curve and its clinical consequences remain uncertain. In this study, we aimed to prospectively evaluate a single surgeon's learning curve for full endoscopic interlaminar decompression. Methods We conducted a prospective, single-surgeon cohort (2018-2023) involving adults who underwent single-level full endoscopic interlaminar decompression for degenerative lumbar canal stenosis. Operative efficiency was prespecified as operative time ≤90 minutes. Learning-curve cumulative summation (LC-CUSUM) was applied to detect the transition from inadequate to adequate performance; competency was declared at the first boundary crossing. Patient-reported outcomes included the Oswestry Disability Index (ODI) and Visual Analog Scale (VAS) scores collected at baseline and at one, three, six, and 12 months. Safety endpoints included major complications and reoperations. Results A total of 77 patients were included (mean follow-up period: 47 months). LC-CUSUM signaled efficiency competency at case 44. Mean operative time was 98.6 ± 29.0 minutes overall; 111.2 ± 32.0 minutes in the early phase group (cases 1-44) and 81.7 ± 10.1 minutes in the late phase group (cases 45-77). Both groups demonstrated significant within-group improvements in ODI and VAS at each postoperative time point; however, the magnitude of improvement did not differ between phases. Major complications (1/44 early vs. 0/33 late) and reoperations (3/44 vs 2/33) were comparable. All patients were discharged within 24 hours. Conclusions Efficiency competency was achieved without compromising patient‑reported outcomes or safety across the learning curve.