Related Experiment Video
Updated: Jan 9, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Population Pharmacokinetic/Pharmacodynamic Model of the Impact of Cumulative Tacrolimus Exposure on Kidney Function
Ningjia Tang1, Shinichirou Maeda1,2, Masahiro Okuda1,2
1Graduate School of Pharmaceutical Sciences, The University of Osaka, Osaka, Japan; and.

Background:
Tacrolimus-induced nephrotoxicity is a common adverse effect after liver transplantation. In this study, we aimed to develop a population pharmacokinetic/pharmacodynamic (PK/PD) model to evaluate the relationships among tacrolimus dose, instantaneous and cumulative exposure, and kidney injury.
Methods:
Data from adult liver transplant recipients with a once-daily tacrolimus formulation were retrospectively analyzed. A sequential population PK/PD modeling approach using nonlinear mixed-effects modeling was applied. Exposure metrics included trough concentrations, the area under the concentration-time curve [area under the curve (AUC)] over a 24-hour (AUC 0-24h ) period, and cumulative AUC (cAUC) over 1-6 months. Renal function was defined as the change in estimated glomerular filtration rate (eGFR). Demographics, biochemical parameters, and concomitant medications were evaluated as covariates.
Results:
Tacrolimus trough concentrations and eGFR measurements were obtained from a total of 44 patients for 3360 and 3504 measurements, respectively. Tacrolimus PK was best described by a one-compartment model with additive interindividual variability. Clearance was influenced by hematocrit (HCT) and postoperative days (PODs) within the first 14 days. Among exposure metrics, only cAUC over 3 months was significantly associated with renal function decline and provided the best model fit. The final PK/PD model was a direct linear model, with baseline eGFR identified as a covariate on the slope, reflecting individual susceptibility to tacrolimus-associated renal changes.
Conclusions:
Cumulative tacrolimus exposure over 3 months is a key determinant of nephrotoxicity and a valuable predictor for dose individualization. Our findings suggest that early PODs, HCT, and baseline renal function should be considered when optimizing tacrolimus therapy.


Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:14
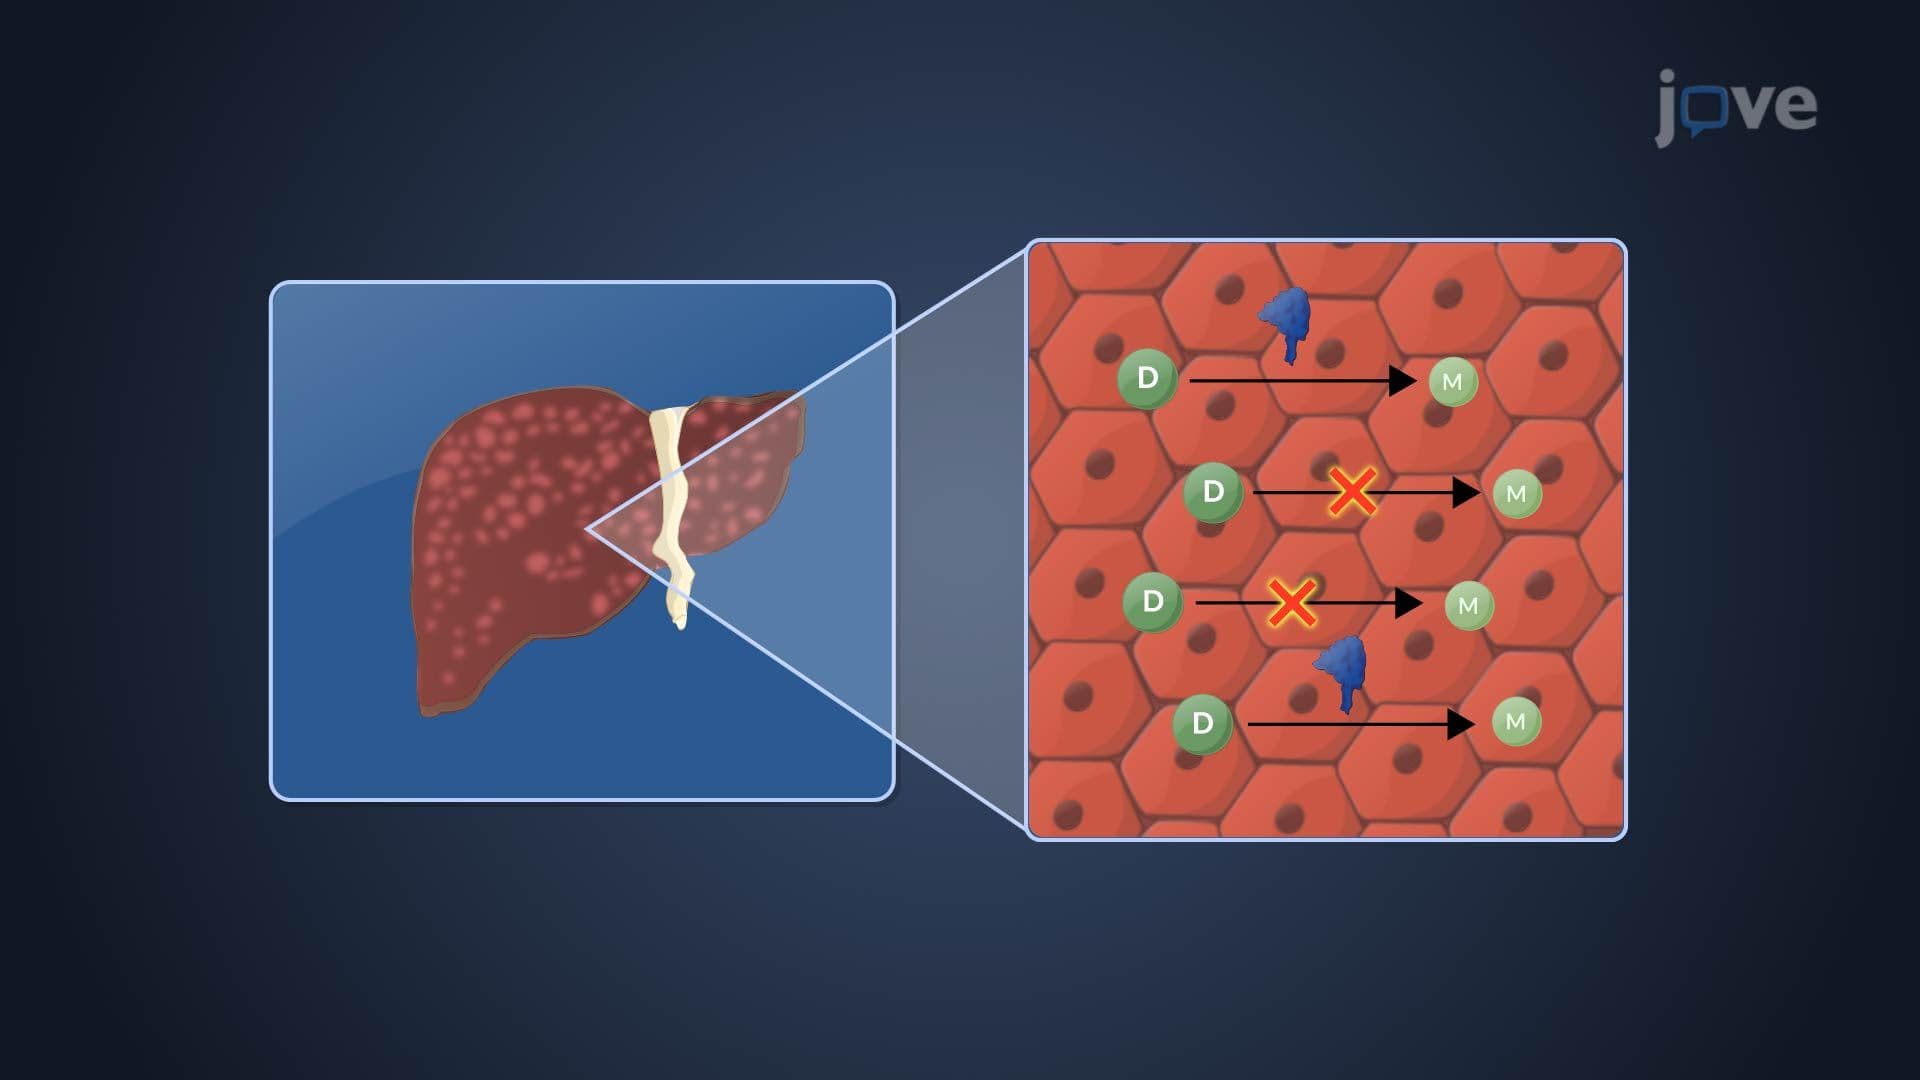
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:07
Physiological Pharmacokinetic Models: Incorporating Hepatic Transporter-Mediated Clearance
A recent model describes pravastatin's hepatobiliary excretion,...