Related Experiment Video
Updated: Jan 7, 2026


A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
Cerebral monitoring responses to bedside physiological challenges in comatose post-cardiac arrest patients
Yorinde S Kishna1,2, Sofia Baars3, Iwan C C van der Horst4,5
1Department of Intensive Care, Maastricht University Medical Center+, Maastricht, The Netherlands. yorinde.kishna@mumc.nl.

Abstract:
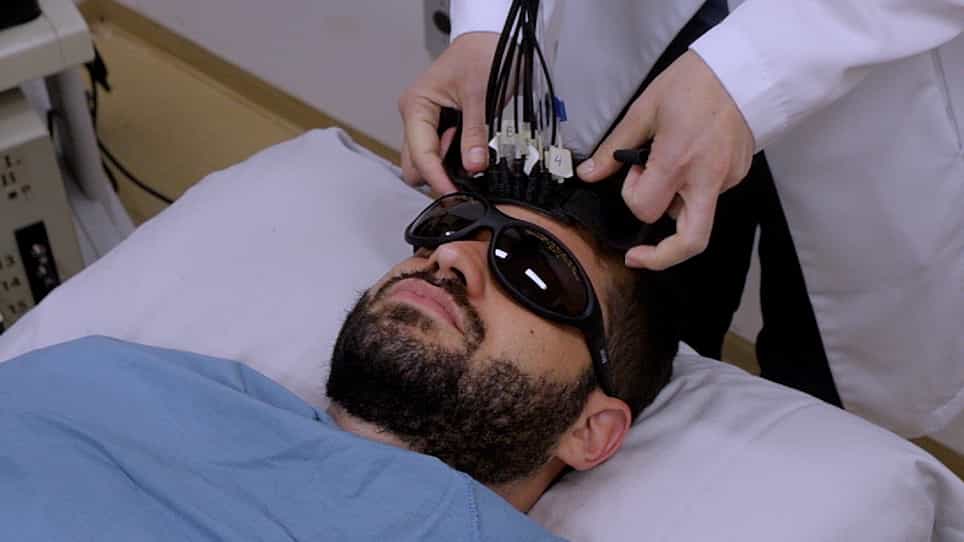
To evaluate the effects of three simple bedside challenges on cerebral oxygenation and brain activity, measured non-invasively using near-infrared spectroscopy (NIRS) and frontal single-channel electroencephalography (EEG), in comatose post-cardiac arrest patients, and to examine whether these responses differ according to cerebral autoregulation status and intensive care unit (ICU) outcome and could aid early prognostication. Three bedside physiological challenges were conducted: (1) increasing the fraction of inspired oxygen (FiO₂) to 100%, (2) lowering the head-of-bed (HOB) to 0°, and (3) elevating end-tidal carbon dioxide (etCO₂) by 1.0 kPa. Tissue oxygen saturation (StO₂) and EEG amplitude were hypothesized to increase, by enhancing oxygen delivery (FiO₂), augmenting cerebral perfusion pressure (HOB), and inducing cerebral vasodilation (etCO₂). Furthermore, we examined the associations between signal responses, cerebral autoregulation status, and ICU outcome. Of the 48 monitored patients, FiO2, HOB, and etCO₂ challenges were successfully completed in 41 (85%), 33 (69%), and 32 (67%) patients, respectively. The StO₂ increased on average by 0.3% (95%-CI 0.2-0.5, p < 0.001) for every 10% rise in FiO2, and 1.94% (95%-CI 0.9-3.0, p < 0.001) for each 15º lowering of the HOB. The etCO₂ challenge did not affect the StO₂. EEG amplitude remained unchanged during all three challenges. No significant differences were found in the responses between patients with intact versus impaired autoregulation or between the ICU outcome groups. Brief physiological challenges simulating common ICU scenarios elicited only modest increases in StO₂, and no measurable response in EEG amplitude. Response patterns were not associated with cerebral autoregulation status or ICU outcome.
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:21
Cardiopulmonary Resuscitation I: Adult