Related Experiment Video
Updated: Jan 9, 2026
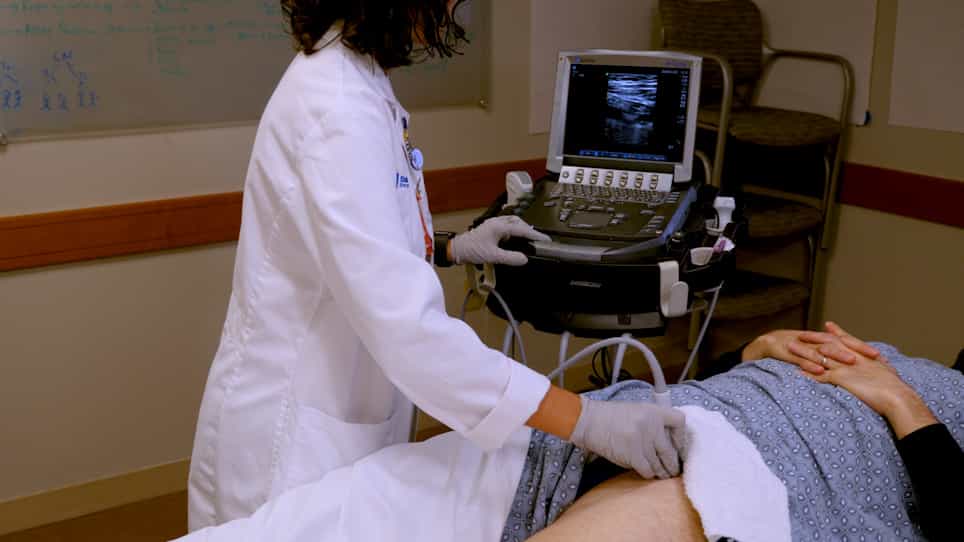

Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Preferences Among Expert Physicians in Areas of Uncertainty in Venous Thromboembolism Management: Results from a
Alessandro Di Minno1,2, Gaia Spadarella3, Ilenia Lorenza Calcaterra4
1Department of Pharmacy, Federico II University Naples, Via D. Montesano 49, 80138 Napoli, Italy.

Abstract:
Background/Objectives: Prevention and treatment of venous thromboembolism (VTE), including deep vein thrombosis (DVT) and pulmonary embolism (PE), is a major clinical issue in hospitalized patients. Some aspects of VTE management lack clarity due to differing physicians' opinions and behaviors. Methods: A multidisciplinary steering committee identified two main areas of uncertainty: VTE prophylaxis and PE management in special settings. A multiple-choice questionnaire including 10 statements was circulated to 183 doctors trained in VTE management. The expected benefit-to-harm ratio was represented on a nine-point Likert scale, with consensus (≥75% agreement) on scores of 1-3 indicating inappropriate and 7-9 indicating appropriate care measures. Results: In online voting, a consensus was reached for 9/10 statements. Respondents considered the following to be appropriate: risk assessment of VTE (93.44%) and bleeding (91.6%) in hospitalized medical patients; low-molecular weight heparin (LMWH) prophylaxis for inpatients with pneumonia and malignancy (82.78%); therapeutic doses of LMWH/fondaparinux in patients with intermediate/high risk of PE with (80.9%) or without (77.97%) instability criteria; and echocardiography to manage patients with a post-PE syndrome (93.99%). Respondents considered the following to be inappropriate: use of 4000 IU LMWH in chronic renal failure (80.46%); use of 2000 IU LMWH in persons on dual antiplatelet therapy (77.01%); and use of low-dose apixaban (2.5 mg) in pregnancy (88.57%) or in subsegmental PE with hypoxemia (82.46%). No consensus was reached on the identification of PE cases eligible for outpatient treatment. Conclusions: Our findings show persistent gaps between guideline recommendations and clinical implementation despite improved awareness among physicians. Uncertainty persists regarding criteria for outpatient PE eligibility and/or for validation of bleeding-risk models.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care