Association between route of furosemide administration and diuretic response in very preterm infants with bronchopulmonary dysplasia
Related Experiment Video
Updated: Jan 9, 2026
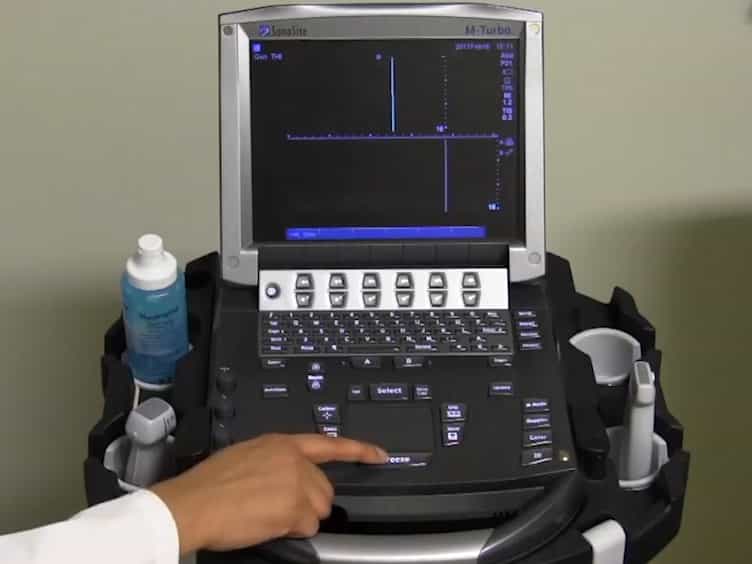
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
Nicolas Bamat1, Matthew Huber1, Heidi Morris1
1Children's Hospital of Philadelphia.

Insights
Furosemide administration routes (IV, gastric, duodenal) show similar diuretic effects in infants with bronchopulmonary dysplasia (BPD). A 1:2 intravenous-to-enteral conversion is effective for managing fluid balance in these infants.
Area of Science:
- Neonatal Medicine
- Pediatric Pharmacology
- Respiratory Medicine
Background:
- Furosemide is frequently used for hospitalized infants with bronchopulmonary dysplasia (BPD).
- Common administration routes include intravenous (IV), gastric, and duodenal.
- The standard 1:2 IV-to-enteral conversion ratio's efficacy is not well-established due to uncertain enteral bioavailability.
Purpose of the Study:
- To compare the diuretic response to furosemide across different administration routes in infants diagnosed with BPD.
- To evaluate the effectiveness of the common 1:2 IV-to-enteral conversion in this patient population.
Main Methods:
- A single-center observational cohort study was conducted on very preterm infants with grade 2-3 BPD.
- Furosemide administration routes (IV, gastric, duodenal) were assessed as the exposure.
- Diuretic response, defined as the change in net fluid balance, was the primary outcome, analyzed using multivariable regression.
Main Results:
- The study included 153 infants with a median postmenstrual age of 43.3 weeks.
- Furosemide administration resulted in a mean fluid balance reduction of -25.6 ml/kg/d.
- Adjusted mean fluid balance changes were comparable across IV (-25.3 ml/kg/d), gastric (-25.8 ml/kg/d), and duodenal (-25.8 ml/kg/d) routes.
Conclusions:
- The findings suggest that a 1:2 IV-to-enteral furosemide conversion yields comparable diuretic effects in infants with established BPD.
- This supports the current clinical practice of using this conversion ratio for managing fluid balance in infants with BPD.
Objective:
Furosemide is commonly prescribed in hospitalized infants with grade 2-3 bronchopulmonary dysplasia (BPD). Intravenous (IV), gastric, and duodenal administrations are common, with a 1:2 IV-to-enteral conversion often used despite uncertain bioavailability. Our objective was to compare diuretic responses between routes in infants with BPD.
Study Design:
Single-center observational cohort of very preterm infants with grade 2-3 BPD prescribed furosemide. The association between route (exposure) and diuretic response (change in net fluid balance after administration, outcome) was evaluated using multivariable regression adjusting for dosing and infant characteristics.
Results:
Among 153 infants (median postmenstrual age of 43.3 weeks at exposure), furosemide reduced fluid balance by -25.6 (29.8) ml/kg/d. Adjusted mean changes were similar across routes: IV, -25.3 (-35.8, -14.7), gastric, -25.8 (-32.2, -19.4), and duodenal, -25.8 (-34.2, -17.4).
Conclusions:
Our data suggest a 1:2 IV-to-enteralconversion leads to comparable diuretic effects in infants with established BPD, supporting this common clinical practice.

Related Concept Videos
 01:21
Factors Affecting Drug Response: Overview
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:29
Drug Dosing: Infants and Children
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:22
Heart Failure Drugs: Diuretics