Related Experiment Video
Updated: Jan 8, 2026
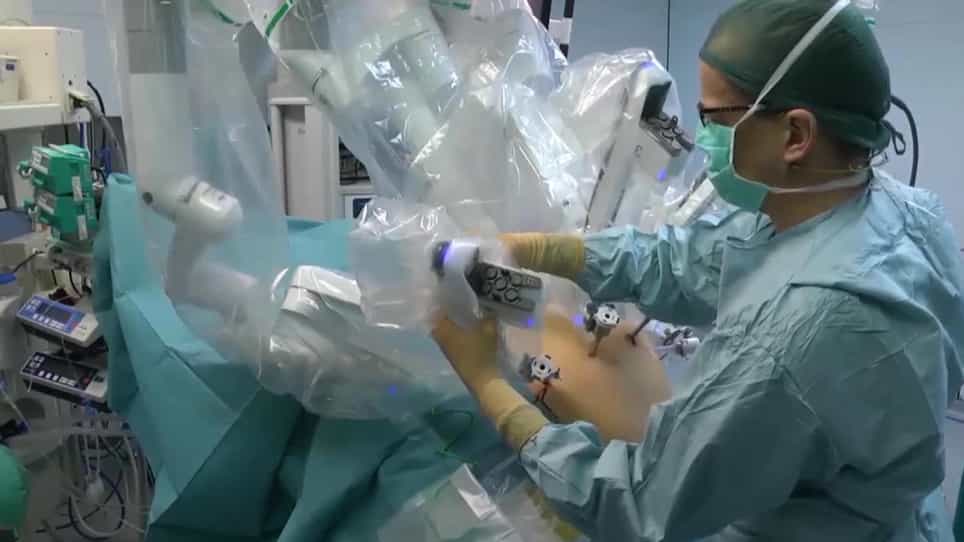

Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
Neoadjuvant therapy versus upfront surgery for resectable pancreatic cancer: Updated systematic review,
Hwee Leong Tan1, Yun Zhao2, Darren Weiquan Chua3
1Department of Hepatopancreatobiliary and Transplant Surgery, Singapore General Hospital and National Cancer Centre Singapore, Academia, Singapore; Duke-National University of Singapore Medical School, Singapore.

Background:
The oncologic benefit of neoadjuvant therapy in resectable pancreatic ductal adenocarcinoma remains uncertain. We conducted an updated systematic review and meta-analysis to evaluate the efficacy of neoadjuvant therapy versus upfront surgery in patients with resectable pancreatic cancer.
Methods:
Searches of various databases identified 9 randomized controlled trials comprising 604 neoadjuvant therapy and 527 upfront surgery patients. Hazard ratios for overall survival and event-free survival were extracted or reconstructed from Kaplan-Meier curves. Dichotomous outcomes were pooled as risk ratios under a random effects model.
Results:
Neoadjuvant therapy produced a significant improvement in event-free survival (hazard ratio 0.77, 95% confidence interval 0.65-0.90) but only a nonsignificant trend toward better overall survival (hazard ratio 0.85, 95% CI 0.68-1.05). One-stage individual patient data reconstruction showed median overall survival rising from 23.7 to 29.6 months (+5.9 months) and median event-free survival from 11.4 to 13.6 months (+2.2 months). Although R0 resection rates appeared higher with neoadjuvant therapy (58.8% vs 52.6%), this difference was not statistically significant (risk ratio 1.13, 95% confidence interval 1.00-1.27). Neoadjuvant therapy reduced noncurative surgeries (surgical exploration rate: risk ratio 0.90, 95% confidence interval 0.87-0.94) and doubled the likelihood of node-negative histology (pN0; 1.73, 95% CI 1.31-2.28). Other outcomes were comparable between the 2 groups. Trial sequential analysis (α = .05, 80% power) confirmed that the event-free survival benefit is definitive, but indicated that both overall survival and R0 resection findings remain inconclusive because of insufficient accumulated data.
Conclusion:
Neoadjuvant therapy significantly prolongs event-free survival, lowers unnecessary surgical exploration and increases pN0 resections in resectable pancreatic cancer. Further adequately powered trials are still needed to confirm the impact of neoadjuvant therapy on overall survival and R0 resection rates.
More Related Videos
 10:04
Laparoscopic Radical Left Pancreatectomy for Pancreatic Cancer: Surgical Strategy and Technique Video
Published on: June 6, 2020
 13:56
Robot Assisted Distal Pancreatectomy with Celiac Axis Resection DP-CAR for Pancreatic Cancer: Surgical Planning and Technique
Published on: August 14, 2021