Related Experiment Video
Updated: Jan 8, 2026

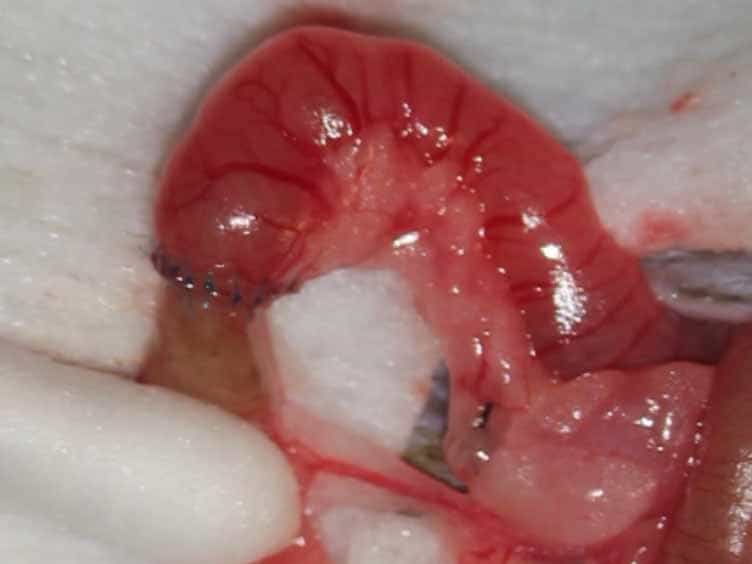
Murine Distal Colostomy, A Novel Model of Diversion Colitis in C57BL/6 Mice
Published on: July 12, 2018
Characteristics of Colonic Pseudo-Obstruction Post Ileostomy Reversal: A Retrospective Study and Scoping Review of
Zirong Yu1, Ferdinand Ong1, Timothy Slack1
1General Surgery, Princess Alexandra Hospital, Woolloongabba, AUS.

Abstract:
Colonic pseudo-obstruction (CPO) is characterized by dilatation of the colon without an anatomical or mechanical obstruction. There are multiple etiologies that may lead to this phenomenon, including post-major abdominal or pelvic surgery, critical illness states, drug-induced effects, and severe electrolyte imbalances, to name a few. An ileostomy closure is a commonly performed surgical procedure that restores the continuity of the gastrointestinal tract post-significant previous colorectal resection. Common complications have been known to occur, such as small bowel ileus, anastomotic leak, wound site infections; however, reports of CPO post-ileostomy closure have not been well reported or studied. This study aimed to evaluate the characteristics, management, and outcomes of patients treated for CPO after loop ileostomy closure and to identify the existing evidence in the literature on this uncommon phenomenon. We conducted a retrospective study of all patients from Princess Alexandra Hospital who developed CPO after ileostomy closure in the past 10 years. Electronic records were accessed to find patient demographic and clinical details, including primary surgery, whether or not radiation was applied, co-morbidities, as well as hospital length of stay and post-operative outcomes. Subsequently, a scoping review was conducted of literature to identify all studies reporting CPO after ileostomy closure. Comparisons were made between our results and those of the scoping review. Nine patients were included in our retrospective study. Seven patients required ileostomy after ultra-low anterior resection (ULAR) for cancer, and two patients for perforated diverticulitis. Mean time to reversal was 7.78 months. Three patients had neoadjuvant and adjuvant chemotherapy, and three patients had neoadjuvant therapy only. CPO diagnosis was made on radiological imaging, and the mean length of hospital stay for all patients was 9.5 days. Mean CPO resolution time was 4.8 days. Scoping review identified 200 studies; however, only one study qualified for inclusion. Five patients were included who underwent ULAR with ileostomy, with four patients requiring neoadjuvant and adjuvant therapy. Mean time to reversal was 8.3 months. Both the retrospective study and scoping review found similar patient characteristics in those who developed CPO post-ileostomy closure. In particular, it would appear that in an irradiated pelvis, the risk of CPO development appeared higher; however, larger patient studies are required to inform better statistical analyses and draw more correlations.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and...
 01:25
Endoscopic Procedures II: Colonoscopy
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...