Related Experiment Video
Updated: Jan 8, 2026
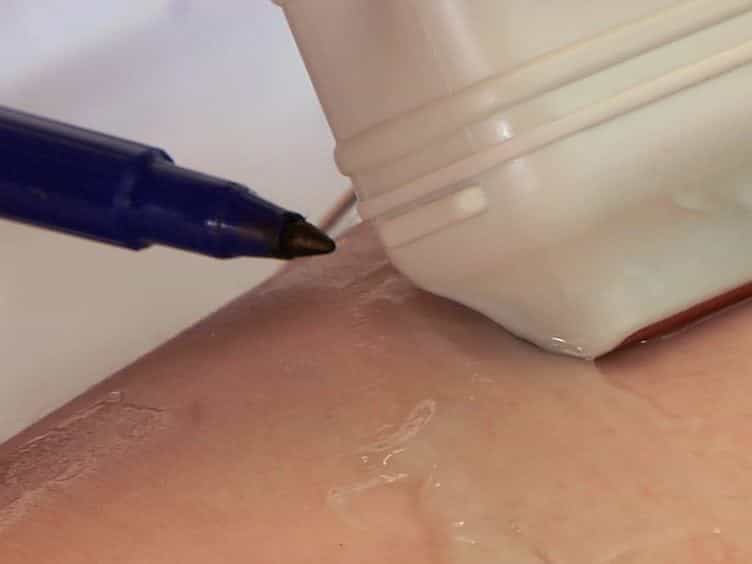

Ultrasound Assessment of Endothelial-Dependent Flow-Mediated Vasodilation of the Brachial Artery in Clinical Research
Published on: October 22, 2014
Interarm blood pressure difference and risk assessment: the ECHORN cohort study
O Peter Adams1,2, Deron Galusha3, Josefa L Martinez-Brockman3,4
1Faculty of Medical Sciences, The University of the West Indies, Cave Hill Campus, Cave Hill, Barbados oswald.adams@uwi.edu.

Insights
Measuring blood pressure in both arms reveals significant interarm differences in about 1 in 10 individuals. Increased body mass index and blood pressure are linked to a higher risk of interarm pressure differences.
Area of Science:
- Cardiology
- Public Health
- Epidemiology
Background:
- Current guidelines recommend bilateral arm blood pressure (BP) measurement, utilizing the higher reading for clinical decisions.
- Interarm blood pressure difference (IAD) is a recognized clinical finding with potential implications for cardiovascular risk assessment.
Purpose of the Study:
- To investigate the prevalence and distribution of interarm blood pressure differences (IAD) in an adult population.
- To identify factors associated with IAD and evaluate the impact of using higher versus lower arm BP readings on BP and atherosclerotic cardiovascular disease (ASCVD) risk classification.
Main Methods:
- A cross-sectional cohort study was conducted on 2912 community-dwelling adults aged 40 years and older across four Caribbean islands.
- Blood pressure was measured simultaneously in both arms. Statistical analyses, including mixed-effects logistic and linear regression, were employed to assess associations with IAD and reclassification of BP and ASCVD risk.
Main Results:
- Prevalence of systolic IADs ≥10 mmHg was 10.7% and ≥15 mmHg was 3.3%. Diastolic IADs ≥10 mmHg occurred in 5.0% and ≥15 mmHg in 1.8% of participants.
- Higher body mass index (BMI), systolic BP, diastolic BP, and hypertension were independently associated with increased IAD (P<0.05).
- Utilizing the higher arm BP reading reclassified approximately 1 in 10 individuals to a higher BP or ASCVD risk category.
Conclusions:
- Bilateral arm BP measurement is crucial for detecting significant IAD (≥10 mmHg) in a substantial proportion of the population.
- Factors such as elevated BMI and higher BP readings are associated with an increased likelihood of significant IAD.
- Accurate BP measurement through bilateral assessment is essential for appropriate cardiovascular risk stratification.
Background:
Guidelines recommend measuring blood pressure (BP) in both arms and using the higher reading.
Aim:
To determine interarm pressure difference (IAD) distribution and associated factors, and BP and atherosclerotic cardiovascular disease (ASCVD) risk classification using the higher and lower readings.
Design & Setting:
This cohort study used a representative cross-sectional sample of community-dwelling residents aged ≥40 years on four Caribbean islands (Barbados, Puerto Rico, US Virgin Islands, and Trinidad).
Method:
BP was measured simultaneously in both arms. Mixed effects logistic and linear regression tested associations with an IAD. BP and ASCVD risk were classified using the higher and lower BP.
Results:
Of 2912 participants (mean age 57.2 years), 10.7% (95% confidence interval [CI] = 9.6 to 11.8) and 3.3% (95% CI = 2.6 to 3.9) had systolic IADs ≥10 mmHg and ≥15 mmHg, respectively, and 5.0% (95% CI = 4.2 to 5.8) and 1.8% (95% CI = 1.3 to 2.3) diastolic IADs ≥10 mmHg and ≥15 mmHg, respectively. Independent associations with systolic and diastolic IADs ≥10 mmHg and/or continuous outcomes, included increasing body mass index (BMI), systolic and diastolic pressures and hypertension (P<0.05). Higher versus lower arm BP reclassified 10.3% (95% CI = 7.8 to 12.8) and 8.3% (95% CI = 5.9 to 10.7) from below to above the 130-mmHg and 140-mmHg systolic thresholds, respectively, 10.8% (95% CI = 8.2 to 13.3) and 6.9% (95% CI = 4.9 to 8.9) at the 80-mmHg and 90-mmHg diastolic thresholds, respectively, and 9.2% (95% CI = 0.0 to 18.4) of those with an IAD of ≥10 mmHg at the ≥10% 10-year ASCVD risk threshold.
Conclusion:
Assessing both arms detects an IAD ≥10 mmHg and reclassifies BP in about 1 in 10 people. Increasing BMI and BP increase the risk of an IAD ≥10 mmHg or 15 mmHg.


Related Concept Videos
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:23
Assessment of blood pressure in brachial artery(two-step method)
 01:11
Assessing Blood pressure in the Leg
Preparation:
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment: