Related Experiment Video
Updated: Jan 8, 2026
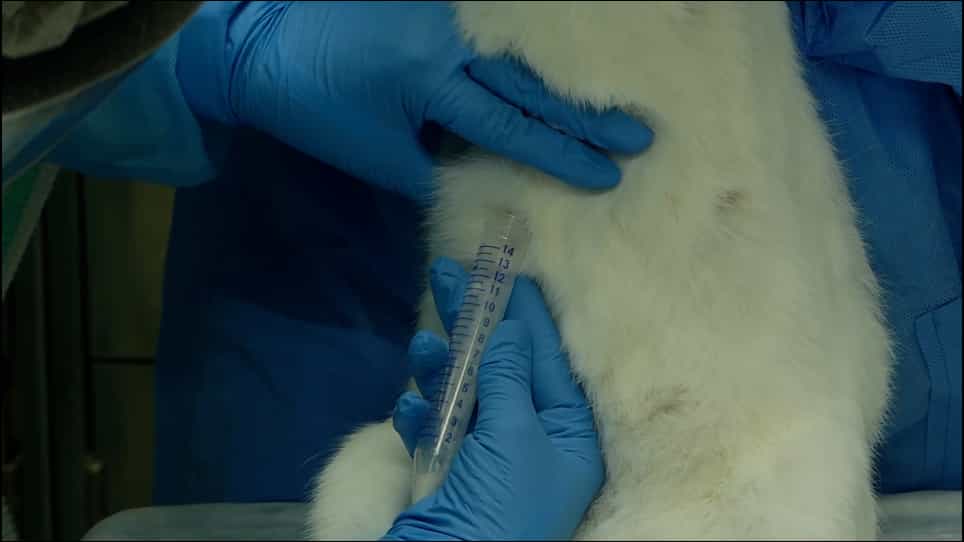

Intranasal Immunization and Milk Collection in Studies of Maternal Immunization in New Zealand White Rabbits Oryctolagus cuniculus
Published on: July 31, 2021
Prophylactic-Dose Rivaroxaban Transfer Into Human Milk
Ann M Bruno1, Kathleen M Job, Joseph E Rower
1Department of Obstetrics & Gynecology, the Department of Pediatrics, the Center for Human Toxicology, and the Department of Hematology, University of Utah Health, Salt Lake City, and the Department of Pediatrics, Intermountain Health, Murray, Utah; and the Department of Obstetrics and Gynecology, Duke Health, Durham, North Carolina.

Direct oral anticoagulants are increasingly used for postoperative thromboprophylaxis, but use is limited in postpartum populations in the absence of data informing transfer into human milk. We evaluated the excretion of prophylactic-dose rivaroxaban into the milk of 20 low-risk lactating individuals from April through September 2024. Participants received two doses of prophylactic-dose rivaroxaban and provided blood and milk samples, with rivaroxaban concentrations quantified by liquid chromatography-tandem mass spectrometry. Pharmacokinetic metrics were evaluated, and the relative infant dose was calculated. Maternal plasma and milk rivaroxaban concentration peaked 2 hours after the second dose. At maximum maternal milk concentration of rivaroxaban, the relative infant dose was 2.9%, below the 10% safety threshold for drug use during breastfeeding. Findings suggest that neonatal exposure is likely low risk for use of prophylactic-dose rivaroxaban in lactating individuals.
Direct oral anticoagulants are increasingly used for postoperative thromboprophylaxis, but use is limited in postpartum populations in the absence of data informing transfer into human milk. We evaluated the excretion of prophylactic-dose rivaroxaban into the milk of 20 low-risk lactating individuals from April through September 2024. Participants received two doses of prophylactic-dose rivaroxaban and provided blood and milk samples, with rivaroxaban concentrations quantified by liquid chromatography-tandem mass spectrometry. Pharmacokinetic metrics were evaluated, and the relative infant dose was calculated. Maternal plasma and milk rivaroxaban concentration peaked 2 hours after the second dose. At maximum maternal milk concentration of rivaroxaban, the relative infant dose was 2.9%, below the 10% safety threshold for drug use during breastfeeding. Findings suggest that neonatal exposure is likely low risk for use of prophylactic-dose rivaroxaban in lactating individuals.


Related Concept Videos
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption